Benchmark corrected letters
Source: original PDF. These are historical corrected submissions, not uniformly high-scoring model answers. For selectable PDF text, the PDF text layer is preferred; scanned and mixed pages use OCR at 220 dpi. Handwritten pages are especially unreliable. OCR can misread names, grades, doses or corrections: check the linked page image before relying on them.
Page 1
Case notes / writing task (OCR)
OET FUTURE LAND
Corrected letters by

Page 2 — Re: Mrs. Katherine Walter DOB: 26/11/1975
Letter
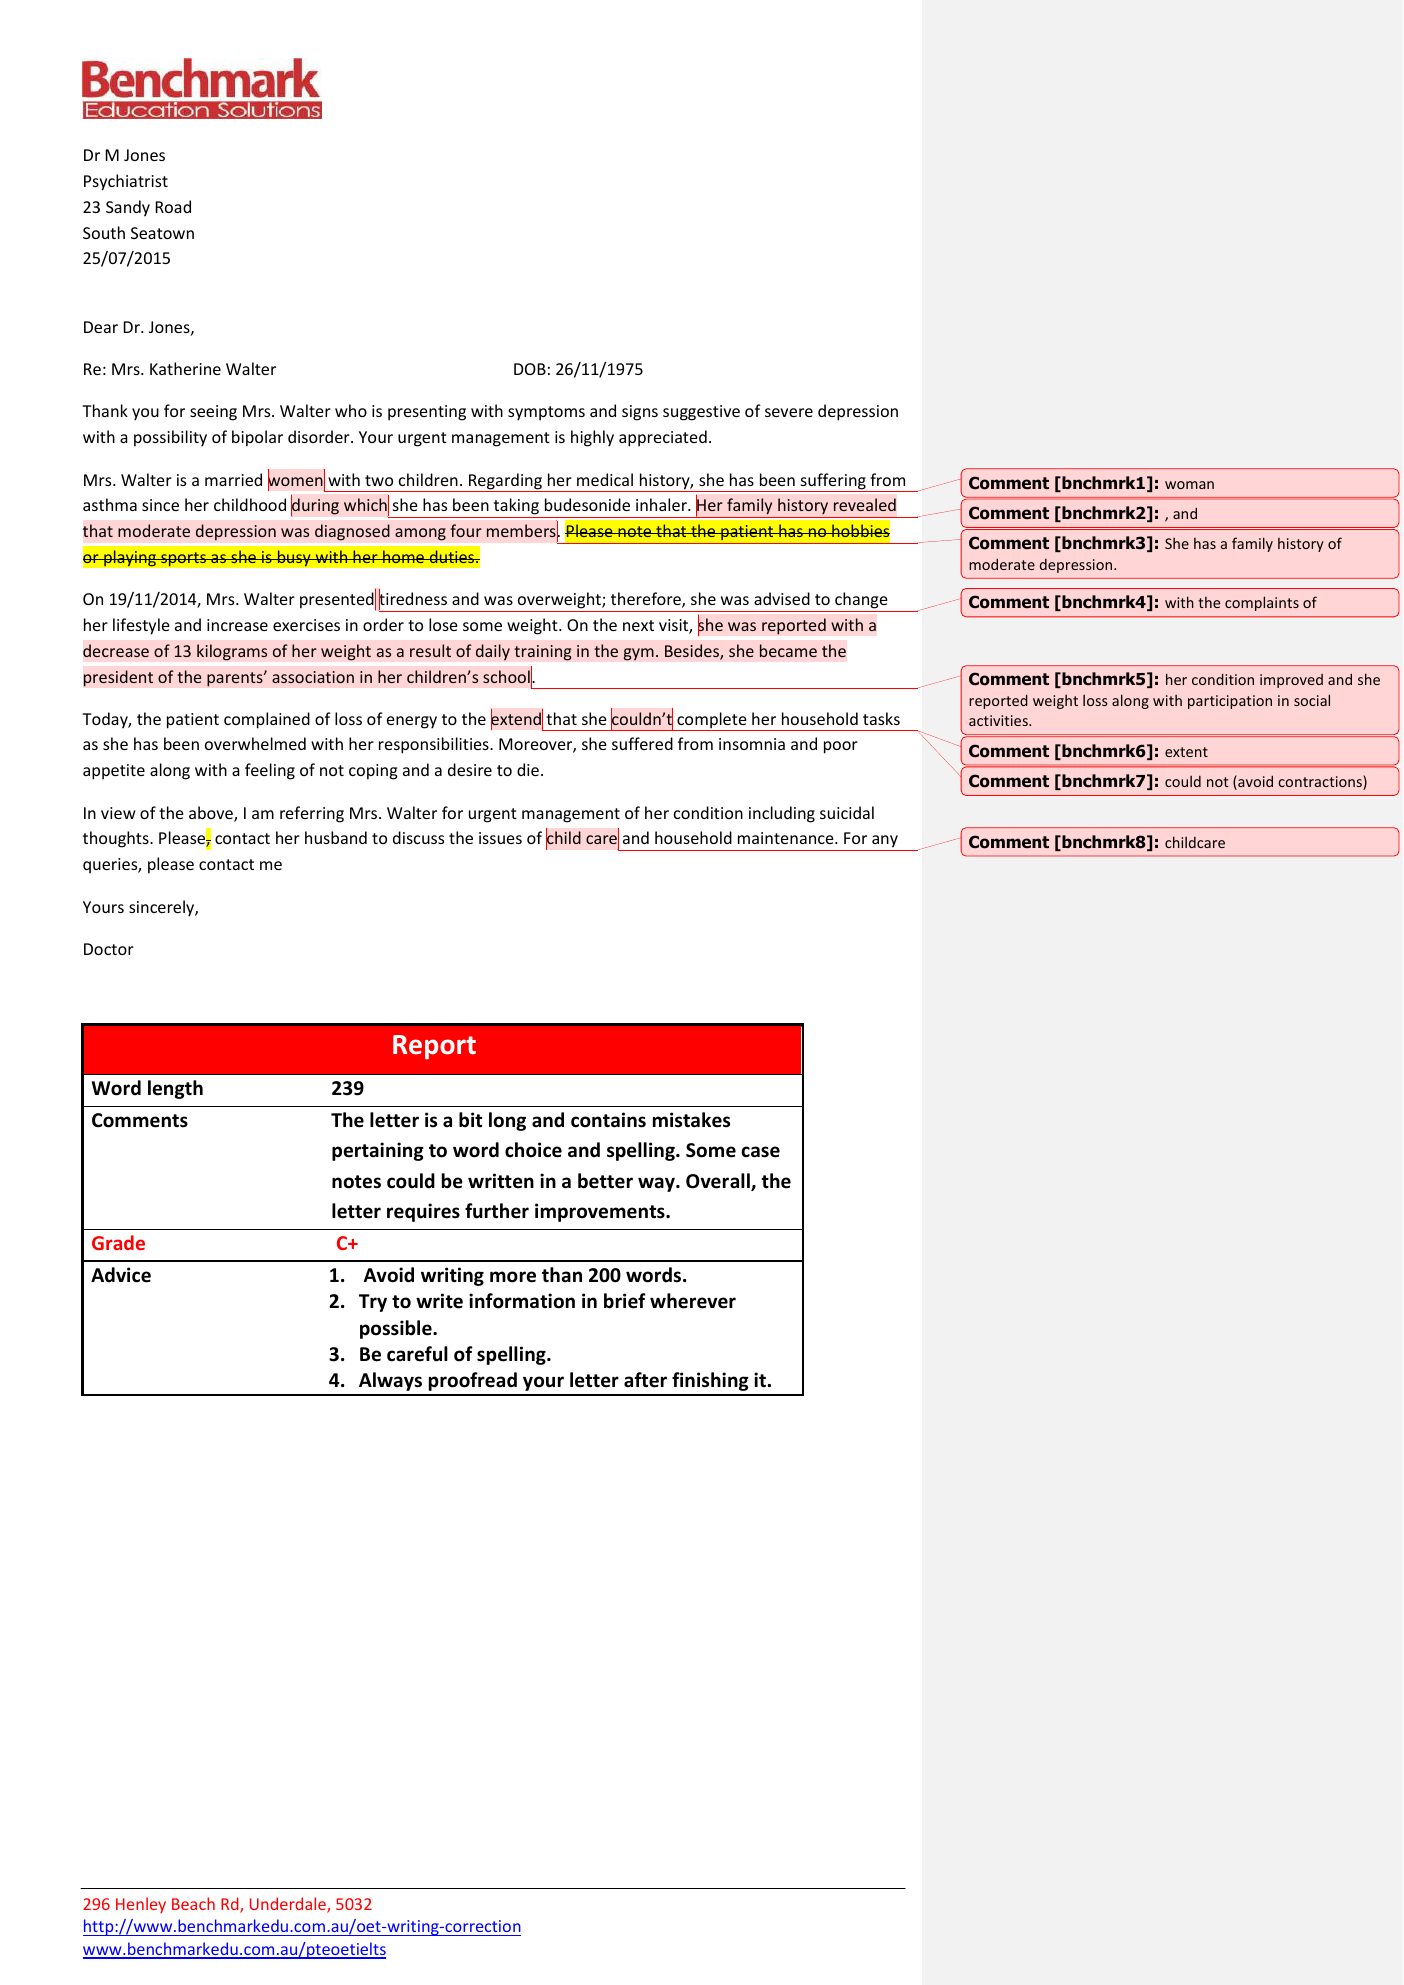
Dr M Jones
Psychiatrist
23 Sandy Road
South Seatown
25/07/2015
Dear Dr. Jones,
Re: Mrs. Katherine Walter DOB: 26/11/1975
Thank you for seeing Mrs. Walter who is presenting with symptoms and signs suggestive of severe depression
with a possibility of bipolar disorder. Your urgent management is highly appreciated.
Mrs. Walter is a married women with two children. Regarding her medical history, she has been suffering from
asthma since her childhood during which she has been taking budesonide inhaler. Her family history revealed
that moderate depression was diagnosed among four members. Please note that the patient has no hobbies
or playing sports as she is busy with her home duties.
On 19/11/2014, Mrs. Walter presented tiredness and was overweight; therefore, she was advised to change
her lifestyle and increase exercises in order to lose some weight. On the next visit, she was reported with a
decrease of 13 kilograms of her weight as a result of daily training in the gym. Besides, she became the
president of the parents’ association in her children’s school.
Today, the patient complained of loss of energy to the extend that she couldn’t complete her household tasks
as she has been overwhelmed with her responsibilities. Moreover, she suffered from insomnia and poor
appetite along with a feeling of not coping and a desire to die.
In view of the above, I am referring Mrs. Walter for urgent management of her condition including suicidal
thoughts. Please, contact her husband to discuss the issues of child care and household maintenance. For any
queries, please contact me
Yours sincerely,
Doctor
Assessor feedback
Word length 239
Comments The letter is a bit long and contains mistakes
pertaining to word choice and spelling. Some case
notes could be written in a better way. Overall, the
letter requires further improvements.
Grade C+
Advice 1. Avoid writing more than 200 words.
2. Try to write information in brief wherever
possible.
3. Be careful of spelling.
4. Always proofread your letter after finishing it.
Margin comments
- Comment [bnchmrk1]: woman
- Comment [bnchmrk2]: , and
- Comment [bnchmrk3]: She has a family history of moderate depression.
- Comment [bnchmrk4]: with the complaints of
- Comment [bnchmrk5]: her condition improved and she reported weight loss along with participation in social activities.
- Comment [bnchmrk6]: extent
- Comment [bnchmrk7]: could not (avoid contractions)
- Comment [bnchmrk8]: childcare
Page 3 — Re: Joshua Vance DOB: 17/11/2013
Letter
Admitting Officer
Emergency Department
Children‘s Hospital
Newtown
18/01/2014
Dear Sir,
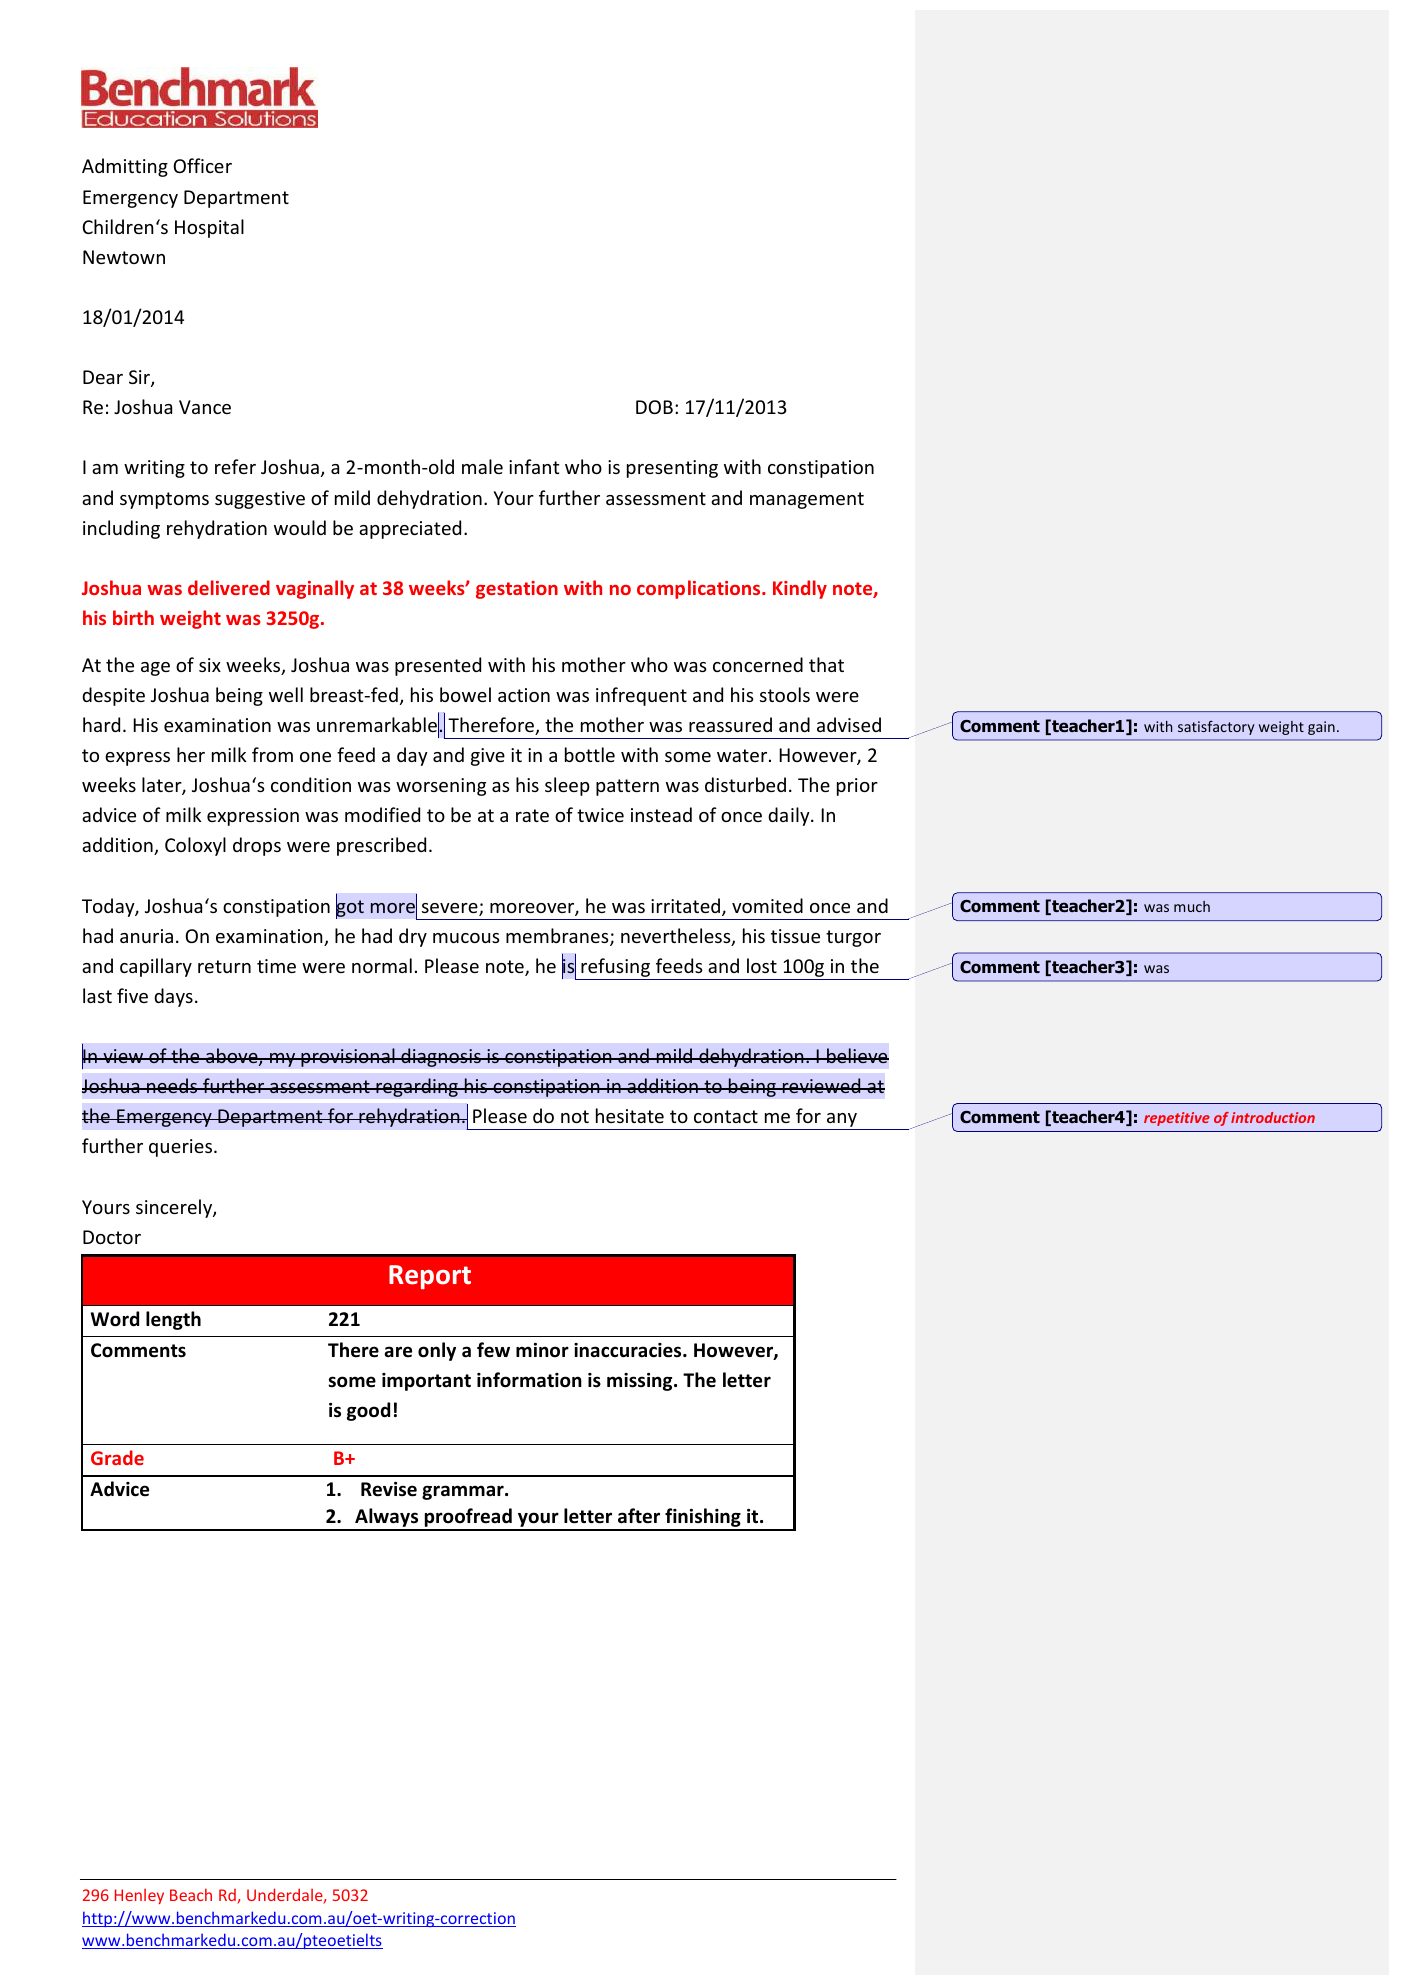
Re: Joshua Vance DOB: 17/11/2013
I am writing to refer Joshua, a 2-month-old male infant who is presenting with constipation
and symptoms suggestive of mild dehydration. Your further assessment and management
including rehydration would be appreciated.
Joshua was delivered vaginally at 38 weeks’ gestation with no complications. Kindly note,
his birth weight was 3250g.
At the age of six weeks, Joshua was presented with his mother who was concerned that
despite Joshua being well breast-fed, his bowel action was infrequent and his stools were
hard. His examination was unremarkable. Therefore, the mother was reassured and advised
to express her milk from one feed a day and give it in a bottle with some water. However, 2
weeks later, Joshua‘s condition was worsening as his sleep pattern was disturbed. The prior
advice of milk expression was modified to be at a rate of twice instead of once daily. In
addition, Coloxyl drops were prescribed.
Today, Joshua‘s constipation got more severe; moreover, he was irritated, vomited once and
had anuria. On examination, he had dry mucous membranes; nevertheless, his tissue turgor
and capillary return time were normal. Please note, he is refusing feeds and lost 100g in the
last five days.
In view of the above, my provisional diagnosis is constipation and mild dehydration. I believe
Joshua needs further assessment regarding his constipation in addition to being reviewed at
the Emergency Department for rehydration. Please do not hesitate to contact me for any
further queries.
Yours sincerely,
Doctor
Assessor feedback
Word length 221
Comments There are only a few minor inaccuracies. However,
some important information is missing. The letter
is good!
Grade B+
Advice 1. Revise grammar.
2. Always proofread your letter after finishing it.
Margin comments
- Comment [teacher1]: with satisfactory weight gain.
- Comment [teacher2]: was much
- Comment [teacher3]: was
- Comment [teacher4]: repetitive of introduction
Page 4 — Re: Mr Daniel McCrae, DOB: 17/10/1962
Letter
Associate Professor Simon Anderson
Surgeon
Suite 65
City Hospital
25-29 Main Road
Centreville
22/02/2014
Dear Dr Anderson,
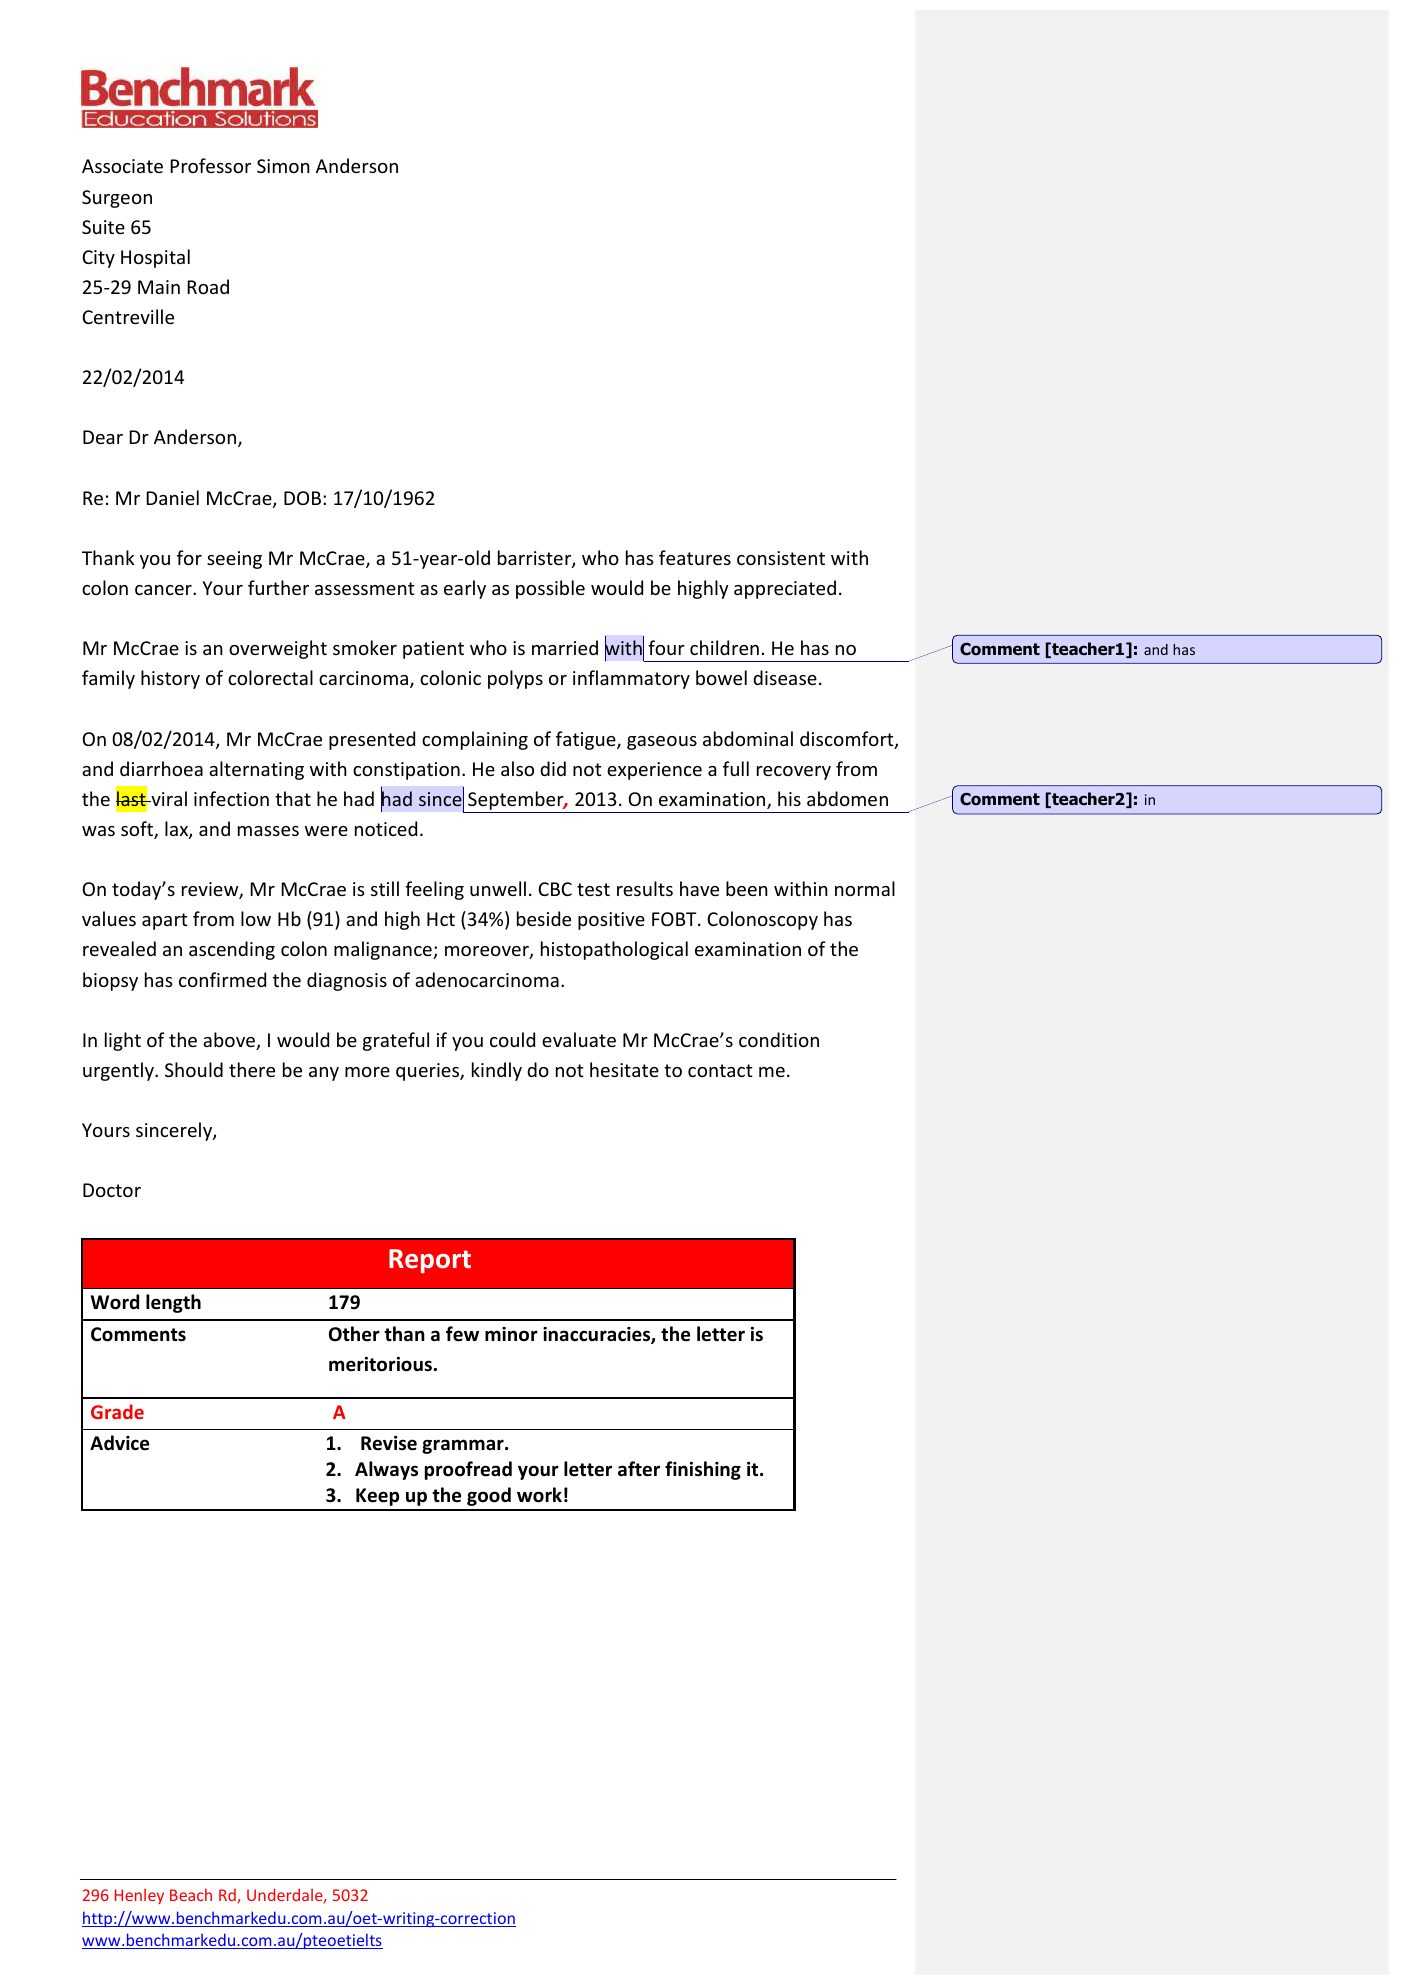
Re: Mr Daniel McCrae, DOB: 17/10/1962
Thank you for seeing Mr McCrae, a 51-year-old barrister, who has features consistent with
colon cancer. Your further assessment as early as possible would be highly appreciated.
Mr McCrae is an overweight smoker patient who is married with four children. He has no
family history of colorectal carcinoma, colonic polyps or inflammatory bowel disease.
On 08/02/2014, Mr McCrae presented complaining of fatigue, gaseous abdominal discomfort,
and diarrhoea alternating with constipation. He also did not experience a full recovery from
the last viral infection that he had had since September, 2013. On examination, his abdomen
was soft, lax, and masses were noticed.
On today’s review, Mr McCrae is still feeling unwell. CBC test results have been within normal
values apart from low Hb (91) and high Hct (34%) beside positive FOBT. Colonoscopy has
revealed an ascending colon malignance; moreover, histopathological examination of the
biopsy has confirmed the diagnosis of adenocarcinoma.
In light of the above, I would be grateful if you could evaluate Mr McCrae’s condition
urgently. Should there be any more queries, kindly do not hesitate to contact me.
Yours sincerely,
Doctor
Assessor feedback
Word length 179
Comments Other than a few minor inaccuracies, the letter is
meritorious.
Grade A
Advice 1. Revise grammar.
2. Always proofread your letter after finishing it.
3. Keep up the good work!
Margin comments
- Comment [teacher1]: and has
- Comment [teacher2]: in
Page 5 — Re: Mr James Seymour, DOB: 19/09/1953
Letter
Dr Malcom Still
Rheumatologist.
5 Grant St
Fairmont
03 May 2014
Dear Dr Still,
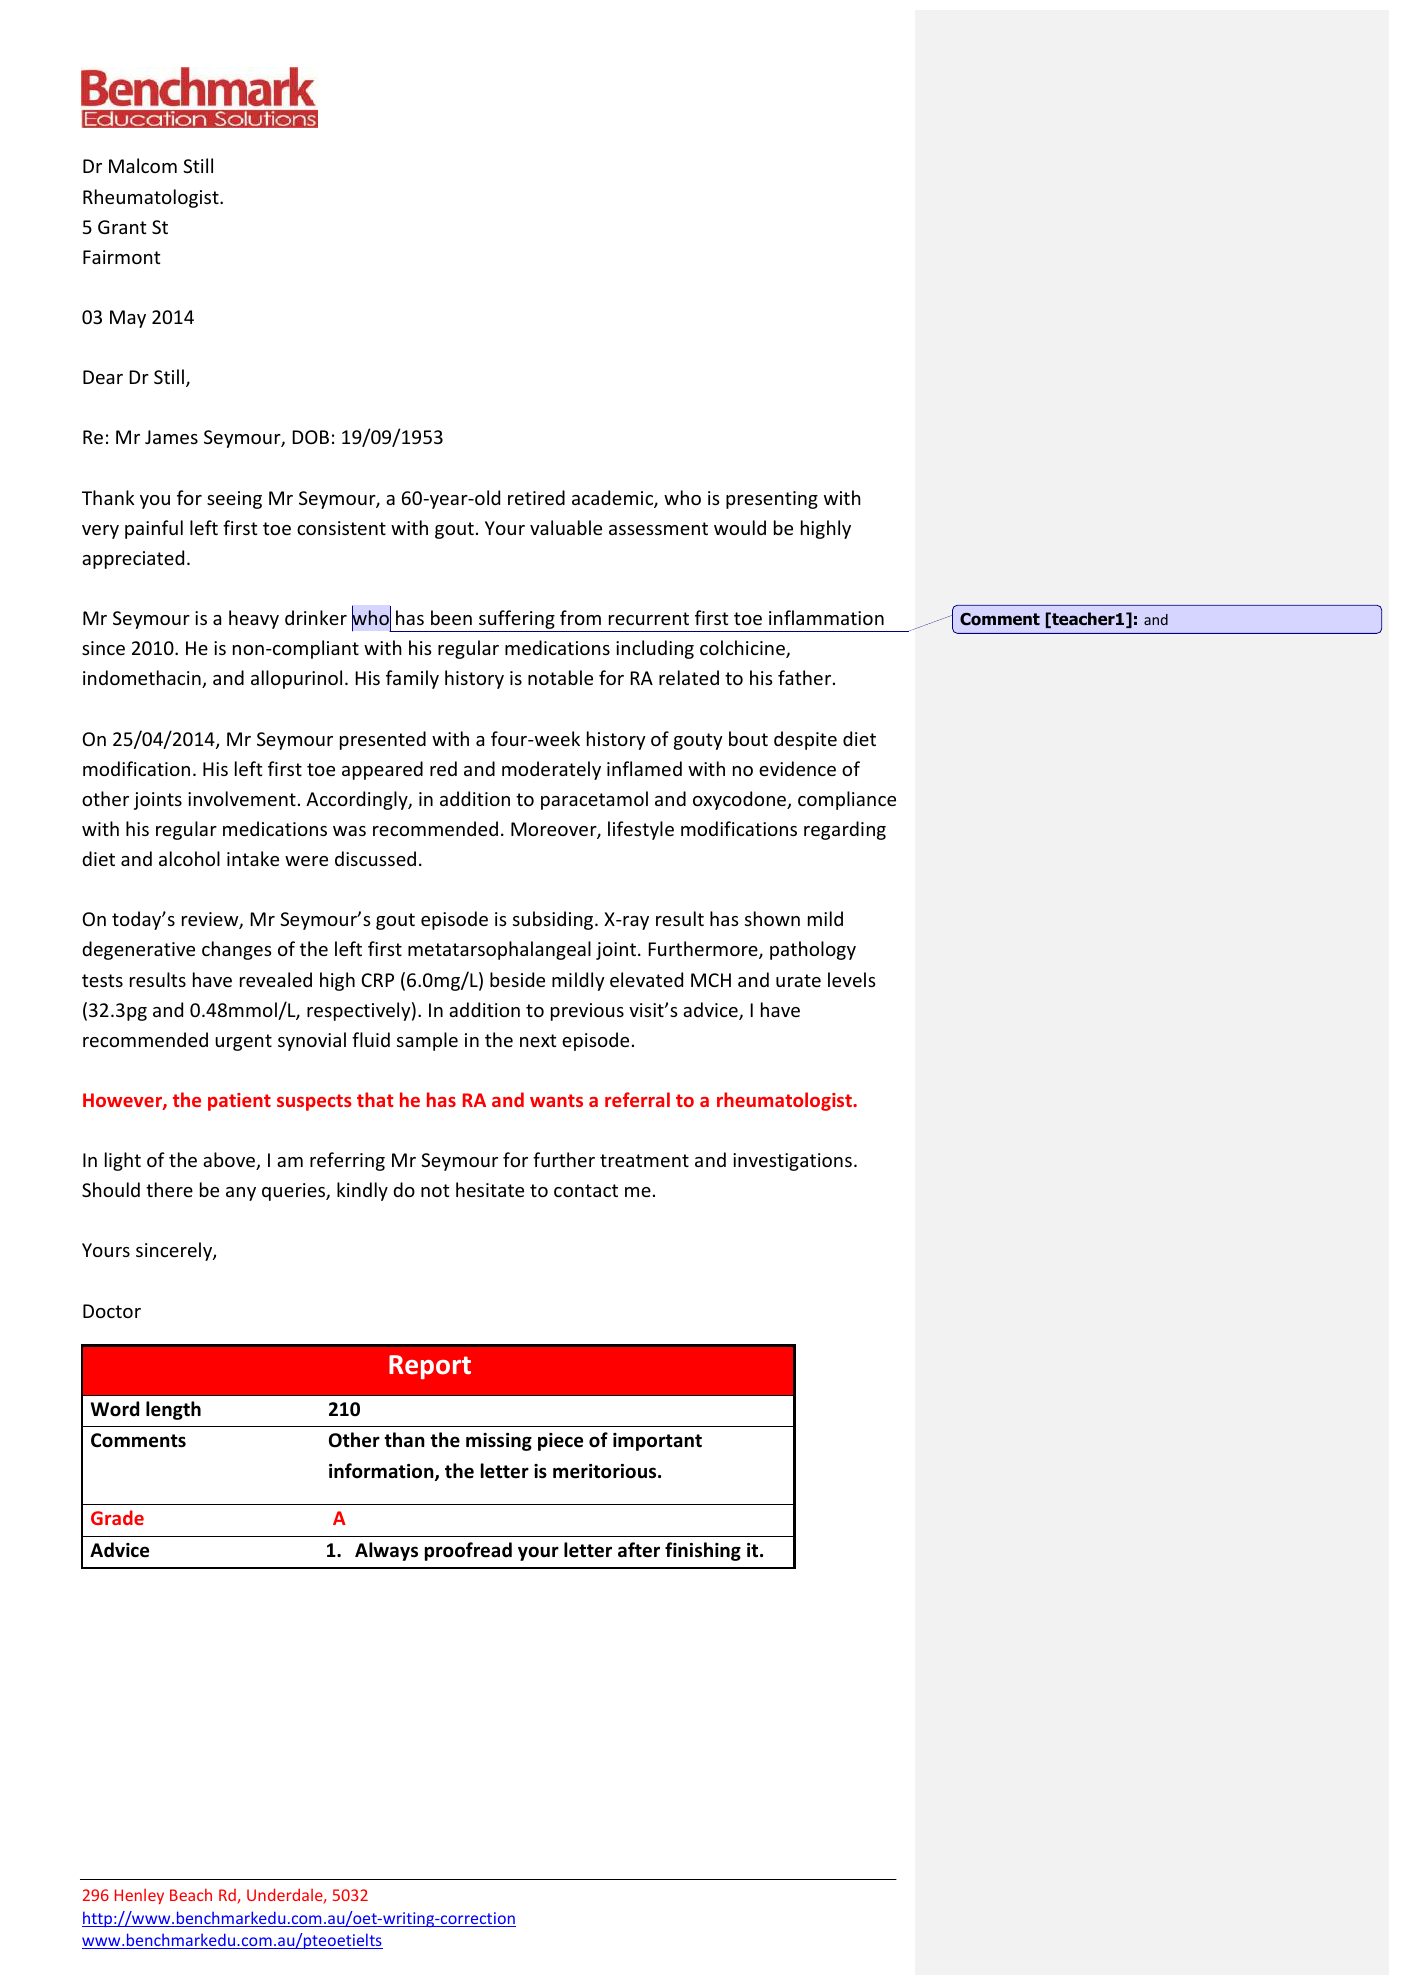
Re: Mr James Seymour, DOB: 19/09/1953
Thank you for seeing Mr Seymour, a 60-year-old retired academic, who is presenting with
very painful left first toe consistent with gout. Your valuable assessment would be highly
appreciated.
Mr Seymour is a heavy drinker who has been suffering from recurrent first toe inflammation
since 2010. He is non-compliant with his regular medications including colchicine,
indomethacin, and allopurinol. His family history is notable for RA related to his father.
On 25/04/2014, Mr Seymour presented with a four-week history of gouty bout despite diet
modification. His left first toe appeared red and moderately inflamed with no evidence of
other joints involvement. Accordingly, in addition to paracetamol and oxycodone, compliance
with his regular medications was recommended. Moreover, lifestyle modifications regarding
diet and alcohol intake were discussed.
On today’s review, Mr Seymour’s gout episode is subsiding. X-ray result has shown mild
degenerative changes of the left first metatarsophalangeal joint. Furthermore, pathology
tests results have revealed high CRP (6.0mg/L) beside mildly elevated MCH and urate levels
(32.3pg and 0.48mmol/L, respectively). In addition to previous visit’s advice, I have
recommended urgent synovial fluid sample in the next episode.
However, the patient suspects that he has RA and wants a referral to a rheumatologist.
In light of the above, I am referring Mr Seymour for further treatment and investigations.
Should there be any queries, kindly do not hesitate to contact me.
Yours sincerely,
Doctor
Assessor feedback
Word length 210
Comments Other than the missing piece of important
information, the letter is meritorious.
Grade A
Advice 1. Always proofread your letter after finishing it.
Margin comments
- Comment [teacher1]: and
Page 6
Case notes / writing task (OCR)
Patient:
Mr George Poulos is a 45-year-old man who has hurt his back. He presented at
21/06/14
your general practice surgery for the first time in late June.
Subjective:
2 days ago at home lifting logs (approx. weight each 20-30kg) from ground
Severe lower back pain of 2 days duration:
into wheelbarrow.
Sudden severe pain - mid lower back. Thought he felt a click.
Action: bending, lifting and rotation.
Was locked in semi-flexed position, almost impossible to walk.
Wife helped him into house and bed.
Took 2x Panadeine Forte, repeated 4 hours later.
Pain only low back, no radiation to thighs.
Disturbed sleep.
Yesterday pain less severe, able to ambulate around house.
Today again pain less severe.
Patient History:
Married - 3 children secondary school, 1 primary school.
Stockbroker - 45 y.o.
App:
Bowels: Normal. Diarrhoea if stressed.
Mict:
Wt:
Normal.
Sex:
Often too tired.
Varies - BMI 27.
Exercise: Nil.
Tobacco: 25/day.
HICONOLA
Frequently 10+ to 15+ std drinks/day.
Allergies:
Pethidine, penicillins, radiographic contrast agent (unspecified) ?? iodine.
Family History:
HPI: Head injury (football) approx 15yrs ago. MRI brain. NAD.
No Ca bowel, no diabetes, no cardiovascular.
neacted to contrast medium.
Objective:
Full examination.
P 68bpm reg. BP 135/80.
CVS, RS, RES, CNS: NAD.
Loss of lumbar lordosis.
Musculo-skeletal: Stands erect. No scoliosis.
Lumbar spine: Flexion fingertips to patella. Expression of pain.
Lateral flexion: L & R full.
Extension limited by pain.
Rotation: L & R fuil.
No sensory loss.
Reflexes: Patellar & Ankle L+ R+.
Plan:
SLR (straight leg raise): L 90 R 90.
Take time off work. Analgesia: paracetamol 500mg 2x 4hrly max 8 in 24hrs or
Review 1 week.
Panadeine Forte, or 1 of each. Warned - risk of constipation with Codeine.
28/06/14
Has now developed pain which extends down back of R thigh, lateral calf and
into dorsum of foot.
Objective:
thigh and SLR: L 85 R 60.
Examination. As before except that now lumbar flexion limited to fingers to mid
05/07/14
Review 1 week.
Pain worse.
Objective:
Almost immobile. Severe pain down R leg. Tingling in R calf.
Examination. Lumbar flexion almost nil. Other movts more restricted by pain.
Loss of light touch sensation lateral distal calf & plantar aspect of foot.
SLR: L 70 R 50.
Diagnosis: Low back pain, probably discogenic, with radiculopathy.
Loss of R ankle reflex.
provide advice regarding the possibility of surgery.
Refer to neurosurgeon & request that the neurosurgeon order an MRI and
Writing Task:
Using the information given in the case notes, write a letter of referral to Dr B White, Neurosurgeon.
City Hospital, Newtown.
Dr B White
Neurosurgeon
City Hospital
Newtown
04/8/2018
Dear Dr White,
Re: Mr George Poulos
Aged 45 years old
I am writing to refer Mr. Poulos, a 45-year-old patient who is presenting with features
suggestive of lumbar disc prolapse and requiring urgent urgent medical attention.
Margin comments
- Comment [teacher1]:,
- Comment [teacher2]: requires

Page 7
Case notes / writing task
Mr. Poulos is married and has 3 children. He is a smoker and he drinks alcohol frequently.
Pleased note, he is allergic to pethidine and radioactive contrasts agents.
He has been seen me on several occasion after he has suffered from a low back pain followed
lifting a heavy object at work. During which time ,his pain was progressing and started to
radiate along his calf into the foot. Examination findings revealed painful limited flexion and
extension. However, analgesics were prescribed and he had medical leave from his work.
Today, Mr. Poulos reported that his pain became severe and there was tingling in his calf.
Moreover, he became immobile. Examination revealed light sensation loss and ankle reflexes
were absent .In addition, straight leg raise test was positive.
My provisional diagnosis is lumbar disc prolapse compounded by radiculopathy. However, I
would be appropriated if you could arrange a consultation to order an MRI and assesses his
suitability for surgery.
Yours Sincerely,
Doctor
Assessor feedback
Word length 184
Comments The letter has inaccuracies pertaining to articles,
tenses, punctuation, word choice and sentence
formation. Information could be written in a better
way. Overall, the letter does not meet the
expectations.
Grade C
Advice 1. Revise grammar.
2. Improve choice of words.
3. Always proofread the letter after finishing
writing it.
Margin comments
- Comment [teacher3]: , penicillin and a
- Comment [teacher4]: contrast agent
- Comment [teacher5]: presented on 20/01/14
- Comment [teacher6]: that
- Comment [teacher7]: of
- Comment [teacher8]: This pain tended
- Comment [teacher9]: Thus
- Comment [teacher10]: was
- Comment [teacher11]: had become
- Comment [teacher12]: and I would appreciate
Page 8 — Re: Mr Patrick Newtown
Letter
Dr Jack Thomas
Department of Gastroenterology
City Hospital
Main Road
Stillwater
21/02/15
Dear Dr Thomas,
Re: Mr Patrick Newtown
I am writing to refer Mr Newtown, a 22_year-old single accountant, whose features are
suggestive of a chronic inflammatory bowel disease . Your further assessment would be
highly appreciated.
Mr Newtown has a habit of smoking and lives with his parents. Please note, his uncle has had
Crohn’s disease.
Regarding his past medical history, the patient reported mild on and off pain in the right and
left wrist joints.
Today, Mr Newtown has been complianing of chronic mild diarrhoea associated with low-
grade intermittent pain in the right lower quadrant abdominal side since 10/14. Moreover, he
has had lethergy, weight loss and poor appetite. Althought he has not sought medical advice,
he has tried ibuprofen and diet modification.
His examination is unremarkable a part from generlized abdominal tenderness. His blood test
as follow: positive faecal occult blood test , mildly elevated CRP and ESR along with anaemia
and a high WBC count. He has been advised to quit smoking.
Based on the above, Mr Newtown is referred to you to be diagnosed and advised to cease
smoking in addition to information about IBD and relevant investigation.
Please do not hesitate to contact me if you require any futher details.
Yours sincerely,
Doctor X
Assessor feedback
Word length 192
Comments An effort to accomplish the task is visible.
However, the letter has several inaccuracies. These
pertain to word choice, grammar and spelling.
Overall, the letter does not meet the expectations.
Grade C
Advice 1. Revise grammar.
2. Be careful with spelling.
3. Improve choice of words.
4. Always proofread the letter after finishing
writing it.
Margin comments
- Comment [teacher1]: Newton, a 22-year
- Comment [teacher2]: 6 months ago.
- Comment [teacher3]: Newton presented complaining
- Comment [teacher4]: suffers from lethargy
- Comment [teacher5]: He
- Comment [teacher6]: but got no relief.
- Comment [teacher7]: came as follows
- Comment [teacher8]: Newton
- Comment [teacher9]: for IBD.
- Comment [teacher10]: further
Page 9 — RE: Mr. Zach Foster DOB: 25/10/1991
Letter
Dr. Tanya Williams
Respiratory Specialist
Bayview Private Hospital
81 Canyon Road
Bayview
18/10/2014
Dear Dr. Williams,
RE: Mr. Zach Foster DOB: 25/10/1991
I am writing to refer Mr. Foster, a 22-years-old man who is suffering from bronchial asthma.
Your further assessment and management would be highly appreciated.
Mr. Foster has been smoking for 4 years. Regarding his medical history, he is allergic to cats
and hay fever. He suffers from eczema. Furthermore, he was admitted in hospital 2 times. It
is worth mentioning that his sister is asthmatic.
On 11/10/2014, Mr. Foster presented with dyspnea, wheezing, cough and heartburn. He was
non-compliant with medications. I advised him to comply with pulmicort and stop smoking.
Pantoprazole was prescribed for gastro-esophageal reflux disease. CXR and FRE were
ordered.
On examination of Mr. Foster today, he is still suffering from the same symptoms because he
does not cessate smoking and does not take pulmicort regularly. Tests results were normal.
He was advised to take pulmicort erratically and he forget it, he should take it as soon as
possible but do not duplicate the dose. Some strategies regarding smoking cessation were
discussed with him namely, nicotine patch, information brochures and involvement with
supporting groups. An appointment was made within 7 weeks.
In view of the above, diagnosis with bronchial asthma was established. Therefore, I am
referring Mr. Foster for further assessment, lung function, and management.
If you have any queries, please do not hesitate to contact me.
Yours sincerely,
Assessor feedback
Word length 221
Comments There are only minor grammatical inaccuracies
Also, the length is more than desired; however, the
case notes have been covered well and explained
coherently. Overall, the letter meets the
expectations.
Grade B
Advice 1. Pay a little more attention to grammatical range
and accuracy.
2. Try to finish your letter in 200 words.
Margin comments
- Comment [benchmark1]: year
- Comment [benchmark2]: quit
- Comment [benchmark3]: but
- Comment [benchmark4]: forgets
- Comment [benchmark5]: . He
- Comment [benchmark6]: must
- Comment [benchmark7]: of 296 Henley Beach Rd, Underdale, 5032 http://www.benchmarkedu.com.au/oet-writing-correction www.benchmarkedu.com.au/pteoetielts
Page 10
Case notes / writing task (OCR)
You are a doctor at Bayview Medical Clinic. You are assessing a 22-year-old man who has worsening
PATIENT DETAILS:
Name:
Mr Zach Foster
DOB:
25/10/91 (Age 22)
Address:
77 Creek Road, Bayview
Medical history:
Asthma, since age 3 - problematic at times, 2 p
(most recent - 3 years ago)
evious hospital admissions
Eczema
Smoker - 4 years, 10-20/day
Allergies:
Cats
Hayfever
Medications:
Ventolin pr
Pulmicort 200mcg one puff bd
Family history:
Sister (age 18) - asthma
Social history:
Builder, single
Presenting complaint:
- SOB - when playing sport.
For last 3/52 (3wks): - Wheeze & cough - waking Pt at night.
Doctor - T use of Ventolin for symptoms.
Treatment Record
11.10.14
Subjective:
Preventative inhaler (Pulmicort): compliance unclear; claims to use inhaler
some of the time.
gastro-oesophageal reflux disease (GORD).
Burning sensation in lower part of chest after meals - consistent win
Objective:
Chest clear.
Peak flow 500L/min.
Abdomen lax & non-tender.
Tests:
CXR, FBE
Diagnosis:
Treatment:
Unstable asthma, possible trigger GORD
• Ensure compliance with Pulmicort.
• Trial of pantoprazole (PPI) for GORD.
• Discussion about smoking cessation.
• Review 1/52.
18.10.14
Review:
Still smoking.
Non-compliant with Pulmicort - forgets to take it.
PPI - effective, nil side effects.
Test results:
CXR - clear
Treatment:
• Use pantoprazole for another 7/52 (7wks) then review.
• Discussion about Pulmicort missed dosage - take as soon as remember,
• Advice on smoking cessation (e.g., nicotine patch, information brochures,
then back to normal, do not double dose
• Continue current management; refer to respiratory specialist for lung
support groups, etc.).
• Review appointment 7/52.
function & advice about asthma management.
Writing Task:
specialist, for further management of Mr Foster’s asthma. Address the letter to Dr Tanya Williams,
Using the information given in the case notes, write a letter of referral to Dr Williams, a respiratory
Respiratory Specialist, Bayview Private Hospital, 81 Canyon Road, Bayview.

Page 11 — Re: Ms Dolores Hoffman D.O.B: 22/6/1986
Letter
John McLennan
Psychiatrist
Royal Mental Health Clinic
Newtown
29/11/2014
Dear Dr McLennan,
Re: Ms Dolores Hoffman D.O.B: 22/6/1986
I am writing to refer Ms Hoffman, a 27-year-old patient, who presented with signs and
symptoms of reactive depression and anxiety. Your further assessment and management
would be appreciated.
Ms Hoffman is single; however, she was in a long-term relationship with a single male partner
before splitting-up last week. She has no family members in Australia and she works as a sales
assistant in a department store. She is a smoker and a drinker.
On 11/12/2013, she visited me after having fainted and lost her consciousness for 5-10
minutes in the preceeding night. That happened after drinking 2 glasses of wine and several
cocktails at a pub. She visited me several visits after that for other issues and she had been
always anxious in all the visits.
A week ago, she complained that she is experiencing a heavy workload and stress. She
reported having signs and symptoms of repression such as disturbed sleep, loss of appetite,
low libido along with other symptoms of disturbed cognitive functions. I recommended a
referral to a psychiatrist; however, she refused. Temazepam was prescribed for her with a 1
week review scheduled for her.
On review today, the patient informed me that she did not take her medicine and preferred
to avoid drug therapy. Additionally, she agreed to be referred to a psychiatrist.
In view of the above, I am referring Ms Hoffman for further assessment and management.
Please do not hesitate to contact me for any queries.
Yours sincerely,
Doctor
Assessor feedback
Word length 243
Comments There are several minor inaccuracies related to
grammar and word choice. Also, the length is more
than desired, thereby showing lack of effort in
writing information in brief/summary form.
Nevertheless, the letter meets the expectations.
Grade B
Advice 1. Pay a little more attention to grammar and
improve sentences.
2. Be careful of word choice.
3. Try to finish your letter in 200 words.
Margin comments
- Comment [benchmark1]: previous
- Comment [benchmark2]: It
- Comment [benchmark3]: times
- Comment [benchmark4]: always been
- Comment [benchmark5]: was
- Comment [benchmark6]: 1-week
- Comment [benchmark7]: Upon today’s review,
- Comment [benchmark8]: if you have 296 Henley Beach Rd, Underdale, 5032 http://www.benchmarkedu.com.au/oet-writing-correction www.benchmarkedu.com.au/pteoetielts
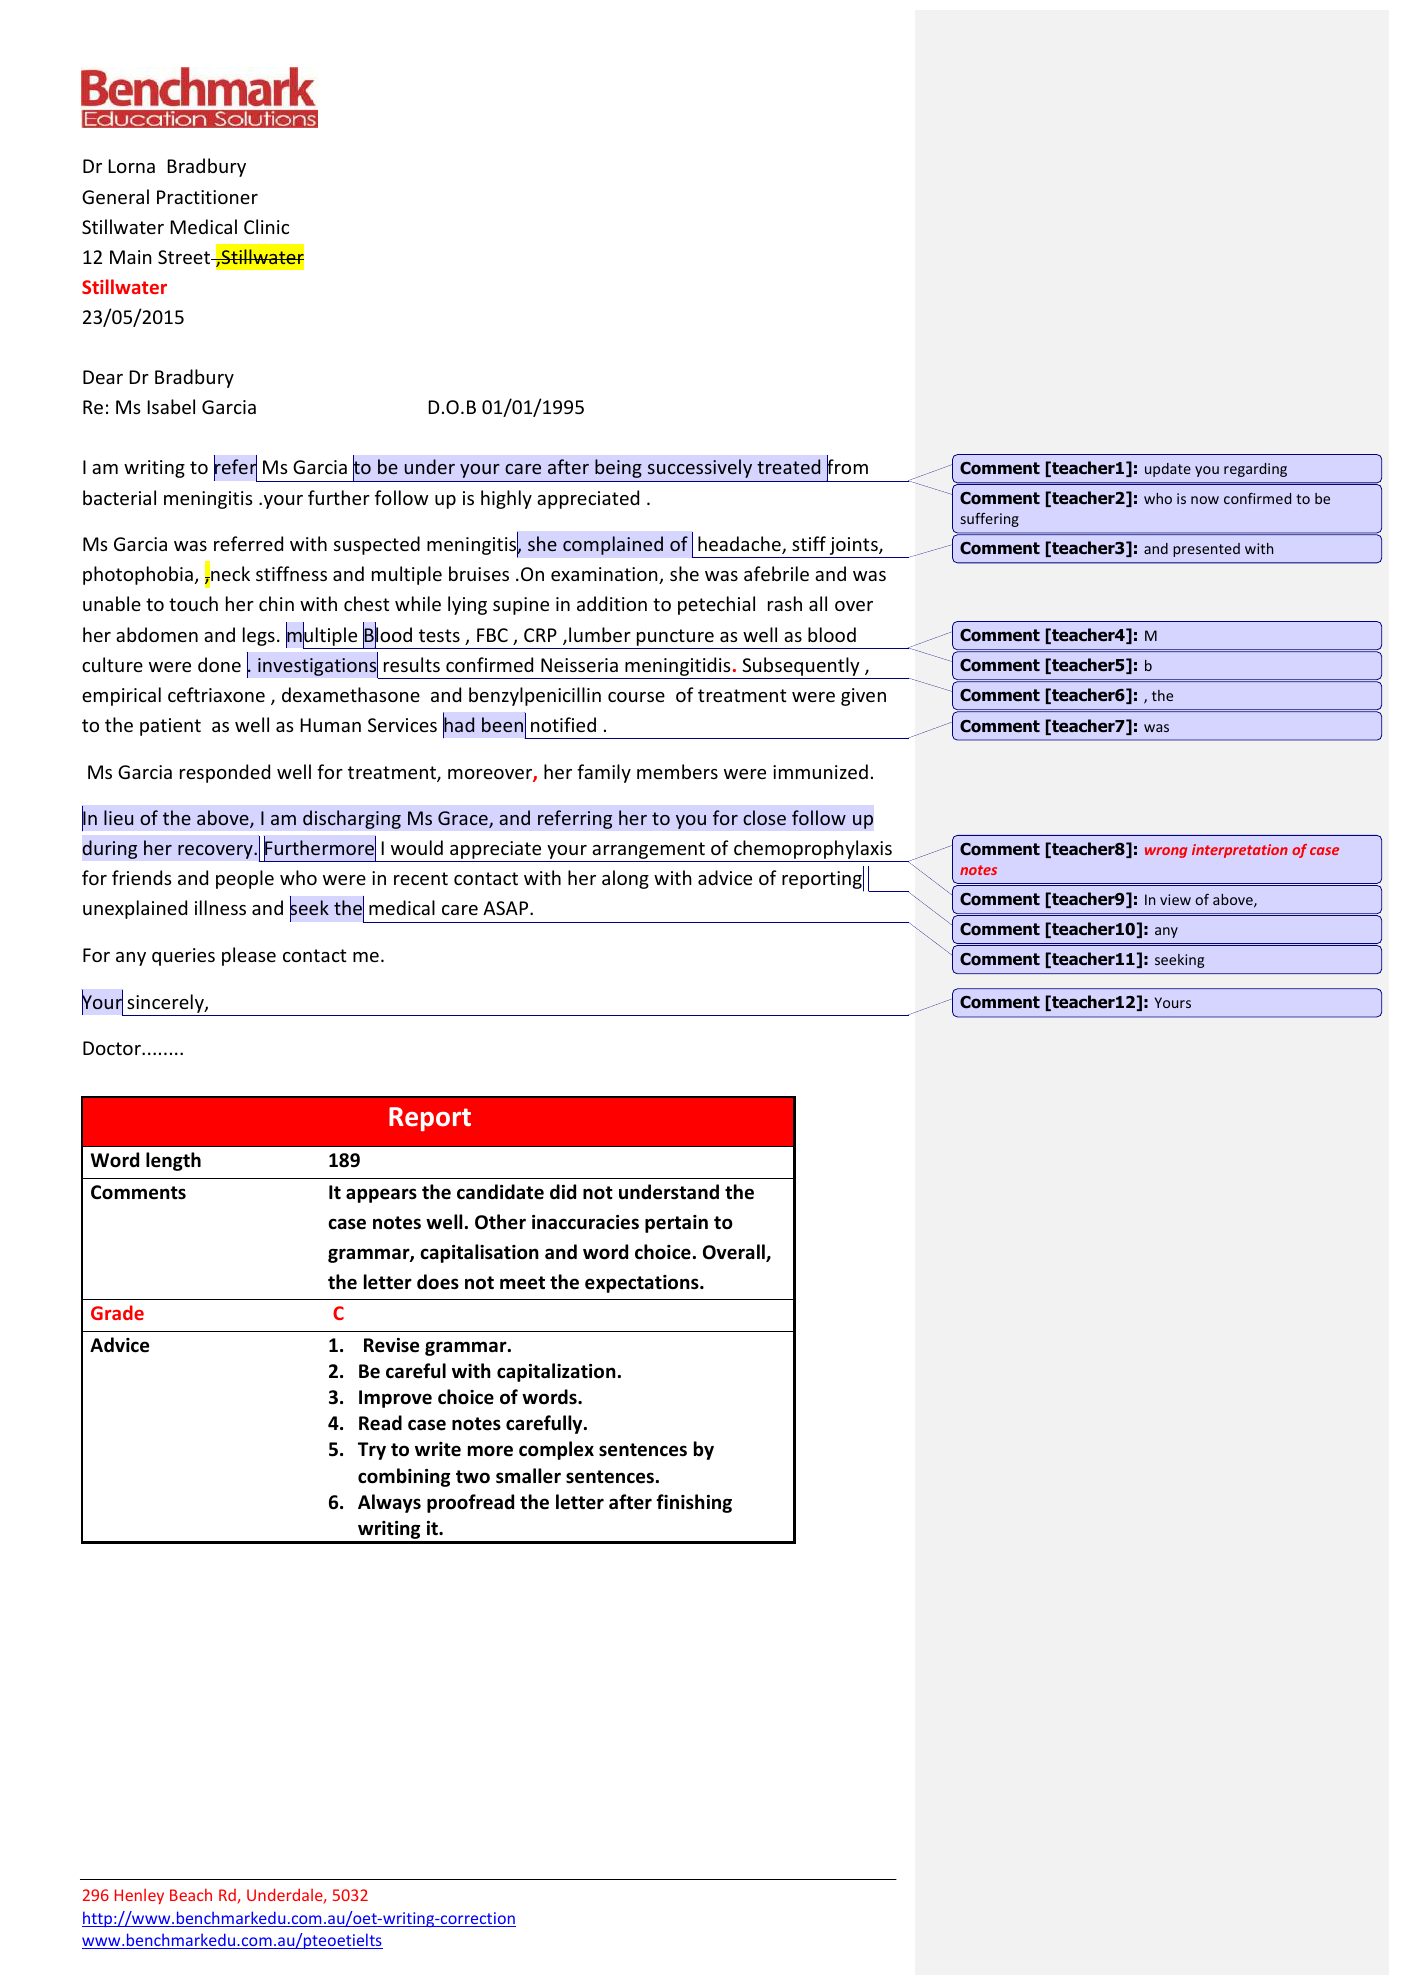
Page 12 — Re: Ms Isabel Garcia D.O.B 01/01/1995
Letter
Dr Lorna Bradbury
General Practitioner
Stillwater Medical Clinic
12 Main Street ,Stillwater
Stillwater
23/05/2015
Dear Dr Bradbury
Re: Ms Isabel Garcia D.O.B 01/01/1995
I am writing to refer Ms Garcia to be under your care after being successively treated from
bacterial meningitis .your further follow up is highly appreciated .
Ms Garcia was referred with suspected meningitis, she complained of headache, stiff joints,
photophobia, ,neck stiffness and multiple bruises .On examination, she was afebrile and was
unable to touch her chin with chest while lying supine in addition to petechial rash all over
her abdomen and legs. multiple Blood tests , FBC , CRP ,lumber puncture as well as blood
culture were done . investigations results confirmed Neisseria meningitidis. Subsequently ,
empirical ceftriaxone , dexamethasone and benzylpenicillin course of treatment were given
to the patient as well as Human Services had been notified .
Ms Garcia responded well for treatment, moreover, her family members were immunized.
In lieu of the above, I am discharging Ms Grace, and referring her to you for close follow up
during her recovery. Furthermore I would appreciate your arrangement of chemoprophylaxis
for friends and people who were in recent contact with her along with advice of reporting
unexplained illness and seek the medical care ASAP.
For any queries please contact me.
Your sincerely,
Doctor…
Assessor feedback
Word length 189
Comments It appears the candidate did not understand the
case notes well. Other inaccuracies pertain to
grammar, capitalisation and word choice. Overall,
the letter does not meet the expectations.
Grade C
Advice 1. Revise grammar.
2. Be careful with capitalization.
3. Improve choice of words.
4. Read case notes carefully.
5. Try to write more complex sentences by
combining two smaller sentences.
6. Always proofread the letter after finishing
writing it.
Margin comments
- Comment [teacher1]: update you regarding
- Comment [teacher2]: who is now confirmed to be suffering
- Comment [teacher3]: and presented with
- Comment [teacher4]: M
- Comment [teacher5]: b
- Comment [teacher6]: , the
- Comment [teacher7]: was
- Comment [teacher8]: wrong interpretation of case notes
- Comment [teacher9]: In view of above,
- Comment [teacher10]: any
- Comment [teacher11]: seeking
- Comment [teacher12]: Yours
Page 13
Case notes / writing task (OCR)
Patient Details
who was referred by her General Practitioner (GP), Dr Bradbury.
you are a doctor working in the Stilwater Hospital Emergency Department. Today you treated Ms Garcia,
DOB:
01.01.1995
Ms Isabel Garcia
fedical history: 2007
29 Greenfield Road, Stillwate
Ilergies:
2014
Unexplained weight gain, Tastress
Dificulty sleeping
Certain washing detergents cause skin irritation.
illy history:
University student (2nd year).
Mother - breast cancer, age 38.
Painful, stilf joints for 1 wk.
Sensitivity to light.
: Headache, neck stiffess, photophobia, rash
T bruising.
On examination:
Bruising L arm.
Afebrile.
Unable to touch chin to chest when lying supine.
Petechial rash abdomen and legs.
Full blood count (FBC), renal function, liver function test (LFT), C-reactive protein
(CRP), lumbar puncture, blood cultures.
Hesults:
C-reactive protein:
White cell count:
150
14.0x10°/L
Lumbar puncture:
Glucose:
White cell count 1000 (elevated)
Protein:
10mg/dl (reduced)
Polymorphonuclear (PMN) predominance
Subsequent microscopy and culture: Neisseria meningitidis
70mg/di (elevated)
Diagnosis:
Bacterial Meningitis.
Ceftriaxone 2g IV bd while awaiting lumbar puncture culture results.
6hrs for 4 days.
Dexamethasone 10mg IV before first dose of antibiotics, then 10mg IV every
Pt responding well to treatment.
Following lumbar puncture results: benzylpenicillin 1.8g IV every 4hrs for 5 days.
Discussed with family re: ensure family immunised.
Department of Human Services notified.
Plan:
Letter to GP, recommend:
Contact close family & friends of Pt:
• Seek medical attention ASAP - observation for any signs of unexplained
• ?chemoprophylaxis for peop
less reguired!
in recent close contact with Pt.
Writing Task:
Using the information given in the case notes, write a letter to Dr Bradbury, the doctor who referred
future. Address the letter to Dr Loma Bradbury, Stillwater Medical Clinic, 12 Main Street, Stillwater.
Ms Garcia, to update her on the patient’s status and follow-up treatment that may be required in the

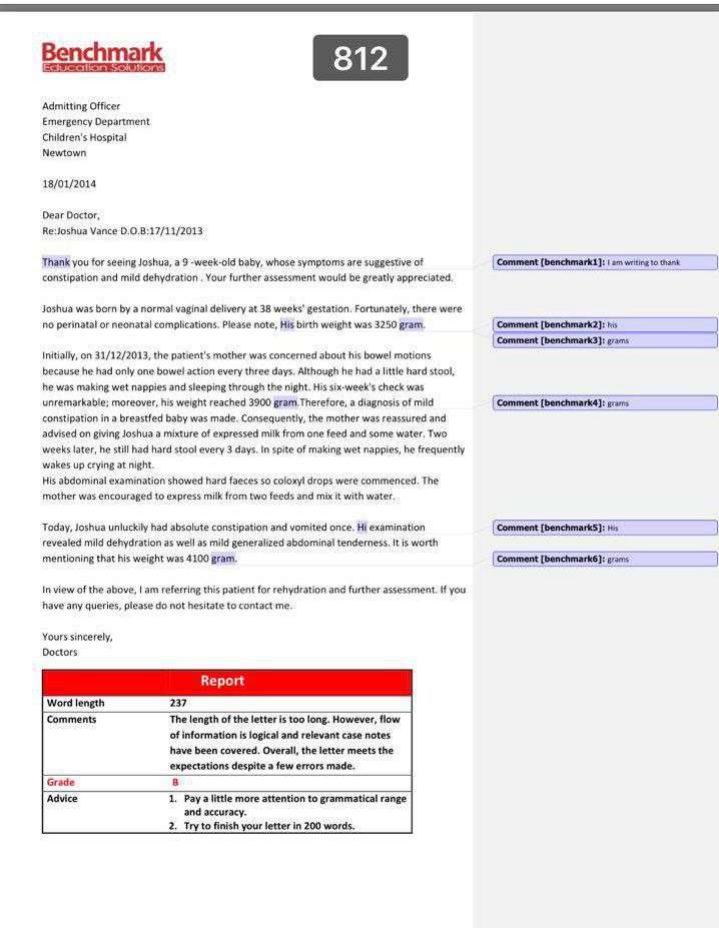
Page 14 — Re: Joshua Vance D.O.B:17/11/2013
Letter (OCR)
812
Admitting Officer
Emergency Department
Children’s Hospital
Newtown
18/01/2014
Dear Doctor,
Re: Joshua Vance D.O.B:17/11/2013
Thank you for seeing Joshua, a 9-week-old baby, whose symptoms are suggestive of
constipation and mild dehydration. Your further assessment would be greatly appreciated
Joshua was born by a normal vaginal delivery at 38 weeks’ gestation. Fortunately, there were
no perinatal or neonatal complications. Please note, His birth weight was 3250 gram.
Initially, on 31/12/2013, the patient’s mother was concerned about his bowel motions
because he had only one bowel action every three days. Although he had a little hard stool,
he was making wet nappies and sleeping through the night. His six-week’s check was
unremarkable; moreover, his weight reached 3900 gram Therefore, a diagnosis of mild
constipation in a breastfed baby was made. Consequently, the mother was reassured and
advised on giving Joshua a mixture of expressed milk from one feed and some water. Two
weeks later, he still had hard stool every 3 days. In spite of making wet nappies, he frequently
wakes up crying at night.
His abdominal examination showed hard faces so coloxyl drops were commenced. The
mother was encouraged to express milk from two feeds and mix it with water.
Today, Joshua unluckily had absolute constipation and vomited once. Hi examination
revealed mild dehydration as well as mild generalized abdominal tenderness. It is worth
mentioning that his weight was 4100 gram.
In view of the above, I am referring this patient for rehydration and further assessment. If you
have any queries, please do not hesitate to contact me.
Yours sincerely,
Doctors
Assessor feedback (OCR)
Word length
237
Comments
The length of the letter is too long. However, flow
of information is logical and relevant case notes
have been covered. Overall, the letter meets the
expectations despite a few errors made.
Grade
Advice
- Pay a little more attention to grammatical range
and accuracy. - Try to finish your letter in 200 words.
Margin comments
- Comment [benchmark1]: I am writing to thank
- Comment [benchmark2]: his
- Comment [benchmark3]: grams
- Comment [benchmark4]: grans
- Comment [benchmark5]: His
- Comment [benchmark6]: grams
Page 15 — Re: Jamie Brown, 5 years of age
Letter (OCR)
Focalien SaVion:
644
Dr F Goldman
171 Victoria St
Northfield
20/03/2010
Dear Dr Goidman,
Re: Jamie Brown, 5 years of age
Thank you for seeing Jamie whose symptoms are consistent with
post streptococcal nephritis accompained by early renal failure. Your further assessment
would be greatly appreciated.
Initially, on 25/02/2010, Jamie had presented with a fever, sore throat, husky voice and
being irritable. His signs and symptoms were suggestive of tonsillitis; thus, pencillini was
commenced. Three weeks later, his mother noticed increase lethergy, tiredness and brown
Moreover, his urine analysis revealed microscopic haematuria; therefore, a diagnosis of
urine. On examination, Jamie had tonsiller hypertrophy and a low blood pressure reading.
and a review appointment was scheduled.
post streptococcal nephritis versus UTI was considered. Investigations were carried out
Today, the patient was still asymptomatic, but his urinalysis demonstrated macroscopic
haematuria. Regarding the tests results, ASOT, urea and creatinine levels were elevated.
Please note. RBC of renal origin were in his MSU test
In view of the above, I am referring this patient for further management, if you have any
querses, please do not hesitate to contact me.
Yours sincerely,
Doctor
Assessor feedback (OCR)
Word length
164
Comments
There are only minor inaccuracies pertaining to
spelling and word choice. Also, the length is
shorter than minimum 180 words. However, these
do not reduce communication.
Grade
B+
Advice
- Improve word choice.
- Be careful of spelling.
- Ensure that the length is at least 180 words.
- Keep up the good work!
Margin comments
- Comment [bnchmrk1]: accompanied
- Comment [bnchmrk2]: penicilin
- Comment [bnchmrk3]: lethargy
- Comment [bnchmrk4]: According to
- Comment [bnchmrk5]: a bit undear!

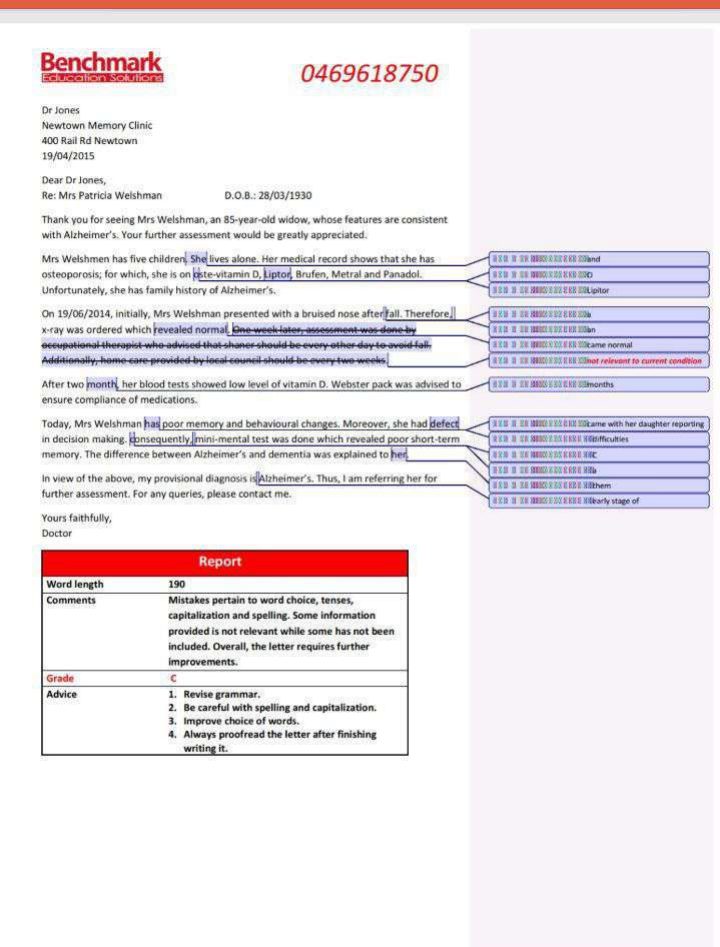
Page 16 — Re: Mrs Patricia Welshman
Letter (OCR)
Dr Jones
Newtown Memory Clinic
400 Rail Rd Newtown
19/04/2015
Dear Dr Jones,
Re: Mrs Patricia Welshman
D.O.B.: 28/03/1930
Thank you for seeing Mrs Welshman, an 85-year-old widow, whose features are consistent
with Alzheimer’s. Your further assessment would be greatly appreciated.
Mrs Welshmen has five children, She lives alone. Her medical record shows that she has
osteoporosis; for which, she is on oste-vitamin D, Liptor, Brufen, Metral and Panadol.
Unfortunately, she has family history of Alzheimer’s.
On 19/05/2014, initially, Mrs Welshman presented with a bruised nose after fall. Therefore.
x-ray was ordered which revealed normal one we
ok lates
at was done by
dvised that si
very e
ay to avoid fall.
831 I IN BEEN KRicame normal
evided by local t
els
AX I EX WIRESEEInor relevant to cur
After two month, her blood tests showed low level of vitamin D. Webster pack was advised to
ensure compliance of medications.
Today, Mrs Welshman has poor memory and behavioural changes, Moreover, she had defect
WE I EI HE 222HE Stame with her daughter reporting
in decision making. consequently mini-mental test was done which revealed poor short-term
memory. The difference between Alzheimer’s and dementia was explained to her.
In view of the above, my provisional diagnosis is Alzheimer’s. Thus, I am referring her for
further assessment. For any queries, please contact me.
HER I BE HEEDLEREE WAkarly stage of
Yours faithfully,
Doctor
Assessor feedback (OCR)
Word length
190
Comments
Mistakes pertain to word choice, tenses,
capitalization and spelling. Some information
provided is not relevant while some has not been
included. Overall, the letter requires further
improvements.
Grade
Advice
- Revise grammar.
- Be careful with spelling and capitalization.
- Improve choice of words.
- Always proofread the letter after finishing
writing it.
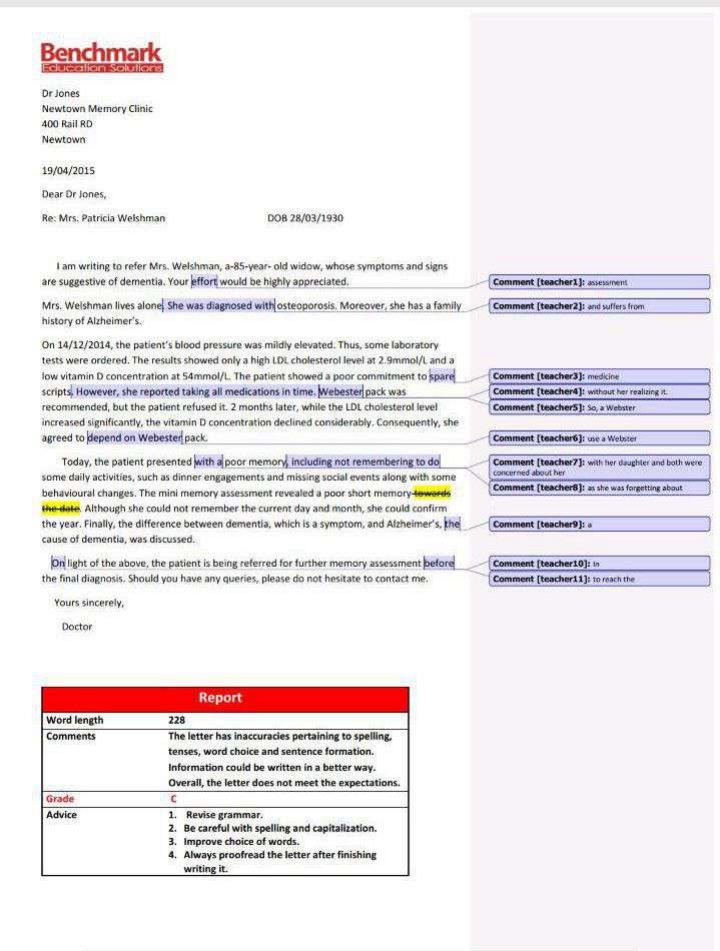
Page 17 — Re: Mrs. Patricia Welshman
Letter (OCR)
Dr Jones
Newtown Memory Clinic
400 Rail RD
Newtown
19/04/2015
Dear Dr Jones,
Re: Mrs. Patricia Welshman
DOB 28/03/1930
I am writing to refer Mrs. Welshman, a-85-year-old widow, whose symptoms and signs
are suggestive of dementia. Your effort would be highly appreciated.
Mrs. Welshman lives alonel She was diagnosed with osteoporosis. Moreover, she has a family
history of Alzheimer’s.
On 14/12/2014, the patient’s blood pressure was mildly elevated. Thus, some laboratory
tests were ordered. The results showed only a high LDL cholesterol level at 2.9mmol/L and a
low vitamin D concentration at 54mmol/L. The patient showed a poor commitment to spare
scripts, However, she reported taking all medications in time. Webester pack was
recommended, but the patient refused it. 2 months later, while the LDL cholesterol level
increased significantly, the vitamin D concentration declined considerably. Consequently, she
agreed to depend on Webester pack.
Today, the patient presented with a poor memory, including not remembering to do
some daily activities, such as dinner engagements and missing social events along with some
concerned about her
behavioural changes. The mini memory assessment revealed a poor short memory tewards
the date
Although she could not remember the current day and month, she could confirm
the year. Finally, the difference between dementia, which is a symptom, and Alzheimer’s, the
cause of dementia, was discussed.
On light of the above, the patient is being referred for further memory assessment pefore
the final diagnosis. Should you have any queries, please do not hesitate to contact me.
Yours sincerely,
Doctor
Assessor feedback (OCR)
Word length
228
Comments
The letter has inaccuracies pertaining to spelling.
tenses, word choice and sentence formation.
Information could be written in a better way.
Overall, the letter does not meet the expectations.
Grade
Advice
- Revise grammar.
- Be careful with spelling and capitalization.
- Improve choice of words.
- Always proofread the letter after finishing
writing it.
Margin comments
- Comment [teacher1]: assessment :
- Comment [teacher2]: and suffers from
- Comment [teacher3]: medicine
- Comment [teacher4]: without her realizing it
- Comment [teacher5]: So, a Webster
- Comment [teacherG]: use a Webster
- Comment [teacher7]: with her daughter and both were
- Comment [teacher8]: as she was forgetting about
- Comment [teacher9]: a
- Comment [teacher10]: in
- Comment [teacher11]: to reach the
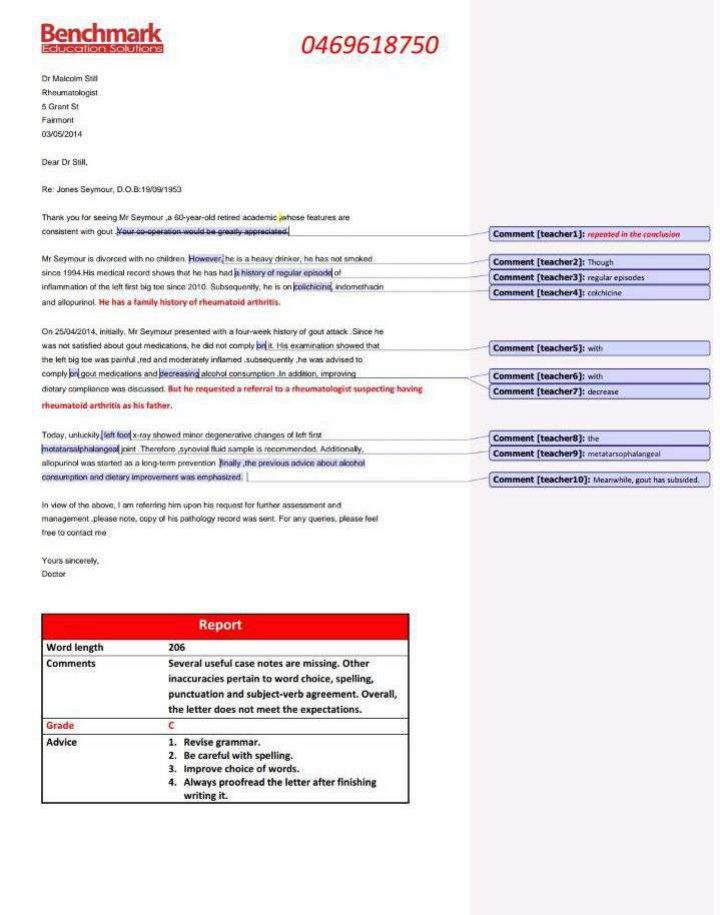
Page 18 — Re: Jones Seymour, D.O.B:19/09/1953
Letter (OCR)
Eetection Soluters
Or Malcolm Still
Rheumatologist
5 Grant St
Fairmont
03/05/2014
Dear Dr Still.
Re: Jones Seymour, D.O.B:19/09/1953
Thank you for seeing Mr Seymour, a 60-year-old retired ac
tic whose features are
consistent with gout Your
Mr Seymour is divorced with no children. However he is a heavy drinker, ho has not smoked
since 1994 His medical record shows that he has had a history of regular episodd of
inflammation of the lelt first big toe since 2010. Subsequently, he is on (colchicine, indomethacin
and allopurinol. He has a family history of rheumatoid arthritis.
On 25/04/2014, initially. Mr Seymour presented with a four-week history of gout attack. Since he
was not satisfied about gout medications, he did not comply brit. His examination showed that
the left big toe was painful, red and moderately inflamed subsequently he was advised to
comply belgout medications and decreasing alcohol consumption In addison. improving
diotary compliance was decussed. But he requested a referral to a rheumatologist suspecting having
rheumatoid arthritis as his father.
Today, unluckily [left food x-ray showed minor degenerative changes of left first
metatarsalphalangeal joint Therefore synovial fluid sample is recommended. Additionally,
stopurinol was started as a long-term prevention finally, the previous advice about alcohol
consumption and dietary improvement was emphosized.
In vow of the above, I am referring him upon his request for further assessment and
management please note, copy of his pathology record was sent. For any queries, please feel
free to contact me
Yours sincerely,
Doctor
Assessor feedback (OCR)
Word length
206
Comments
Several useful case notes are missing. Other
inaccuracies pertain to word choice, spelling,
punctuation and subject-verb agreement. Overall,
the letter does not meet the expectations.
Grade
Advice
- Revise grammar.
- Be careful with spelling.
- Improve choice of words.
- Always proofread the letter after finishing
writing it.
Margin comments
- Comment [teacher1]: repented in the conclusion
- Comment [teacher2]: Though
- Comment [teacher3]: regular episodes
- Comment [teacher4]: colchicine
- Comment [teacherS): with
- Comment [teacher6]: with
- Comment [teacher7]: decrease
- Comment [teacher®]: the
- Comment [teacher9]: metatarsophalangeal
- Comment [teacher10]: Meanwhile, gout has subsided.
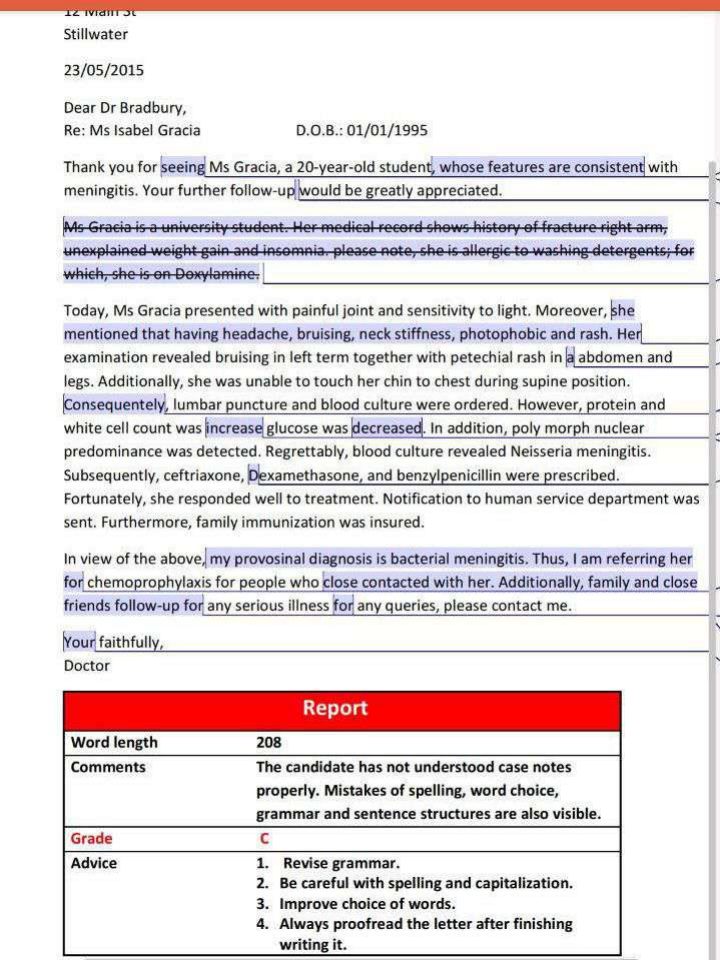
Page 19 — Re: Ms Isabel Gracia
Letter (OCR)
Stillwater
23/05/2015
Dear Dr Bradbury,
Re: Ms Isabel Gracia
D.O.B.: 01/01/1995
Thank you for seeing Ms Gracia, a 20-year-old student, whose features are consistent with
meningitis. Your further follow-up would be greatly appreciated.
Ms Gracia is a university student. Her medical record shows history of fracture right arm,
unexplained weight gain and insomnia. please note, she is allergic to washing detergents; for
which, she is on Doxylamine.
Today, Ms Gracia presented with painful joint and sensitivity to light. Moreover, she
mentioned that having headache, bruising, neck stiffness, photophobic and rash. Her
examination revealed bruising in left term together with petechial rash in a abdomen and
legs. Additionally, she was unable to touch her chin to chest during supine position.
Consequentely, lumbar puncture and blood culture were ordered. However, protein and
white cell count was increase glucose was decreased. In addition, poly morph nuclear
predominance was detected. Regrettably, blood culture revealed Neisseria meningitis.
Subsequently, ceftriaxone, Dexamethasone, and benzylpenicillin were prescribed.
Fortunately, she responded well to treatment. Notification to human service department was
sent. Furthermore, family immunization was insured.
In view of the above, my provosinal diagnosis is bacterial meningitis. Thus, I am referring her
for chemoprophylaxis for people who close contacted with her. Additionally, family and close
friends follow-up for any serious illness for any queries, please contact me.
Your faithfully,
Doctor
Assessor feedback (OCR)
Word length
208
Comments
The candidate has not understood case notes
properly. Mistakes of spelling, word choice,
grammar and sentence structures are also visible.
Grade
C
Advice
- Revise grammar.
- Be careful with spelling and capitalization.
- Improve choice of words.
- Always proofread the letter after finishing
writing it.
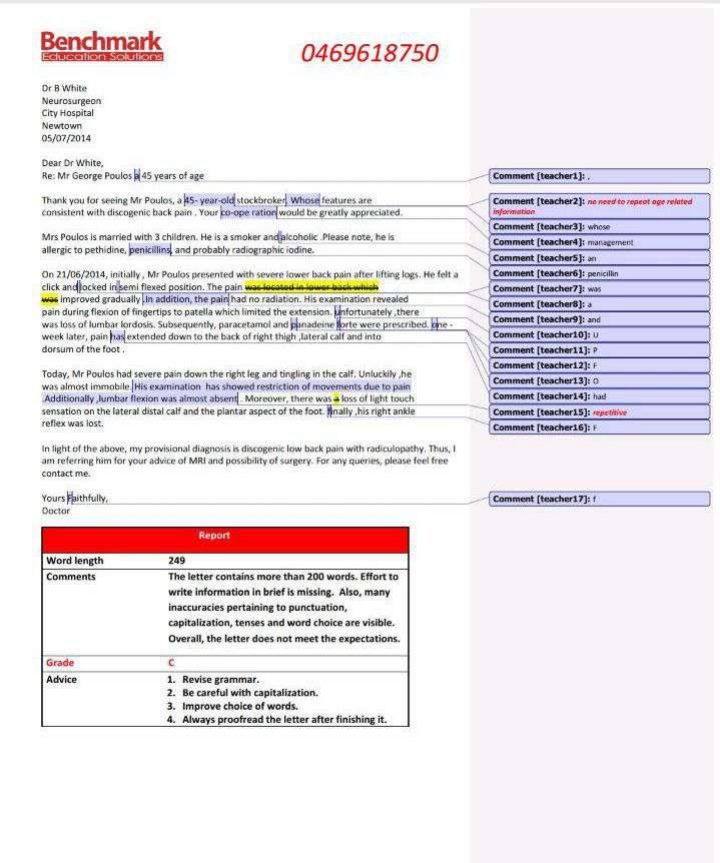
Page 20 — Re: Mr George Poulos a 45 years of age
Letter (OCR)
uliens
Dr B White
Neurosurgeon
City Hospital
Newtown
05/07/2014
Dear Dr White,
Re: Mr George Poulos a 45 years of age
Thank you for seeing Mr Poulos, a 85- year-old stockbroker. Whose features are
consistent with discogenic back pain. Your co-ope ration would be greatly appreciated.
mormation
Mrs Poulos is married with 3 children. He is a smoker and alcoholic. Please note, he is
allergic to pethidine, penicillins, and probably cadiographic iodine.
On 21/06/2014, initially, Mr Poulos presented with severe lower back pain after lifting logs. He felt a
click andlocked in semi flexed position. The pain was located in lower back which
was improved gradually In addition, the pain had no radiation. His examination revealed
pain during flexion of fingertips to patella which limited the extension. unfortunately, there
was loss of lumbar lordosis. Subsequently, paracetamol and pinadee forte were prescribed, one -
week later, pain has extended down to the back of right thigh lateral calf and into
dorsum of the foot.
Today, Mr Poulos had severe pain down the right leg and tingling in the calf. Unluckily, he
was almost immobile /His examination has sho
d restriction of movements due to pain
Additionally, Jumbar flexion was almost absent. Moreover, there was a loss of light touch
sensation on the lateral distal calf and the plantar aspect of the foot. finally, his right ankle
reflex was lost.
In light of the above, my provisional diagnosis is discogenic low back pain with radiculopathy, Thus, I
contact me.
am referring him for your advice of MRI and possibility of surgery. For any queries, please feel free
Yours Faithfully.
Doctor
Assessor feedback (OCR)
Word length
249
Comments
The letter contains more than 200 words. Effort to
write information in brief is missing. Also, many
inaccuracies pertaining to punctuation,
capitalization, tenses and word choice are visible.
Overall, the letter does not meet the expectations.
Grade
Advice
- Revise grammar.
- Be careful with capitalization.
- Improve choice of words.
- Always proofread the letter after finishing it.
Margin comments
- Comment [teacher]):.
- Comment [teacher2]: no need to repeat age related
- Comment [teacher3]: whose
- Comment [teacher4]: management
- Comment [teacher5]: an
- Comment [teacher6]: penicilin
- Comment [teacher7]: wis
- Comment [teacher®]: a
- Comment [teacher9]: and
- Comment [teacher10]: U
- Comment [teacher11]: P
- Comment [teacher12]: F
- Comment [teacher13]: 0
- Comment [teacher14]: had
- Comment [teacher15]: repetitive
- Comment [teacher16]: F
- Comment [teacher17]: f
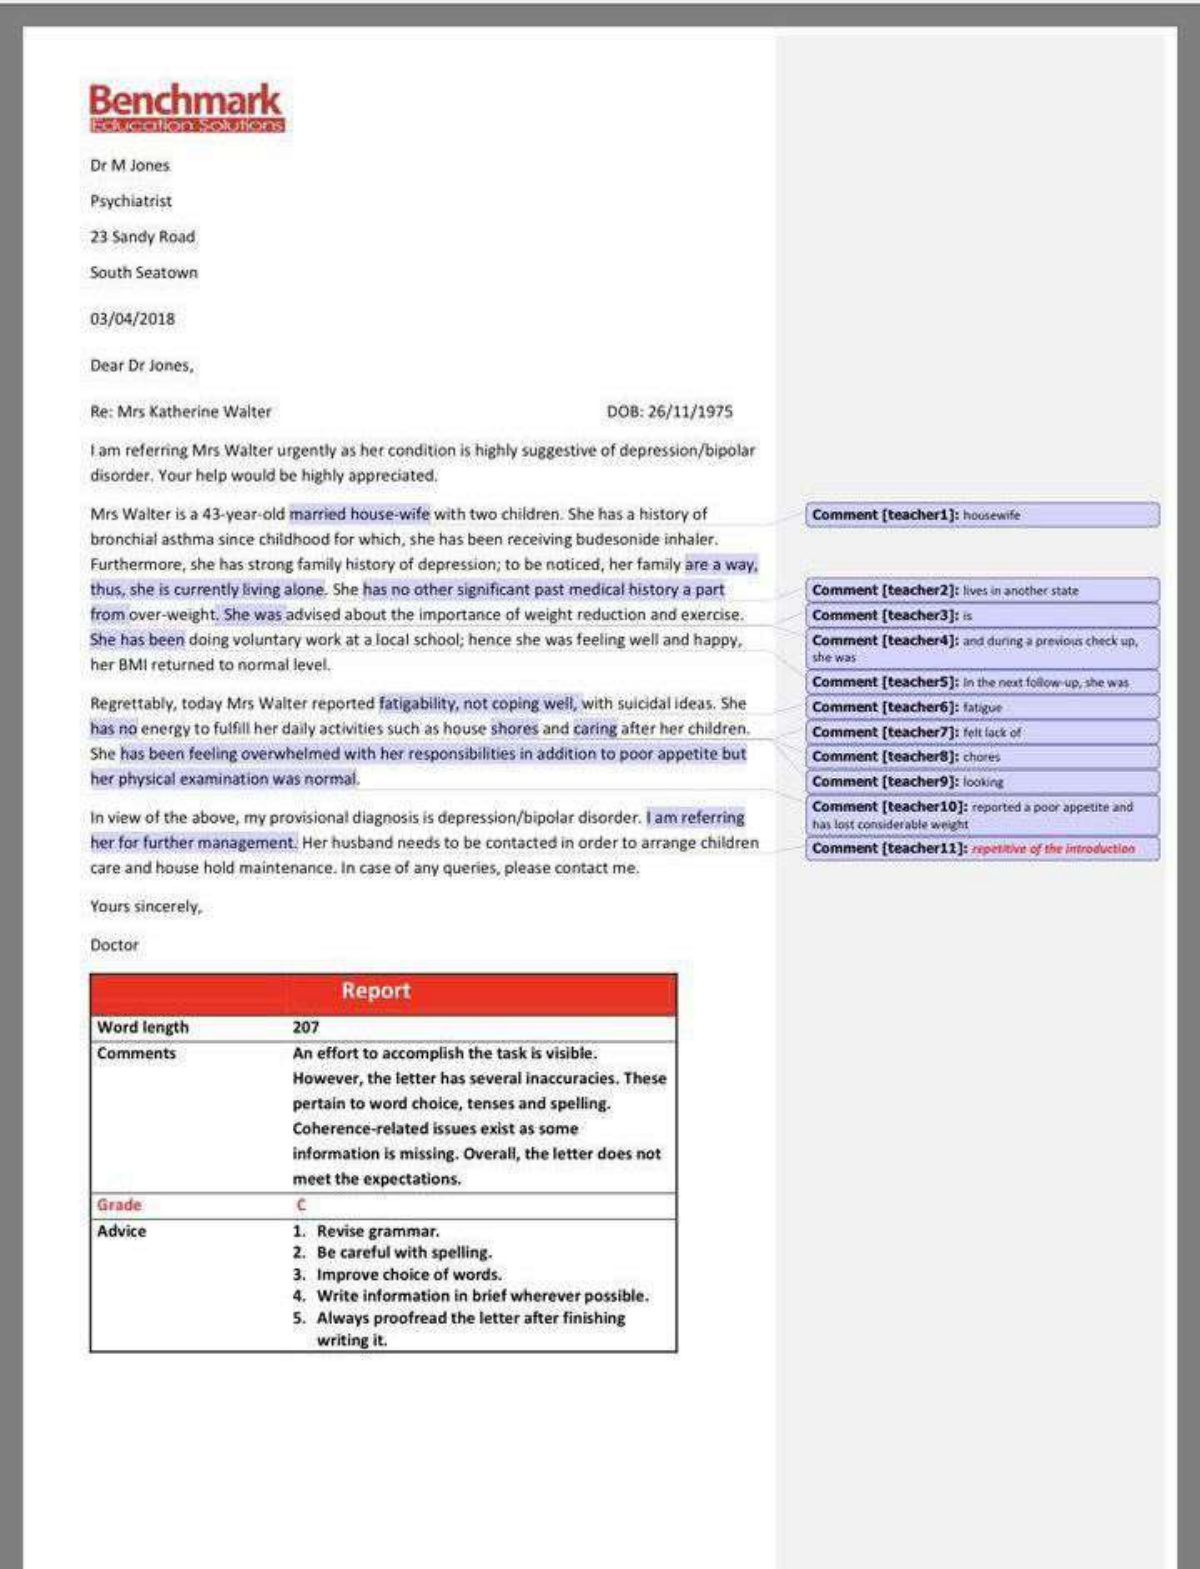
Page 21 — Re: Mrs Katherine Walter
Letter (OCR)
Dr M Jones.
Psychiatrist
23 Sandy Road
South Seatown
03/04/2018
Dear Dr Jones,
Re: Mrs Katherine Walter
DOB: 26/11/1975
Lam referring Mrs Walter urgently as her condition is highly suggestive of depression/bipolar
disorder, Your help would be highly appreciated.
Mrs Walter is a 43-year-old married house-wife with two children. She has a history of
bronchial asthma since childhood for which, she has been receiving budesonide inhaler.
Furthermore, she has strong family history of depression; to be noticed, her family are a way,
thus, she is currently living alone. She has no other significant past medical history a part
from over-weight. She was advised about the importance of weight reduction and exercise.
She has been doing voluntary work at a local school; hence she was feeling well and happy.
her BMI returned to normal level.
she was
Regrettably, today Mrs Walter reported fatigability, not coping well, with suicidal ideas. She
has no energy to fulfill her daily activities such as house shores and caring after her children.
She has been feeling overwhelmed with her responsibilities in addition to poor appetite but
her physical examination was normal.
In view of the above, my provisional diagnosis is depression/bipolar disorder. I am referring
has lost considerable weight
her for further management. Her husband needs to be contacted in order to arrange children
care and house hold maintenance. In case of any queries, please contact me.
Yours sincerel
Doctor
Assessor feedback (OCR)
Word length
207
Comments
An effort to accomplish the task is visible.
However, the letter has several inaccuracies. These
pertain to word choice, tenses and spelling.
Coherence-related issues exist as some
information is missing. Overall, the letter does not
meet the expectations.
Grade
Advice
- Revise grammar.
- Be careful with spelling.
- Improve choice of words.
- Write information in brief wherever possible.
- Always proofread the letter after finishing
writing it.
Margin comments
- Comment [teachert]: housewife
- Comment [teacher2]: lives in another state
- Comment [teacher3]: is
- Comment [teacher4]: and during a previous check up
- Comment [teacherS]; in the next follow up, she was
- Comment [teacher6]: fatigue
- Comment [teacher7]: felt lack of
- Comment [teacher8]: chores
- Comment [teacher9]: looking
- Comment [teacher10]: reported a poor appetite and
- Comment [teacher11]: m
Page 22 — Re: Mrs. Mary Clarke, D.O.B.: 17/09/1960
Letter (OCR)
Dr Penny Clifton
Thoracic Surgeon
Department Of Cardiothoracic Surgery
Central Hospital
Main Street
Stillwater
22/08/2015
Dear Dr. Clifton.
Re: Mrs. Mary Clarke, D.O.B.: 17/09/1960
I am writing to refer Mrs. Clarke who has demonstrated features suggestive of bronchogenic
carcinoma. Your help would be highly appreciated.
Mrs. Clarke is an office clerk and married. She is a heavy smoker for more than 30 years with
consumption of 30-35 cigarettes per day. Moreover, she has no allergies and her mother died
from laryngeal carcinoma. She presented once with sore throat upon which she was
prescribed Augmantin.
On review today, Mrs. Clarke has been suffering from dry non-productive cough with no
haemoptysis for the last 7 weeks. Associated with chest pain (heaviness) and shortness of
breath which is more noticeable during night, however she can exercise well, do her shopping
and walking. Respiratory examination revealed right mid-zone consolidation accompanied
with monophonic wheeze. Other systems’ examination were normal; no cyanosis, ne-cervical
lymphadenopathy and no hoarseness of voice. Chest X-ray and CT scan showed right middle
examinations
lobe atelectasis with enlarged right hilum.
In view of the above, my provisional diagnosis is bronchogenic carcinoma. I am referring her
for further investigations (bronchoscopy with biopsy) and assessment. If you have any query,
please contact me.
Yours sincerely,
Doctor
Assessor feedback (OCR)
Word length
185
Comments
Some issues pertaining to sentence formation and
word choice are visible. There are mistakes of
tenses and punctuation as well. Overall, the letter
requires further improvements.
Grade
C+
Advice
- Revise grammar and sentence formation.
- Improve word choice.
- Always proofread your letter after finishing it.
Margin comments
- Comment [bnchmrk1]: has been
- Comment [bnchmrk2]: associated
- Comment [bnchmrk3]: systemic and respiratory
- Comment [bnchmrk4]:, and there was
- Comment [bnchmrk5]: or
Page 23 — Re: Mr Michael Weir, D.O.B:20/09/1970
Letter (OCR)
Dr M McLaren
Neurologist
Suite 3
67 The Cewscent
Newtown
09/08/2014
Dear Dr McLaren,
Re: Mr Michael Weir, D.O.B:20/09/1970
Thank you for seeing Mr Weir, a 44- year-old real estate agent, Whose features are
consistent with multiple sclerosis. Your co-operation would be greatly appreciated.
Mr Weir is married with 3 children. He is a smoker his medical record shows depression, for
which,he is on Zoloft.
On 29/06/2014, initially, Mr McLaren presented with stress and tiredness. Subsequently,
blood tests were ordered. One-week later, he complained of weakness in the left leg. His
examination revealed low WBC, RBC, Hb and Hct. Additionally, his BMI increased up to
28.5. Consequently, he was advised to decrease weight and quitting smoking. In addition, he
should doing a regular exercise and watching his cholesterol level.
Today, Mr Weir complained of dizziness and two recent blackouts. Moreover, he had labile
mood, tingling in both hands, breathless, occasional constipation, and shortness of the
energy. Unfortunately, he had loss of sensation on both hands. In addition, left patellar
reflex was diminished. Therefore, head and lumbar spinal CT were ordered.
In view of the above, my provisional diagnosis is multiple sclerosis. Thus, I am referring him
for full neurological assessment and MRI. For any queries, please feel free to contact me.
Yours Sincerely,
Doctor
Assessor feedback (OCR)
Word length
194
Comments
Mistakes pertain to word choice, capitalization and
sentence structures. Overall, the letter requires
further improvements.
Grade
C+
Advice
- Revise grammar.
- Be careful with capitalization.
- Improve choice of words.
- Always proofread the letter after finishing
writing it.
Page 24 — Re: Mrs Mary Clarke D.O.B:17/09/1960
Letter (OCR)
Bauer
aulons
679
Dr Penny Clifton
Thoracic Surgeon
Department Of Cardiothoracic surgery
Central Hospital
Main Street
Stillwater
22/08/2015
Dear Dr Clifton,
Re: Mrs Mary Clarke D.O.B:17/09/1960
Thank you for seeing Mrs Clarke, a 54-year-old office clerk, whose symptoms are suggestive
of bronchogenic carcinoma. Your further assessment would be greatly appreciated.
Mrs Clarke, who is a married women, lives with her husband and son. Please note, she is a
heavy smoker and she has no known allergies. Her mother died from laryngeal carcinoma
while her father was suffering from a mining related lung disease.
Initially, on 04/07/2015, the patient had presented with a sore throat, fever, cough and body
aches. Therefore, Augmentin was commenced.
On today’s visit, Mrs Clarke complained of a dry non-productive cough with no haemoptysis.
Additionally, there was mild shortness of breath especially at night associated with a
heaviness sensation in the chest. On examination, there were signs of conolidation
accompanied by monophonic wheezes in the right mid-zone. The X-ray and CT revealed
right middle lobe atelectasis and enlarged right hilum. Consequently, she was counselled on
the potential diagnosis together with the need for further investigations.
In view of the above, I am referring this patient for a bronchoscopy and biopsy If you have
any queries, please donot hesitate to contact me.
Yours sincerely,
Doctor
Assessor feedback (OCR)
Word length
189
Comments
Mistakes pertain to spelling, capitalisation and
preposition. However, flow of information is
logical and relevant case notes have been covered.
Overall, the letter meets the expectations.
Grade
B+
Advice
- Revise grammar.
- Improve word choice.
- Be careful of spelling.
Margin comments
- Comment [bnchmrk1]: woman
- Comment [onchmrk2]: is married and
- Comment [bnchmrk3]: but
- Comment [bnchmrk4]: of
- Comment [bnchmrkS]: suffered
- Comment [bnchmrk6]: consoldation
- Comment [bnchmrk7]: x
Page 25 — Re: Mr Zach Foster
Letter (OCR)
81 Canyon Road
Bayview
18/10/14
Dear Dr Williams,
Re: Mr Zach Foster
D.O.B: 25/10/1991
Thank you for seeing Mr Foster, a 22-year-old builder, who is presenting with bronchial
Comment
asthma. Your further investigations and management would be greatly appreciated.
Mr Foster is single. He has been smoking for four years. His medical record shows that he has
been complaining of bronchial asthma since 1994. Consequently, he has been using ventolin
and pulmicort. Please note, he is allergic to cats and hay fever.
Initially, Mr Foster complained of shortness of breath during playing sport. Moreover, he
mentioned wheeze and cough which waking him at night. On 11/10/2014, he presented with
Comment
features consistent with gastro-esophageal disease. His examination was unremarkable.
Comment
Therefore, pantoprazole was prescribed. Additionally, he was advised to stop smoking
together with good compliance on pulmicort.
Comment
Comment
Today, Mr Foster mentioned that he is still smoking. In addition, he was not complaint on
Comment
pulmicort. His blood tests as well as chest X-ray were normal. Subsequently, pantoprazole
Comment I
was prescribed for another seven weeks. Furthermore, he was advised again to stop smoking
and good compliance on pulmicort.
and medicatio
In view of the above, my diagnosis is bronchial asthma. Thus I am referring him for further
management and lung function test. For any queries, please contact me.
Yours sincerely,
Doctor
Assessor feedback (OCR)
Word length
197
Comments
Mistakes mainly pertain to word choice and
sentence formation. Nevertheless, the letter meets
the expectations.
Grade
B
Advice
- Revise grammar and sentence formation.
- Be careful of capitalisation.
- Improve word choice.
Margin comments
- Comment [
- Comment [
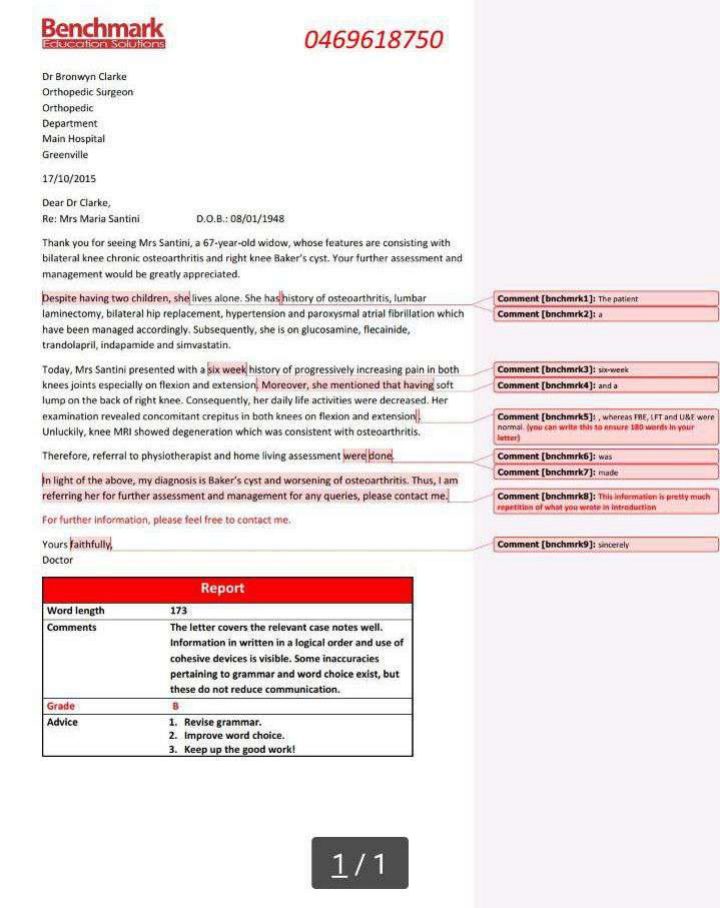
Page 26 — Re: Mrs Maria Santini
Letter (OCR)
Dr Bronwyn Clarke
Orthopedic Surgeon
Orthopedic
Department
Main Hospital
Greenville
17/10/2015
Dear Dr Clarke,
Re: Mrs Maria Santini
D.O.B.: 08/01/1948
Thank you for seeing Mrs Santini, a 67-year-old widow, whose features are consisting with
bilateral knee chronic osteoarthritis and right knee Baker’s cyst. Your further assessment and
management would be greatly appreciated.
Despite having two children, she lives alone. She has history of osteoarthritis, lumbar
laminectomy, bilateral hip replacement, hypertension and paroxysmal atrial fibrillation which
have been managed accordingly. Subsequently, she is on glucosamine, flecainide,
trandolapril, indapamide and simvastatin.
Today, Mrs Santini presented with a six week history of progressively increasing pain in both
knees joints especially on flexion and extension, Moreover, she mentioned that having soft
lump on the back of right knee. Consequently, her daily life activities were decreased. Her
examination revealed concomitant crepitus in both knees on flexion and extension.
Unluckily, knee MRI showed degeneration which was consistent with osteoarthritis.
normal. (you can write this to ensure 180 wards in your
latter)
Therefore, referral to physiotherapist and home living assessment were done
In light of the above, my diagnosis is Baker’s cyst and worsening of osteoarthritis. Thus, I am
referring her for further assessment and management for any queries, please contact me.
repetition of what you weate in introduction
For further information, please feel free to contact me.
Yours faithfully,
Doctor
Assessor feedback (OCR)
Word length
173
Comments
The letter covers the relevant case notes well.
Information in written in a logical order and use of
cohesive devices is visible. Some inaccuracies
pertaining to grammar and word choice exist, but
these do not reduce communication.
Grade
Advice
- Revise grammar.
- Improve word choice.
- Keep up the good work!
1/1
Margin comments
- Comment [bnchmrk1]: The patient
- Comment [bnchmrk2]: a
- Comment [bnchmrk3]: six-week
- Comment [bnchmrk4]: and a
- Comment [bnchmrkS]:, whereas FBE, LFT and U&E were
- Comment [bnchmrk6]: was
- Comment [bnchmrk7): made
- Comment [bnchmrk8]: This information is pretty much
- Comment [bnchmrk9]: sincerely
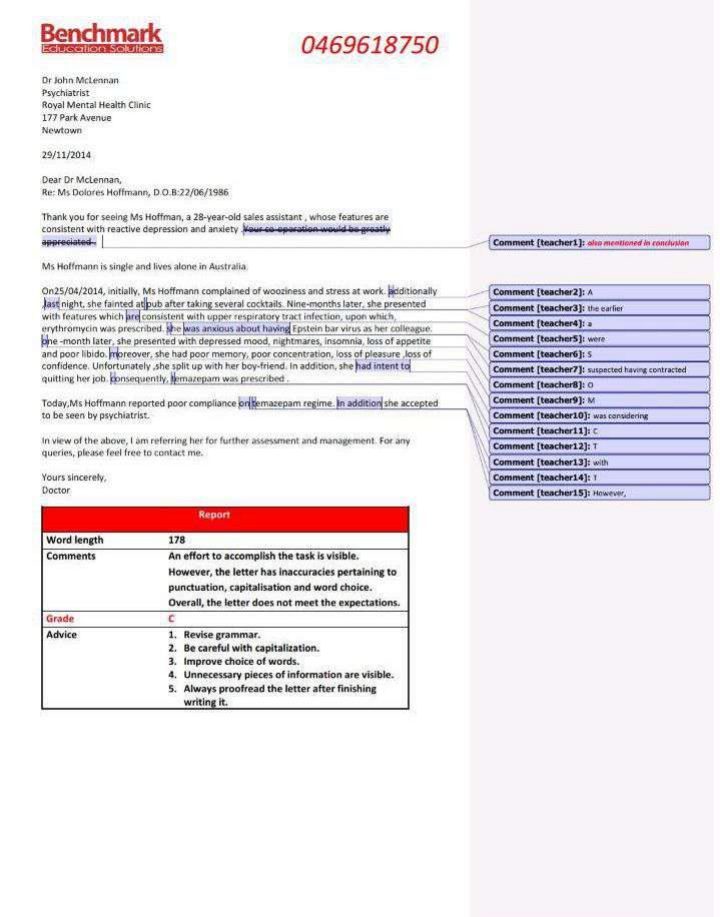
Page 27 — Re: Ms Dolores Hoffmann, D.O.B:22/06/1986
Letter (OCR)
Dr John McLennan
Psychiatrist
Royal Mental Health Clinic
177 Park Avenue
Newtown
29/11/2014
Dear Dr McLennan,
Re: Ms Dolores Hoffmann, D.O.B:22/06/1986
Thank you for seeing Ms Hoffman, a 28-year-old sales assistant, whose features are
consistent with reactive depression and anxiety Mour co
ould-bo greatly
appreciated
Ms Hoffmann is single and lives alone in Australia.
On25/04/2014, initially, Ms Hoffmann complained of wooziness and stress at work. additionally
Jast night, she fainted at pub after taking several cocktails. Nine-months later, she presented
with features which pre consistent with upper respiratory tract infection, upon which
erythromycin was prescribed, She was anxious about having Epstein bar virus as her colleague.
Comment teachers! a
one-month later, she presented with depressed mood, nightmares, insomnia, loss of appetite
and poor libido. moreover, she had poor memory, poor concentration, loss of pleasure loss of
confidence. Unfortunately, she split up with her boy-friend. In addition, she had intent to
quitting her job consequently, femazepam was prescribed.
Today, Ms Hoffmann reported poor compliance or temazepam regime. In addition she accepted
to be seen by psychiatrist.
in view of the above, I am referring her for further assessment and management. For any
queries, please feel free to contact me.
Yours sincerely,
Doctor
Assessor feedback (OCR)
Word length
178
Comments
An effort to accomplish the task is visible.
However, the letter has inaccuracies pertaining to
punctuation, capitalisation and word choice.
Overall, the letter does not meet the expectations.
Grade
Advice
- Revise grammar.
- Be careful with capitalization.
- Improve choice of words.
- Unnecessary pieces of information are visible.
- Always proofread the letter after finishing
writing it.
Margin comments
- Comment [teacher1]: also mentioned in cond
- Comment [teacher2]: A
- Comment [teacher3): the earlier
- Comment [teacherS]: were:
- Comment [teacher6]: S
- Comment [teacher7]: suspected having contracted
- Comment [teacher8]: o
- Comment [teacher9]: M
- Comment [teacher10]: was considering
- Comment [teacher11]: c
- Comment [teacher12]; T
- Comment [teacher13]: with
- Comment [teacher14]: 1
- Comment [teacher15]: However,
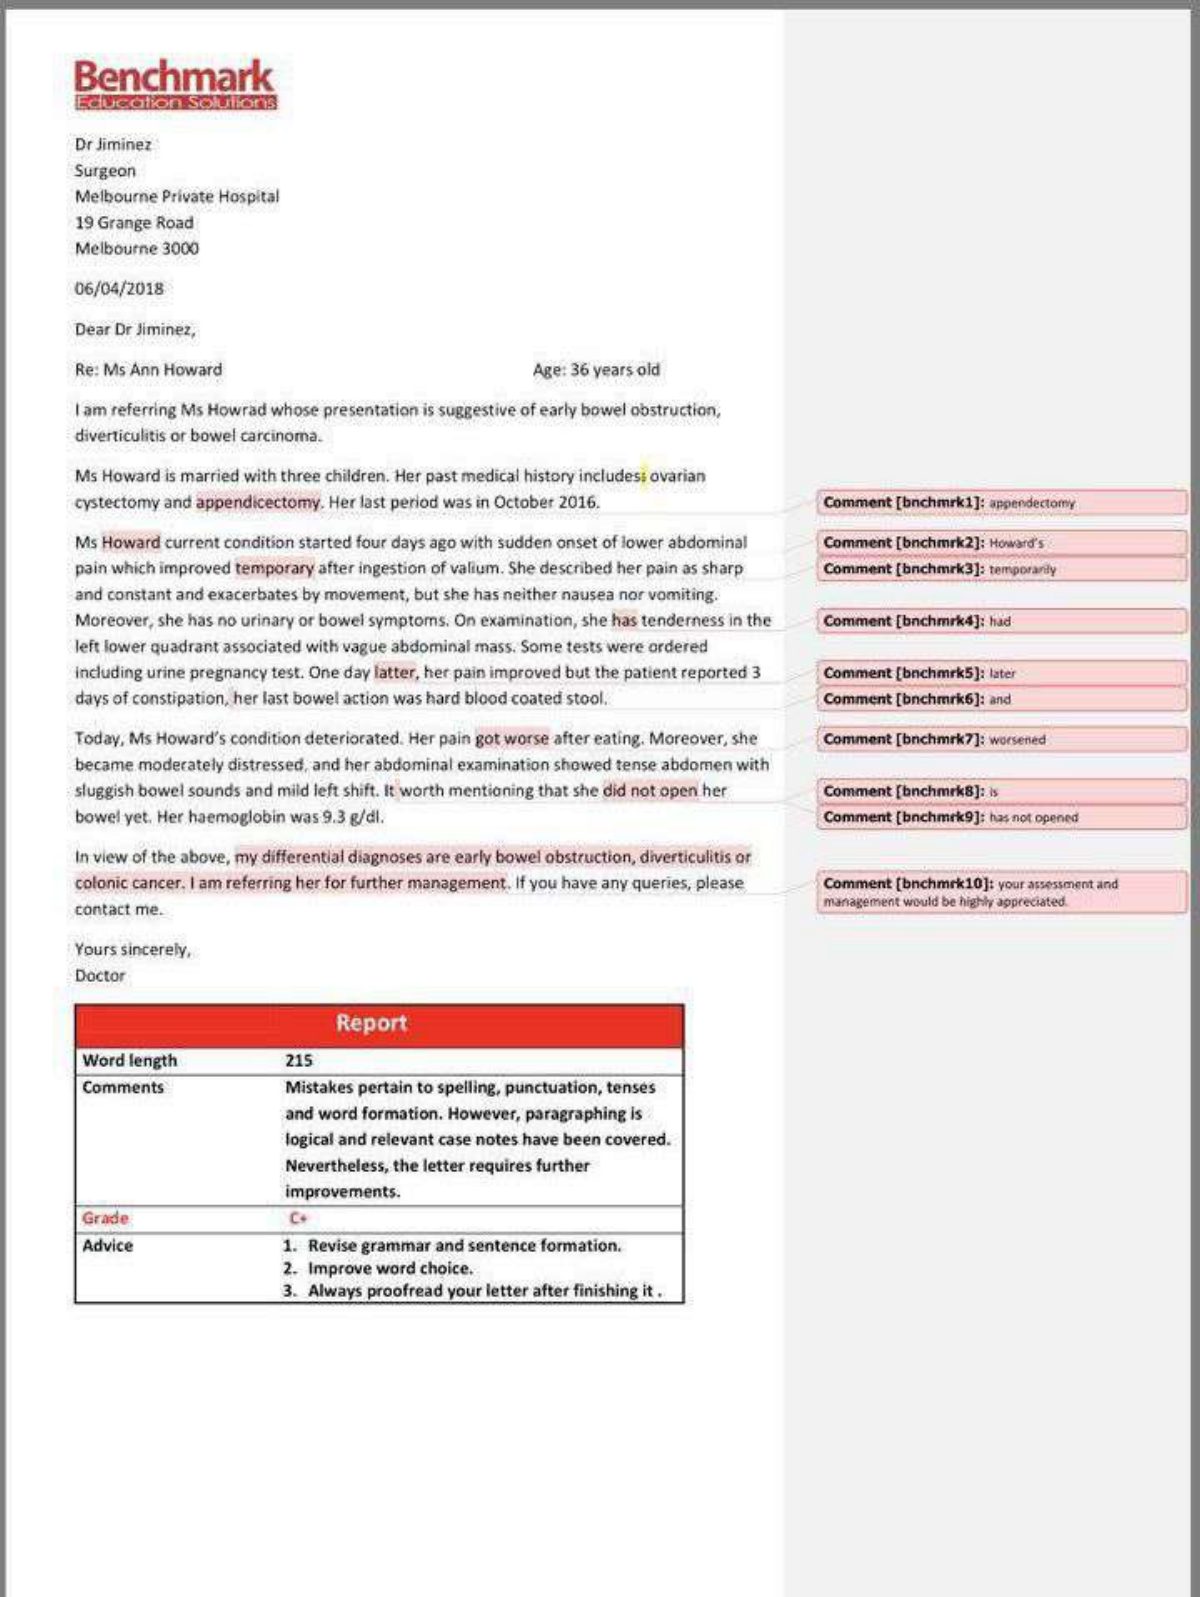
Page 28 — Re: Ms Ann Howard
Letter (OCR)
Feucation Salulion:
Dr Jiminez
Surgeon
Melbourne Private Hospital
19 Grange Road
Melbourne 3000
06/04/2018
Dear Dr Jiminez,
Re: Ms Ann Howard
Age: 36 years old
I am referring Ms Howrad whose presentation is suggestive of early bowel obstruction,
diverticulitis or bowel carcinoma.
Ms Howard is married with three children. Her past medical history includess ovarian
cystectomy and appendicectomy. Her last period was in October 2016.
Ms Howard current condition started four days ago with sudden onset of lower abdominal
pain which improved temporary after ingestion of valium. She described her pain as sharp
and constant and exacerbates by movement, but she has neither nausea nor vomiting.
Moreover, she has no urinary or bowel symptoms. On examination, she has tenderness in the
left lower quadrant associated with vague abdominal mass. Some tests were ordered
including urine pregnancy test. One day latter, her pain improved but the patient reported 3
days of constipation, her last bowel action was hard blood coated stool.
Today, Ms Howard’s condition deteriorated. Her pain got worse after eating. Moreover, she
became moderately distressed, and her abdominal examination showed tense abdomen with
sluggish bowel sounds and mild left shift. It worth mentioning that she did not open her
bowel yet. Her haemoglobin was 9.3 g/dl.
In view of the above, my differential diagnoses are early bowel obstruction, diverticulitis or
colonic cancer. I am referring her for further management. If you have any queries, please
contact me.
management would be highly appreciated
Yours sincerely,
Doctor
Assessor feedback (OCR)
Word length
215
Comments
Mistakes pertain to spelling, punctuation, tenses
and word formation. However, paragraphing is
logical and relevant case notes have been covered.
Nevertheless, the letter requires further
improvements.
Grade
C+
Advice
- Revise grammar and sentence formation.
- Improve word choice.
- Always proofread your letter after finishing it.
Margin comments
- Comment [bnchmrk1]: appendectomy
- Comment [bnchmrk2]; Howard’s
- Comment [bnchmrk3]: temporarly
- Comment [bnchmrk4]: had
- Comment [bnchmrk5]: later
- Comment [bnchmrk6]: and
- Comment [bnchmrk7]: worsened
- Comment [bnchmrk8]: is
- Comment [bnchmrk9]: has not opened
- Comment [bnchmrk10]: your assessment and
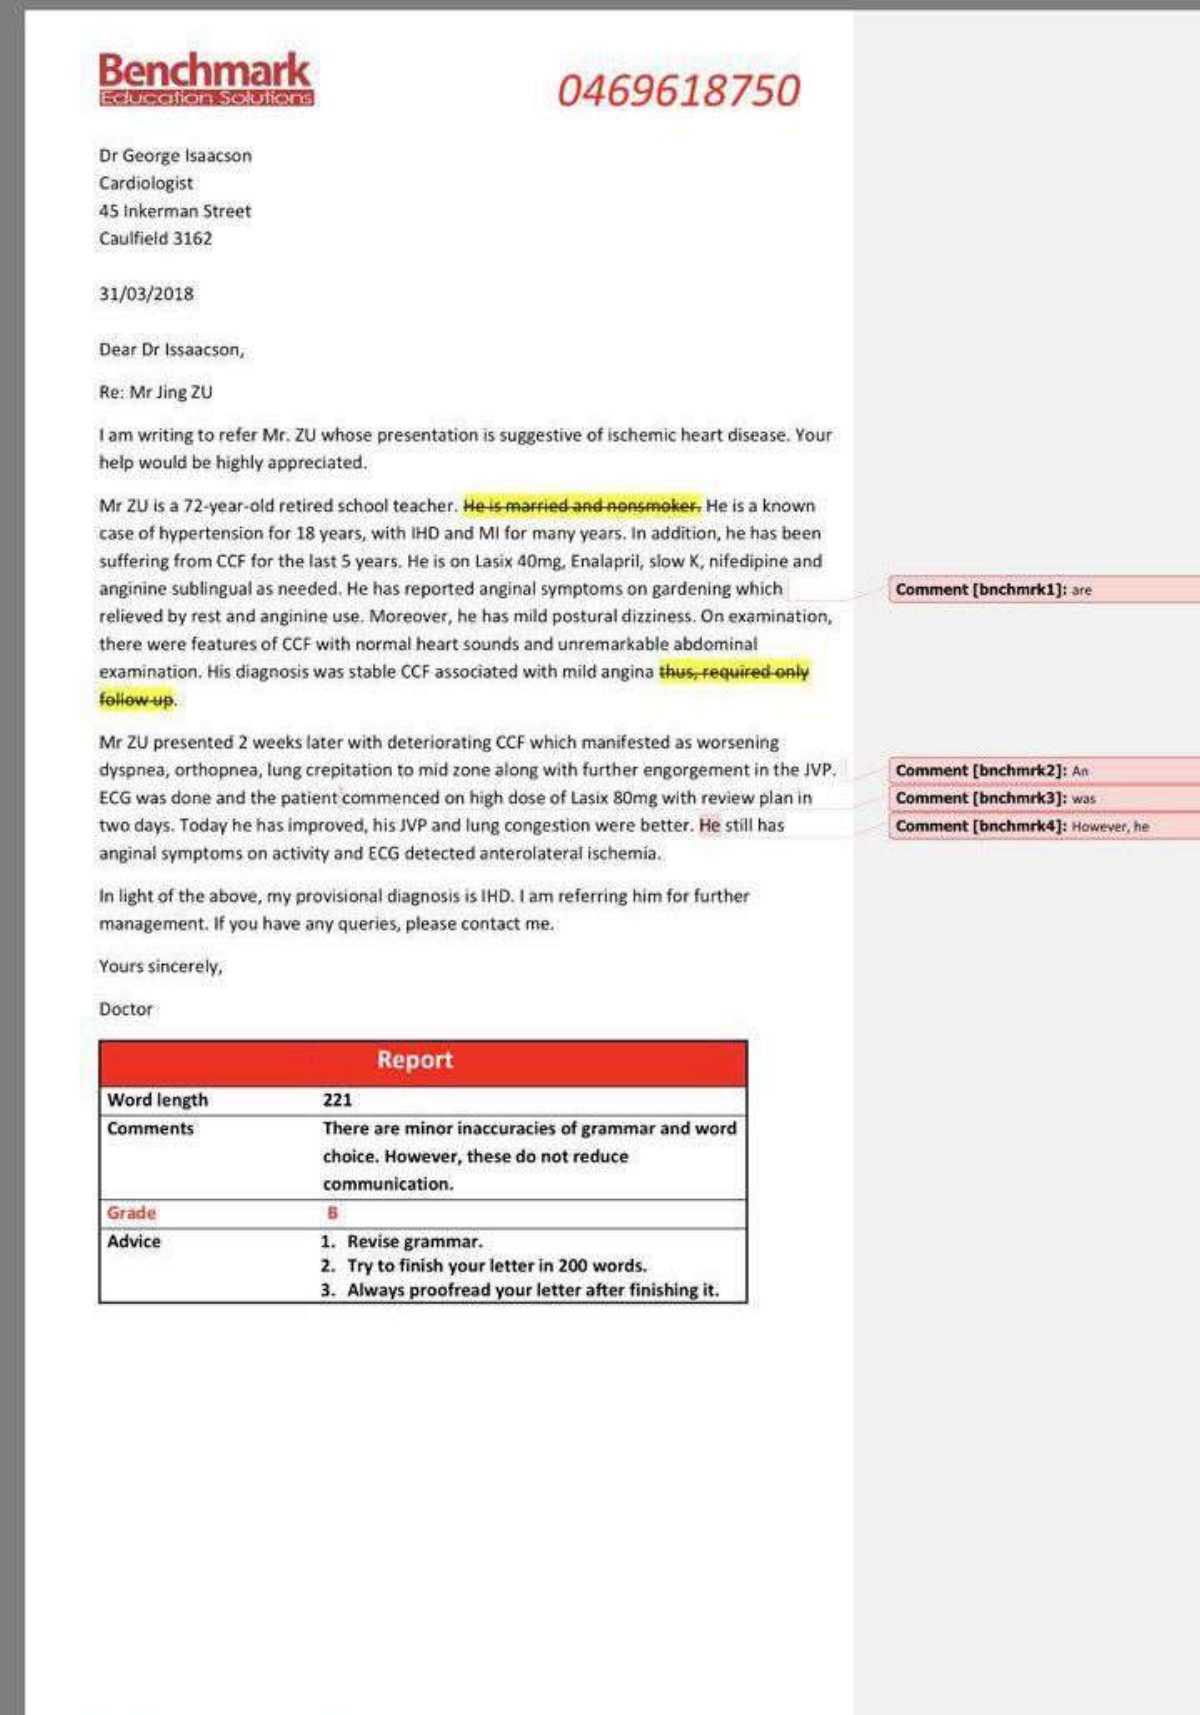
Page 29 — Re: Mr Jing ZU
Letter (OCR)
Eaucation Solutions
Dr George Isaacson
Cardiologist
45 Inkerman Street
Caulfield 3162
31/03/2018
Dear Dr Issaacson,
Re: Mr Jing ZU
I am writing to refer Mr. ZU whose presentation is suggestive of ischemic heart disease. Your
help would be highly appreciated.
Mr ZU is a 72-year-old retired school teacher. He is married and nonsmoker. He is a known
case of hypertension for 18 years, with IHD and MI for many years. In addition, he has been
suffering from CCF for the last 5 years. He is on Lasix 40mg, Enalapril, slow K, nifedipine and
anginine sublingual as needed. He has reported anginal symptoms on gardening which
relieved by rest and anginine use. Moreover, he has mild postural dizziness. On examination,
there were features of CCF with normal heart sounds and unremarkable abdominal
examination. His diagnosis was stable CCF associated with mild angina thus, required only
foliow up.
Mr ZU presented 2 weeks later with deteriorating CCF which manifested as worsening
dyspnea, orthopnea, lung crepitation to mid zone along with further engorgement in the JVP.
ECG was done and the patient commenced on high dose of Lasix 80mg with review plan in
two days. Today he has improved, his JVP and lung congestion were better. He still has
anginal symptoms on activity and ECG detected anterolateral ischemia.
In light of the above, my provisional diagnosis is IHD. I am referring him for further
management. If you have any queries, please contact me.
Yours sincerely,
Doctor
Assessor feedback (OCR)
Word length
221
Comments
There are minor inaccuracies of grammar and word
choice. However, these do not reduce
communication.
Grade
Advice
- Revise grammar.
- Try to finish your letter in 200 words.
- Always proofread your letter after finishing it.
Margin comments
- Comment [bnchmrk1]: are
- Comment [bnchmrk2]: An
- Comment [bnchmrk3]: was
- Comment [bnchmrk4]: However, he
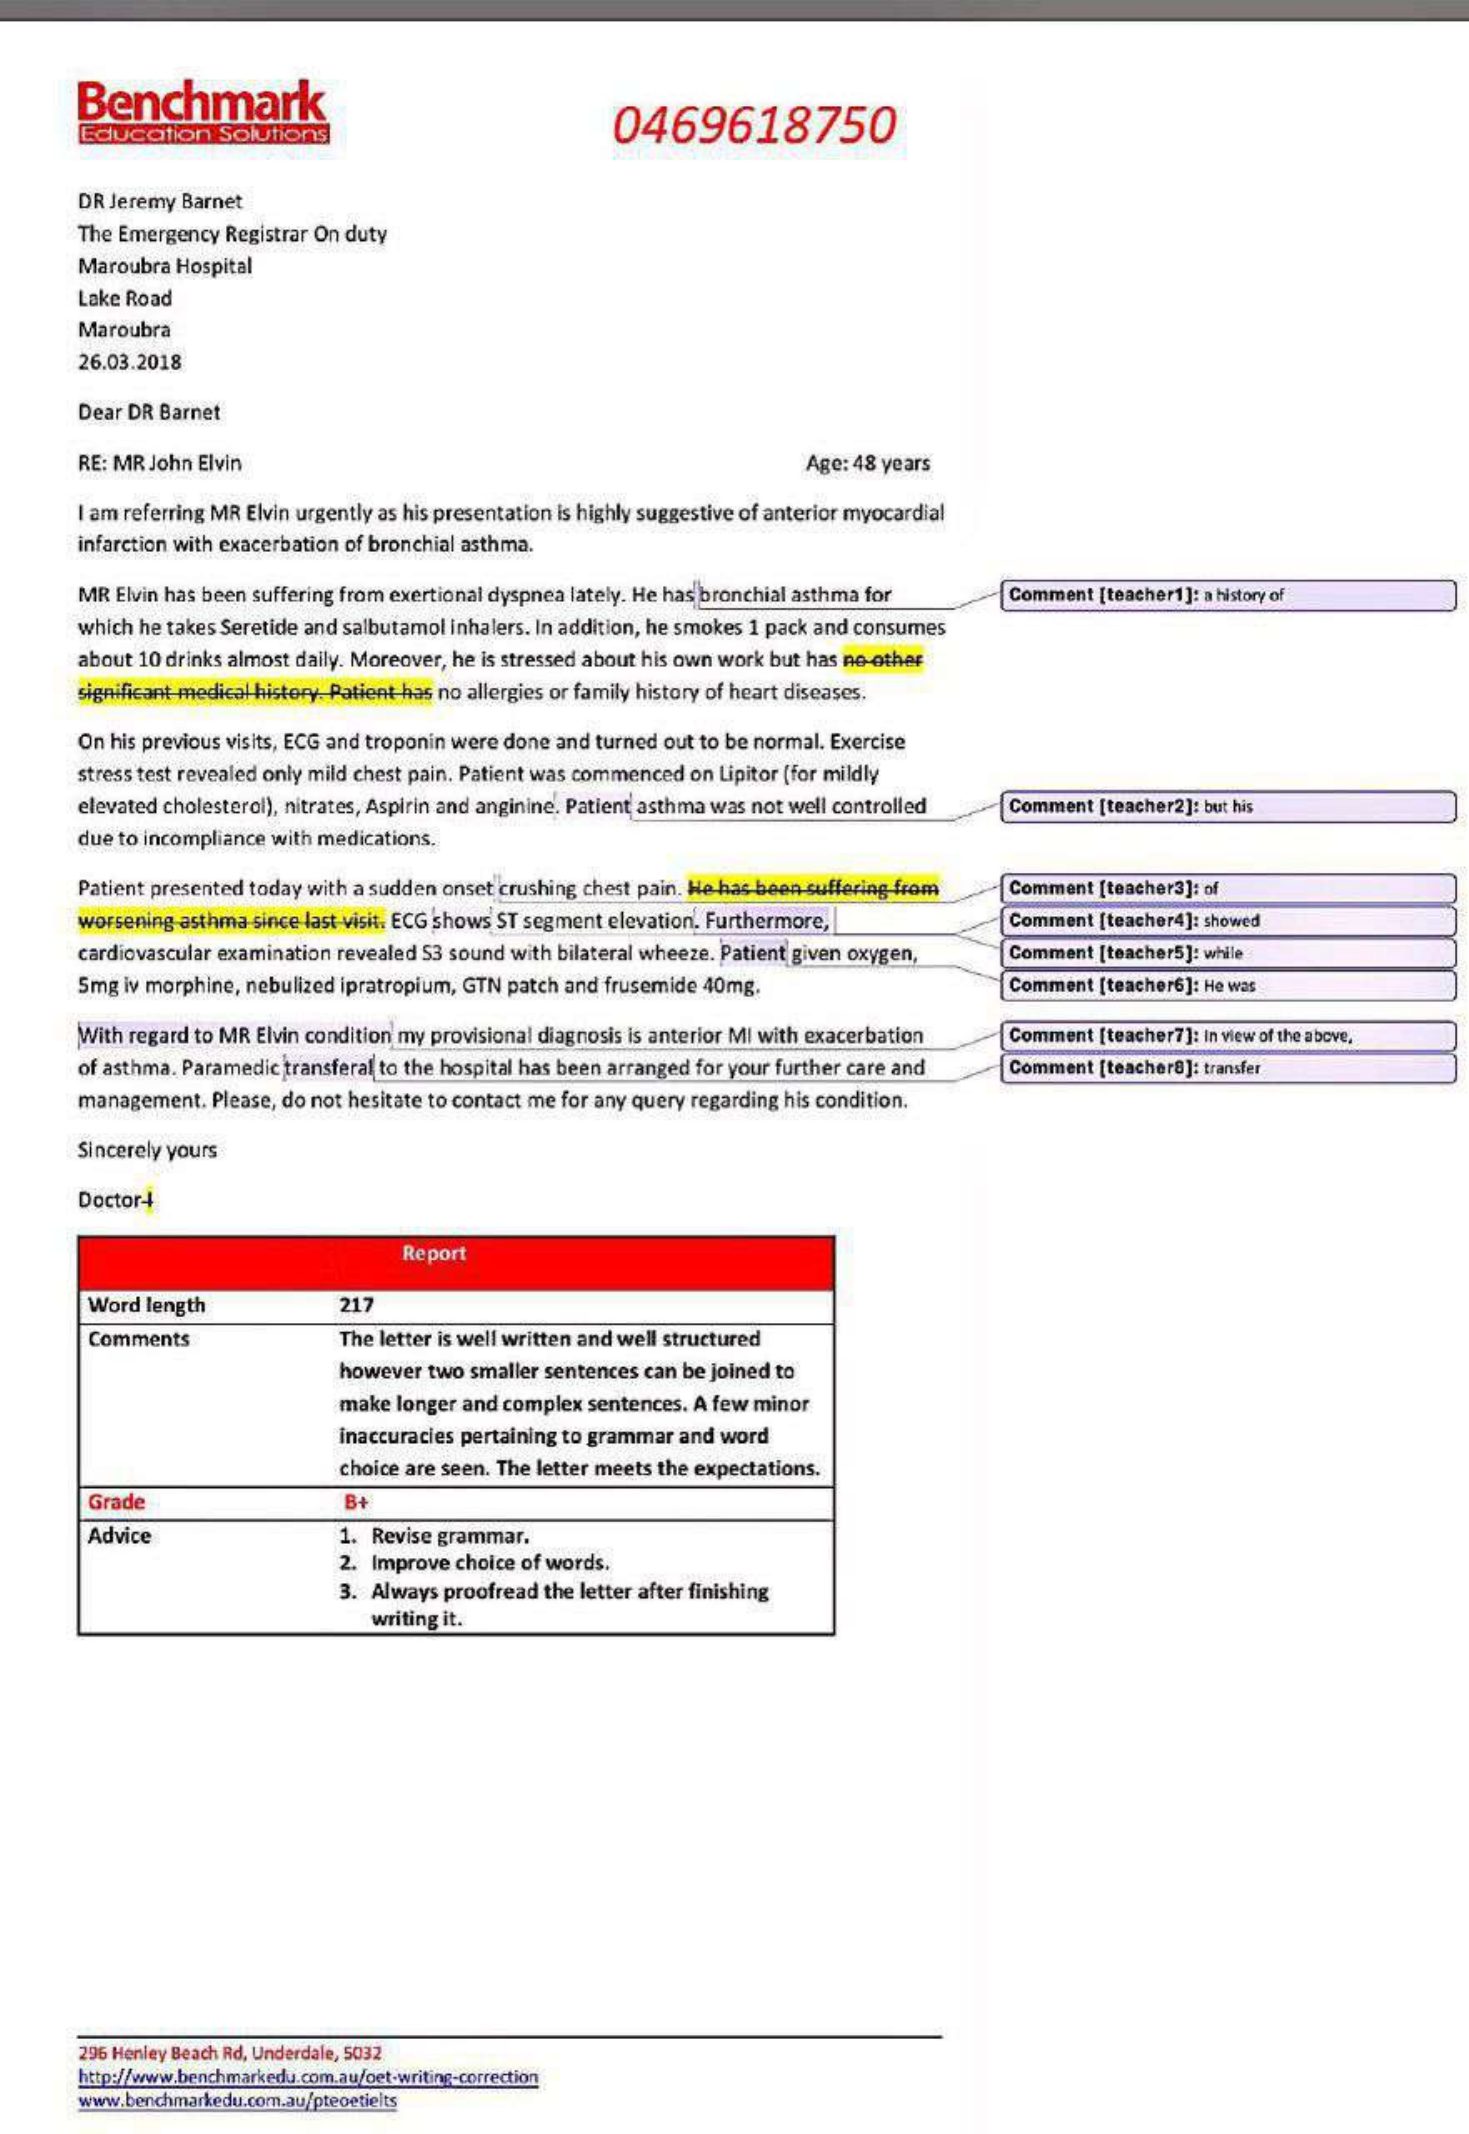
Page 30 — RE: MR John Elvin
Letter (OCR)
DR Jeremy Barnet
The Emergency Registrar On duty
Maroubra Hospital
Lake Road
Maroubra
26.03.2018
Dear DR Barnet
RE: MR John Elvin
Age: 48 years
I am referring MR Elvin urgently as his presentation is highly suggestive of anterior myocardial
infarction with exacerbation of bronchial asthma.
MR Elvin has been suffering from exertional dyspnea lately. He has bronchial asthma for
which he takes Seretide and salbutamol inhalers. In addition, he smokes 1 pack and consumes
about 10 drinks almost daily. Moreover, he is stressed about his own work but has ne-other
significant medical histery. Patient has no allergies or family history of heart diseases.
On his previous visits, ECG and troponin were done and turned out to be normal. Exercise
stress test revealed only mild chest pain. Patient was commenced on Lipitor (for mildly
elevated cholesterol), nitrates, Aspirin and anginine. Patient asthma was not well controlled
due to incompliance with medications.
Patient presented today with a sudden onset crushing chest pain. We has been suffering from
worsening asthma since last visit. ECG shows ST segment elevation. Furthermore,
cardiovascular examination revealed 53 sound with bilateral wheeze. Patient given oxygen,
Smg iv morphine, nebulized ipratropium, GTN patch and frusemide 40mg.
With regard to MR Elvin condition my provisional diagnosis is anterior MI with exacerbation
of asthma. Paramedic transferal to the hospital has been arranged for your further care and
management. Please, do not hesitate to contact me for any query regarding his condition.
Sincerely yours
Doctor+
Assessor feedback (OCR)
Word length
217
Comments
The letter is well written and well structured
however two smaller sentences can be joined to
make longer and complex sentences. A few minor
inaccuracies pertaining to grammar and word
choice are seen. The letter meets the expectations.
Grade
B+
Advice
- Revise grammar.
- Improve choice of words.
- Always proofread the letter after finishing
writing it.
www:.benchmarkedu.com.au/pteoetieits
Margin comments
- Comment [teacher1]: a history of
- Comment [teacher2]: but his
- Comment [teacher3]: of
- Comment [teacher4]: showed
- Comment [teacher5]: while
- Comment [teacher6]: He was
- Comment [teacher7]: In view of the above,
- Comment [teacher8]: transfer
Page 31 — Re: Joshua Vance D.O.B: 17/11/2013
Letter
Admitting Officer
Emergency Department
Children’s Hospital
Newtown
18/01/2014
Dear Sir/Madam,
Re: Joshua Vance D.O.B: 17/11/2013
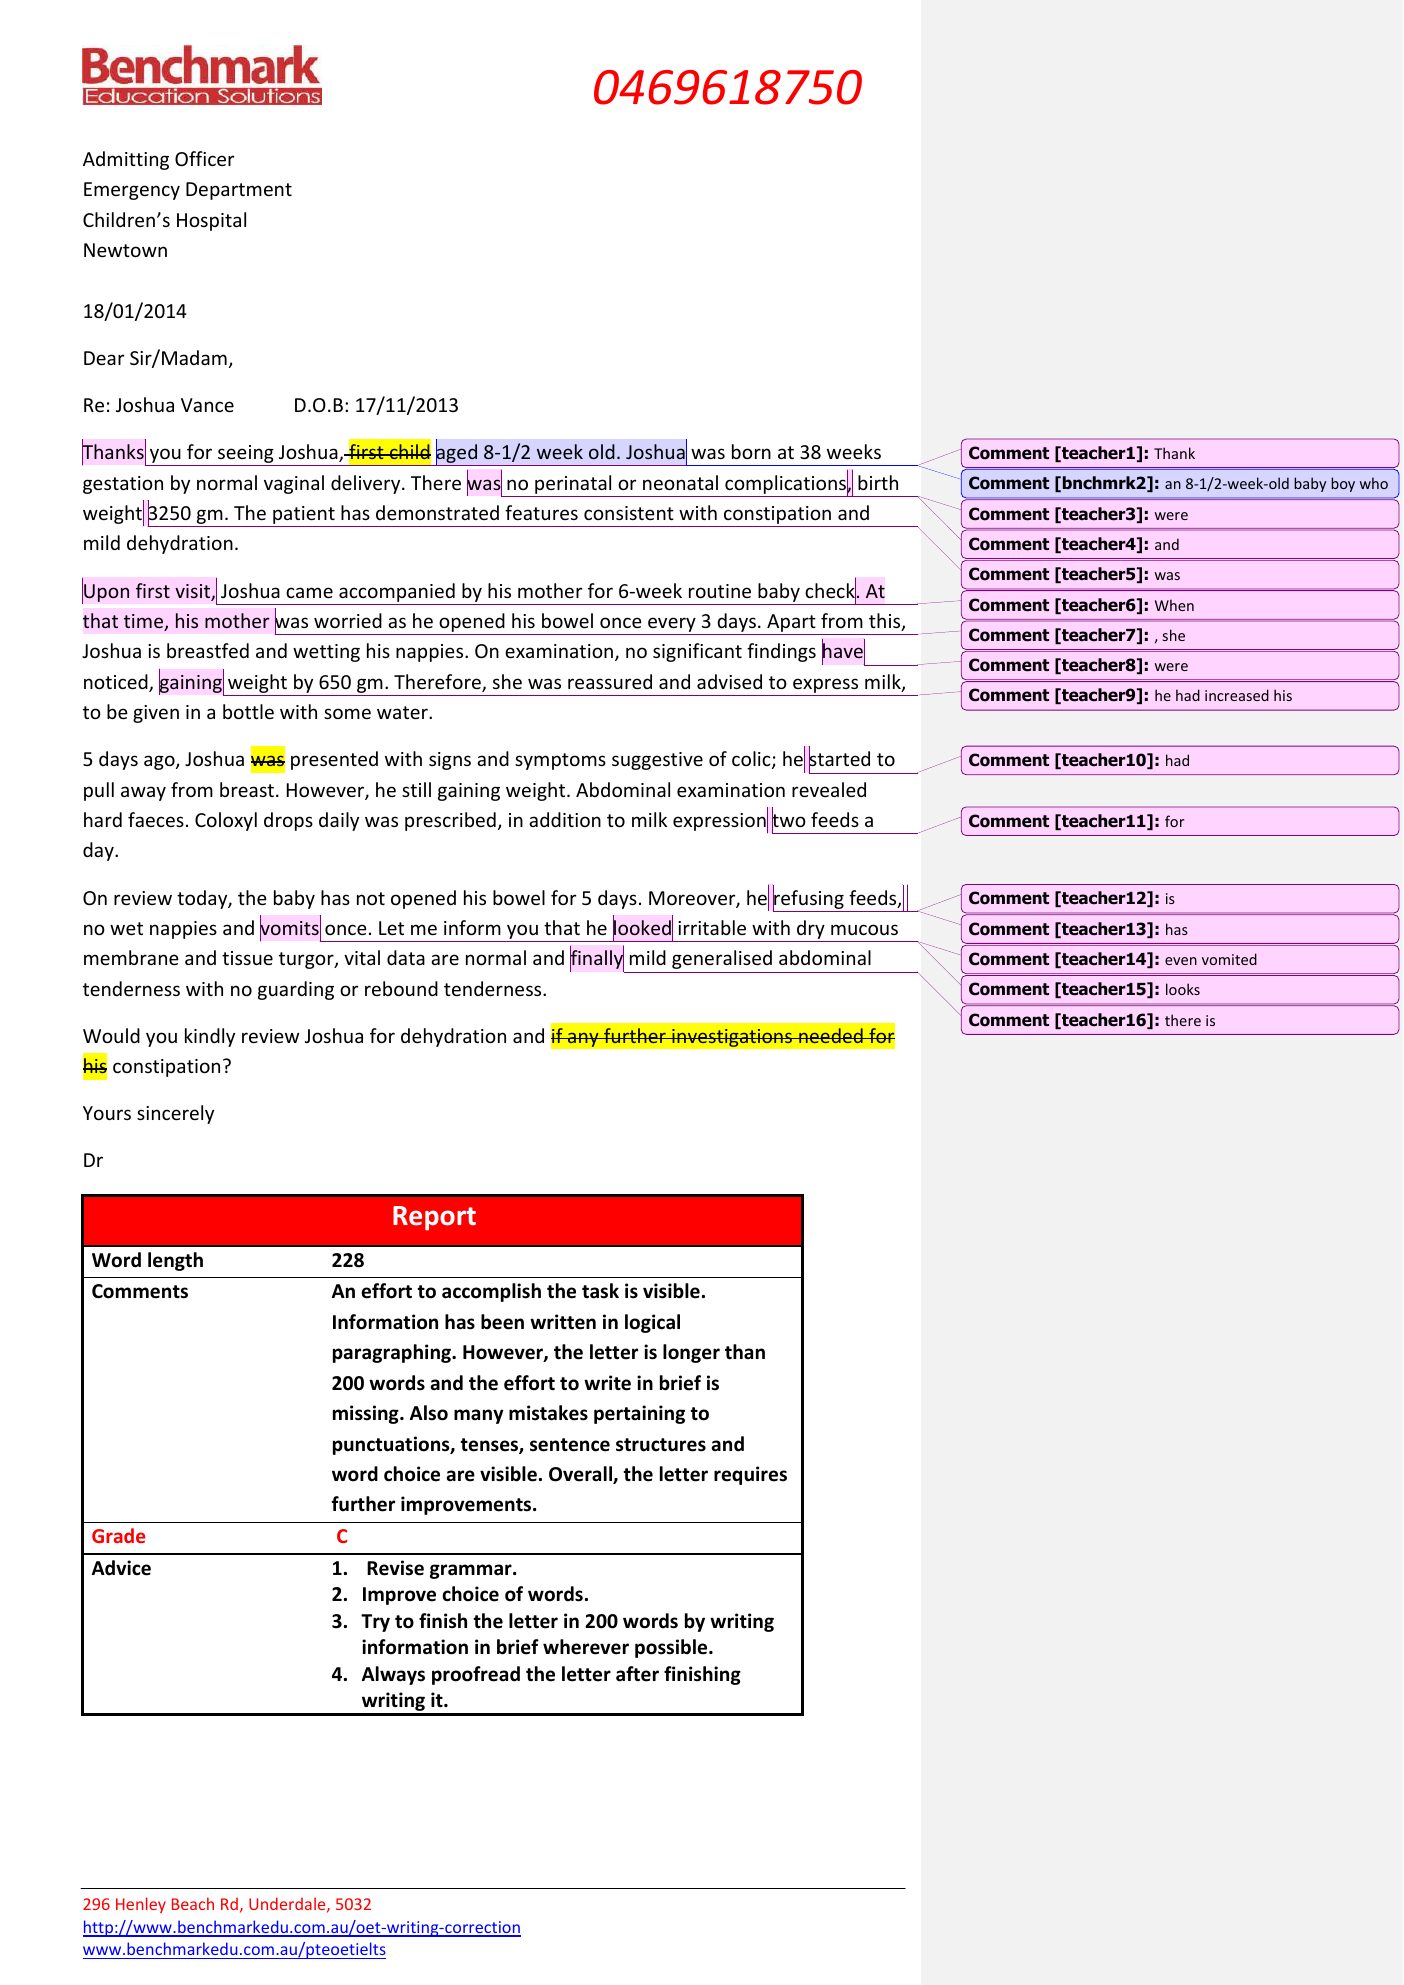
Thanks you for seeing Joshua, first child aged 8-1/2 week old. Joshua was born at 38 weeks
gestation by normal vaginal delivery. There was no perinatal or neonatal complications, birth
weight 3250 gm. The patient has demonstrated features consistent with constipation and
mild dehydration.
Upon first visit, Joshua came accompanied by his mother for 6-week routine baby check. At
that time, his mother was worried as he opened his bowel once every 3 days. Apart from this,
Joshua is breastfed and wetting his nappies. On examination, no significant findings have
noticed, gaining weight by 650 gm. Therefore, she was reassured and advised to express milk,
to be given in a bottle with some water.
5 days ago, Joshua was presented with signs and symptoms suggestive of colic; he started to
pull away from breast. However, he still gaining weight. Abdominal examination revealed
hard faeces. Coloxyl drops daily was prescribed, in addition to milk expression two feeds a
day.
On review today, the baby has not opened his bowel for 5 days. Moreover, he refusing feeds,
no wet nappies and vomits once. Let me inform you that he looked irritable with dry mucous
membrane and tissue turgor, vital data are normal and finally mild generalised abdominal
tenderness with no guarding or rebound tenderness.
Would you kindly review Joshua for dehydration and if any further investigations needed for
his constipation?
Yours sincerely
Dr
Assessor feedback
Word length 228
Comments An effort to accomplish the task is visible.
Information has been written in logical
paragraphing. However, the letter is longer than
200 words and the effort to write in brief is
missing. Also many mistakes pertaining to
punctuations, tenses, sentence structures and
word choice are visible. Overall, the letter requires
further improvements.
Grade C
Advice 1. Revise grammar.
2. Improve choice of words.
3. Try to finish the letter in 200 words by writing
information in brief wherever possible.
4. Always proofread the letter after finishing
writing it.
Margin comments
- Comment [teacher1]: Thank
- Comment [bnchmrk2]: an 8-1/2-week-old baby boy who
- Comment [teacher3]: were
- Comment [teacher4]: and
- Comment [teacher5]: was
- Comment [teacher6]: When
- Comment [teacher7]: , she
- Comment [teacher8]: were
- Comment [teacher9]: he had increased his
- Comment [teacher10]: had
- Comment [teacher11]: for
- Comment [teacher12]: is
- Comment [teacher13]: has
- Comment [teacher14]: even vomited
- Comment [teacher15]: looks
- Comment [teacher16]: there is
Page 32 — Re: Mr. Brett Collister, D.O.B.: 20/11/1970
Letter
Dr Granthy Cross
Consultant Endocrinologist
City Hospital
Suite 32
55 Main Road
Newtown
24/01/2015
Dear Dr Cross,
Re: Mr. Brett Collister, D.O.B.: 20/11/1970
Thank you for seeing Mr. Collister who has features consistent with type 2 DM.
Mr. Collister is married and working as a foreman. His hobbies do not include any regular exercises.
Regarding the patient’s past history; he was suffering from repeated infections, pain and sore throat, therefore
analgesics and antibiotics were prescribed. The patient had been referred to the physio twice last year. Firstly,
he complained of sore L shoulder due to playing darts on which he received treatment. Secondly, he presented
with sore R knee and there was query osteoarthritis. The patient’s BMI was 30, accordingly he was advised to
practice more sports and to reduce weight.
3 months later, Mr. Collister developed sore eye, tiredness, dizziness and may be orthostatic hypotension. He
was still overweight with 29.7 BMI, unfit and he did not follow the previous recommendations. Laboratory
investigations were requested including cholesterol and blood sugars.
On today review, the patient is in the same condition, however there is mild improvement in his BMI (28.4).
The laboratory results have revealed high random glucose, high fasting glucose, increased HDL/LDL and 8.4%
HgA1C.
I would very much appreciate your further assessment and management regarding this patient.
Yours sincerely,
Doctor
Assessor feedback
Word length 196
Comments An effort to accomplish the task is visible. Flow of
information in logical. However, mistakes
pertaining to word choice, word order, articles and
prepositions is visible. Sentence formation and
paraphrasing of case notes could be better.
Overall, the letter requires further improvements.
Grade C+
Advice 1. Improve sentence structures and revise
grammar.
2. Learn more vocabulary and word choice.
3. It is better to give dates than writing firstly,
secondly etc.
4. Always proofread your letter after finishing it.
Margin comments
- Comment [bnchmrk1]: ,
- Comment [bnchmrk2]: left
- Comment [bnchmrk3]: His recent medical history includes an episode of tonsillitis and sore left shoulder which were cured successfully .
- Comment [bnchmrk4]: Upon his visit on 26/10/2014,
- Comment [bnchmrk5]: right
- Comment [bnchmrk6]: with intermittent pain
- Comment [bnchmrk7]: of
- Comment [bnchmrk8]: ibuprofen for pain
- Comment [bnchmrk9]: On his subsequent visit
- Comment [bnchmrk10]: a
- Comment [bnchmrk11]: and complained of
- Comment [bnchmrk12]: possible
- Comment [bnchmrk13]: review today
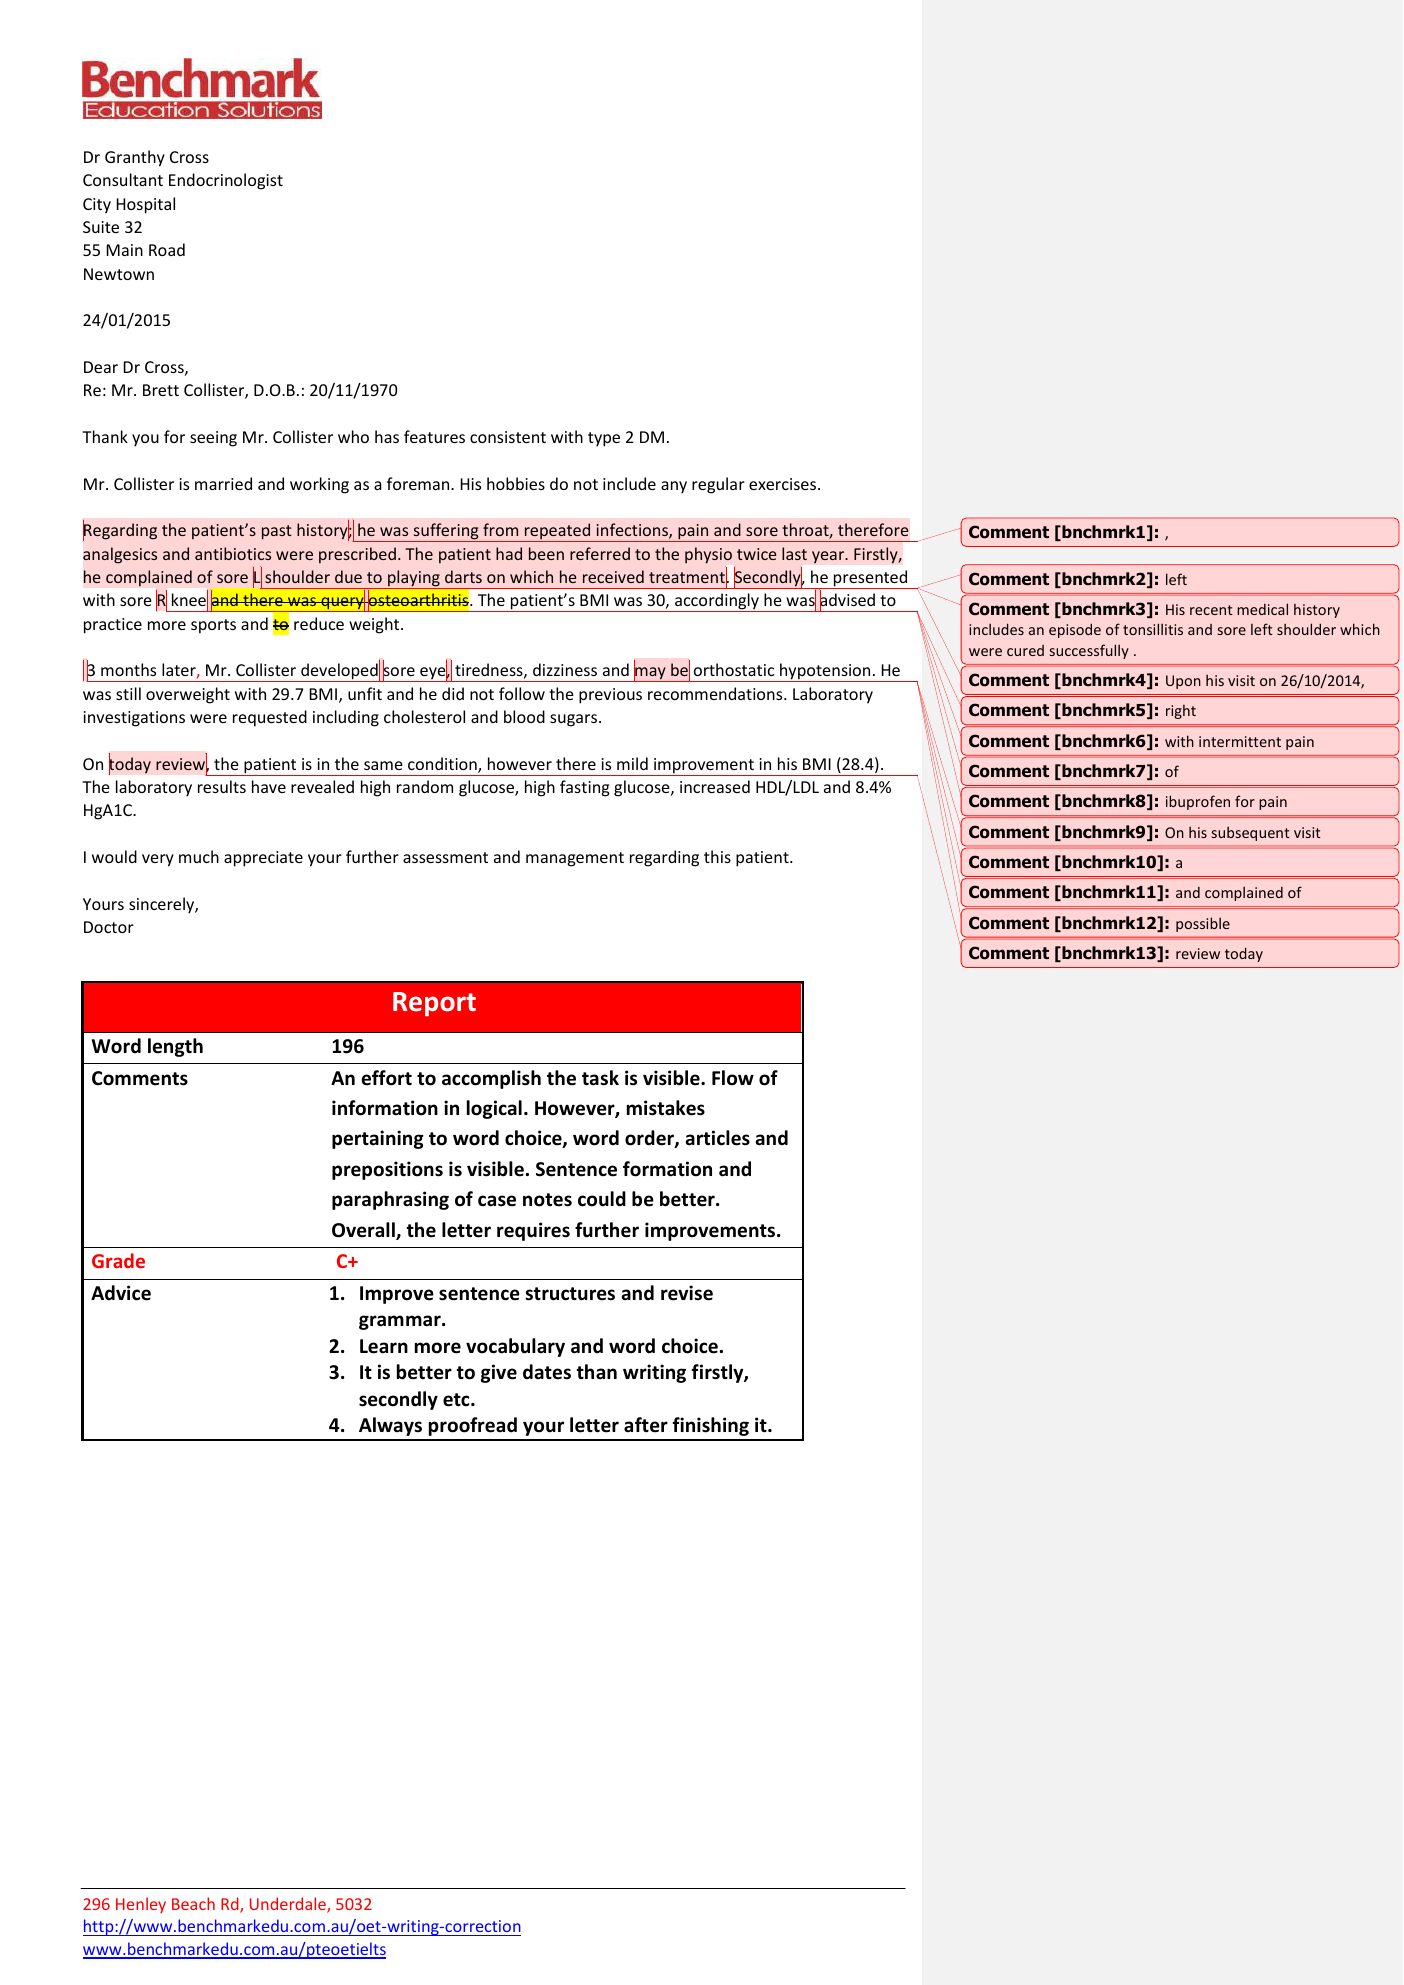
Page 33 — Re: Mrs. Priya Sharma, D.O.B.: 08/05/1954
Letter
Dr Lisa Smith
Endocrinologist
City Hospital
Newtown
10/02/2014
Dear Dr Smith,
Re: Mrs. Priya Sharma, D.O.B.: 08/05/1954
Thank you for seeing Mrs. Sharma who is 60 years old and married 40 years ago. She has
features consistent with uncontrolled level of blood sugar.
Regarding the patient’s family history; many family members suffer from NIDDM. Mrs.
Sharma has been diagnosed with NIDDM since 1994. Furthermore, she is known allergic to
penicillin. She is on metformin 500mg 2 nocte and glipizide 5mg 2 mane.
Mrs. Sharma visited me on 29/12/2013 complaining of uncontrolled blood sugar level, which
was ranging between 6-18. However her examination was normal, blood pressure was found
to be high. Therefore, I prescribed candesartan tab 4mg 1 mane to her. FBE, U&Es, creatinine,
LFTs, full lipid profile and HBA1C were requested. The patient would be reviewed within 2
weeks.
Two weeks later, I discussed the pathology report with the patient which revealed GFR >
60ml/min, HBA1C 10% and high lipid profile. Accordingly, metformin had changed to 1 b.d.,
while glipizide to be continued as before. Atrovastatin 20mg 1 mane was added as new drug.
After regular follow up and investigations, however there was improvement in her pathology
report, her fasting sugar is still high around 16+.
I would very much appreciate your further management regarding this patient.
Yours sincerely
Doctor
Assessor feedback
Word length 201
Comments There are a few inaccuracies of grammar and word
choice. Nevertheless, the letter meets the
expectations.
Grade B
Advice 1. Revise grammar.
2. Improve choice of words.
3. Always proofread the letter after finishing
writing it.
Margin comments
- Comment [teacher1]: repetitive/not required in the introduction
- Comment [teacher2]: was
- Comment [teacher3]: in
- Comment [teacher4]: Though
- Comment [teacher5]: was to
- Comment [teacher6]: was
- Comment [teacher7]: was
- Comment [teacher8]: however, 296 Henley Beach Rd, Underdale, 5032 http://www.benchmarkedu.com.au/oet-writing-correction www.benchmarkedu.com.au/pteoetielts
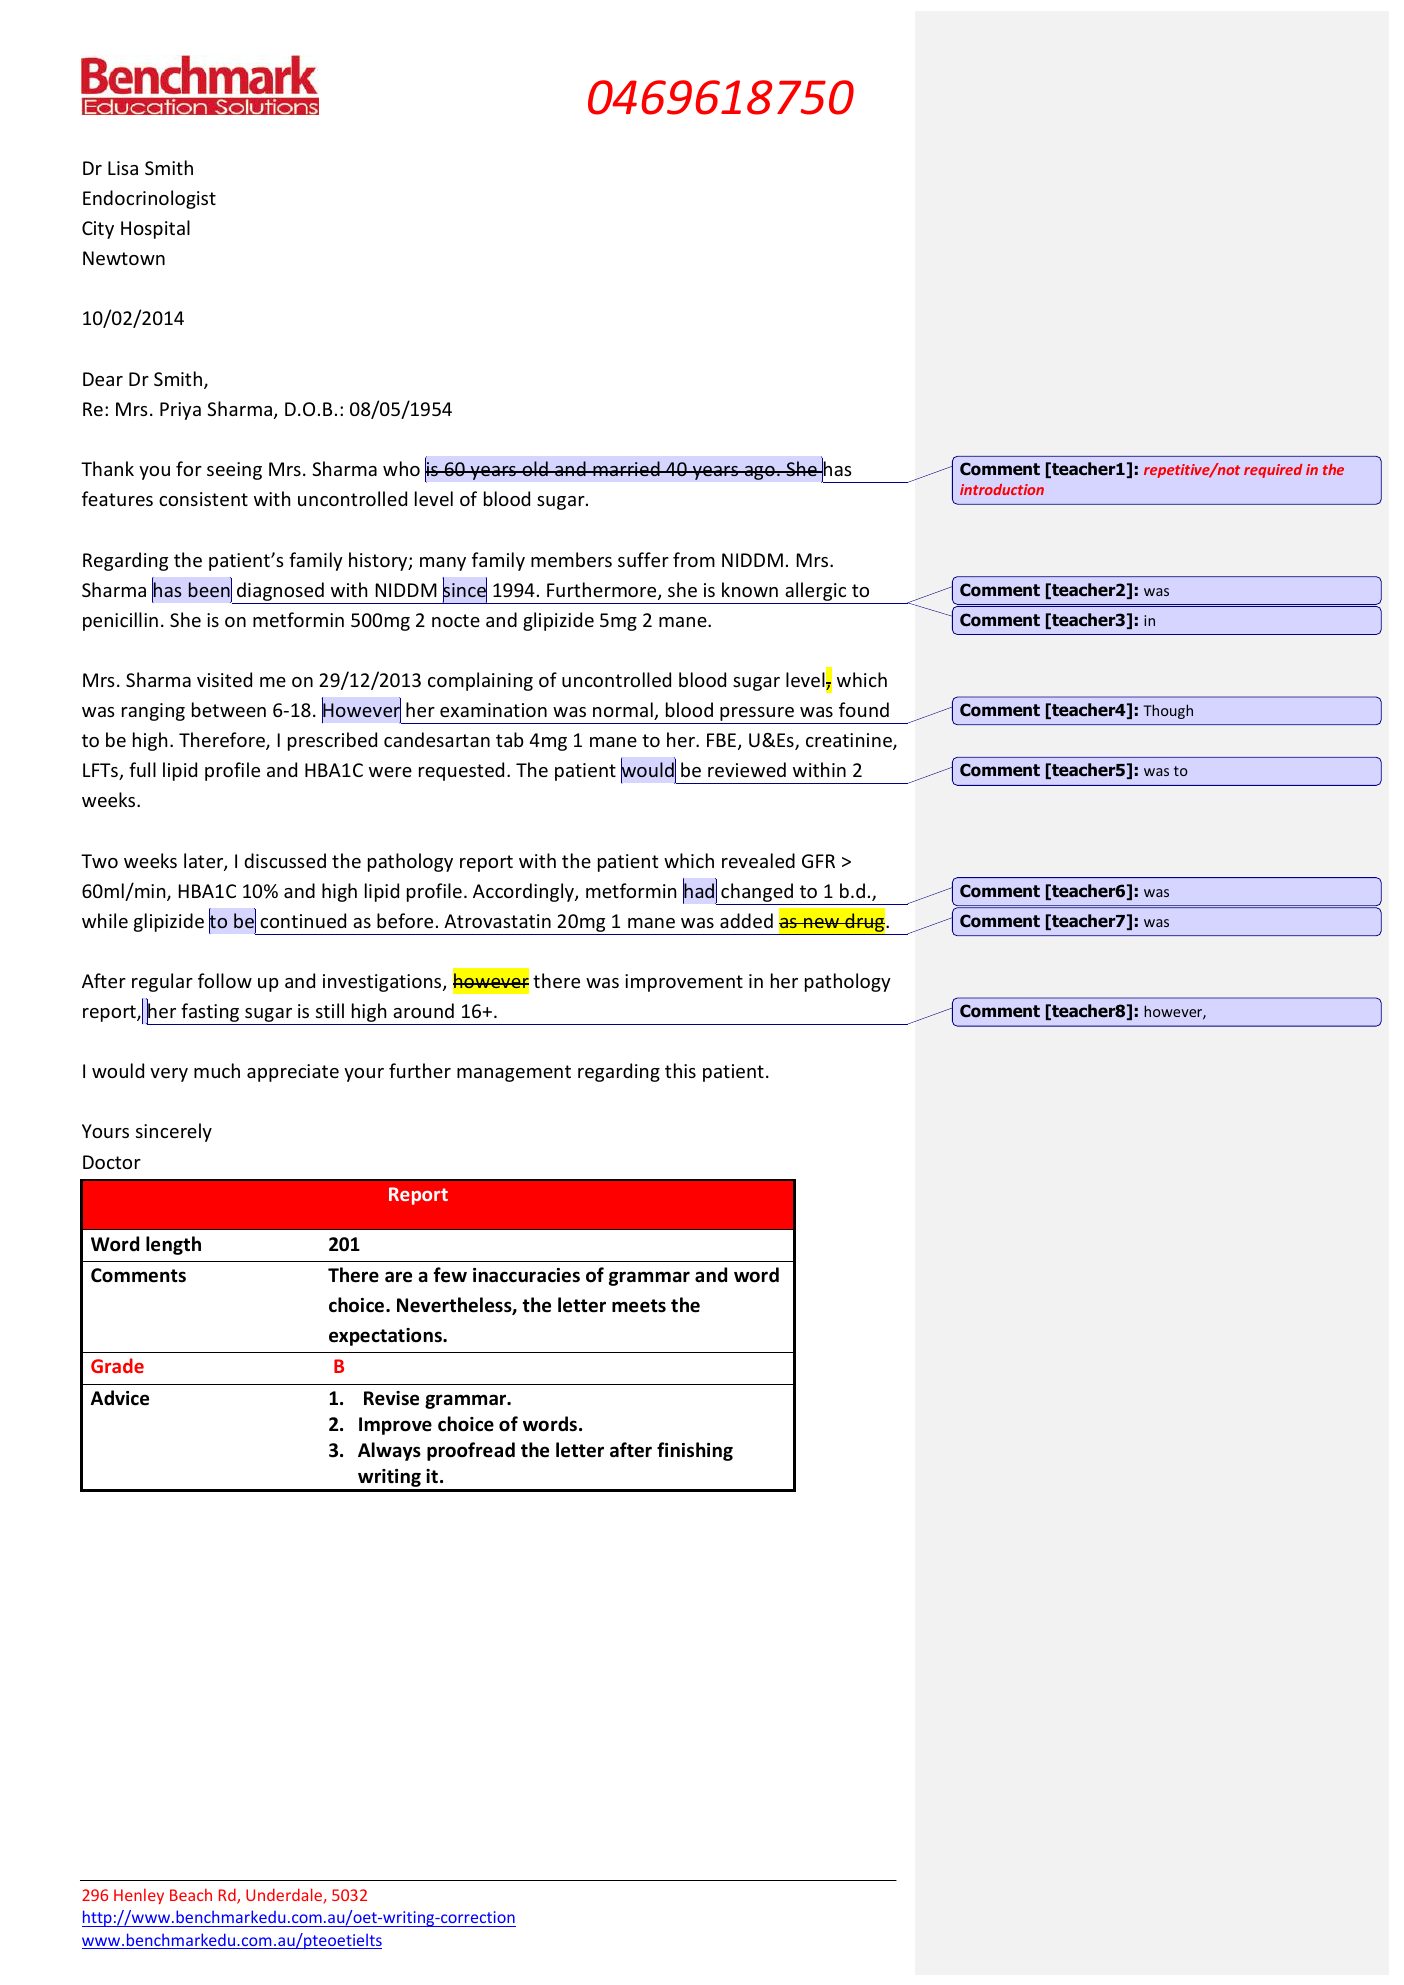
Page 34
Case notes / writing task (OCR)
Patient:
DOB:
Mrs Priya Sharma
Residence:
71 Seaside Street, Newtown
08.05.53 (Age 60)
Family History:
Social Background: Maried 40 years - 3 adult children, 5 grandchildren (overseas). Retired (clerical worker).
Many relatives with type 2 diabetes (NIDDM)
Nil else significant
Medical History:
1994 - NIDDM
Nil significant, no operations
Allergic to penicillin
Menopause 12 yrs
Never smoked, nil alcohol
No formal exercise
Current Drugs:
Metformin 500mg 2 nocte
No other prescribed, OTC, or recreational
Glipizide 5mg 2 mane
29/12/13
Discussion:
Concerned that her glucose levels are not well enough controlled - checks levels often
(worried?)
Recent blood sugar levels (BSL) 6-18
Attends health centre - feels not taking her concerns seriously
Last eye check October 2012 - OK
Checks BP at home
Wt steady, BMI 24
Bowels normal, micturition normal
App good, good diet
O/E:
Full physical exam: NAD
BP 155/100
No peripheral neuropathy; pelvic exam not performed
Medication added: candesartan (Atacand) tab 4mg 1 mane
Pathology requested: FBE, U&Es, creatinine, LFTs, full lipid profile, HbA1c
Review 2 weeks
05/01/14
Pathology report received:
FBE, U&Es, creatinine, LFTe in normal range
GFR > 80ml/min
HbA1c 10% (very poor control)
Lipida: Chol 6.2 (high), Trig 2.4. LDLC 3.7
12/01/14
Changee in medication recommended
Review of pathology resulte with Pt
Metformin regime changed from 2 nocte to 1 b.d.
Je 5mg 2 mane
tatin (Lipitor) 20mg 1 mane added
30/01/14
Home BP in range
Sugara improved
Pathology requested: fasting lipide, full profile
06/02/14
Pathology report received: Chol 3.2, Trig 1.7, LDLC 1.1
10/02/14
Fasting sugar usually in 16+ (high) range
Pathology report reviewed with Mre Shama
Heter to specialist at Diabetes Unit for further management of augar level:
Other blood sugars 7-8
Writing Task:
Using the information in the case notes, write a letter of referral to Dr Smith, an endocrinologiat at City
Endocrinologist, City Hospital, Newtown.
Hospital, for further management of Mra Sharma’s sugar levela. Addrece the letter to Dr Lisa Smith,
In your anawer:
• Expand the relevant notes into complete sentences
• Use letter format
Do not use note form
The body of the letter should be approximately 180-200 words.

Page 35 — Re: Ms Tracy Bowen, DOB: 22/07/1988
Letter
28/03/2014
Dr Susan Clayton
Endocrinologist
Women’s Health Centre
11-13 Bell Street
Newtown
Dear Dr Clayton,
Re: Ms Tracy Bowen, DOB: 22/07/1988
Thank you for seeing Ms Bowen, who is presenting with symptoms suggestive of PCOS. Your
further management is highly recommended.
Ms Bowen is a 30-year-old women, who has an abnormal menarche . It was irregular,
infrequent and associated with dysmenorrheal. She uses OCP for this disturbed menstruation
along with inhaler for asthma.
On 21/09/2015, Ms Bowen presented with severe facial, shoulder, neck and back acne. Her
acnes were infected, inflamed and filled with pus, more over multiple scars were noted at
their sites. Therefore, topical and systemic tetracycline were started. A review on 24/11/2014
was done which revealed no improvement of her condition. Therefore, I referred her to a
dermatologist for further management.
On today’s visit, Ms Bowen discontinue her OCP as she got married. Her examination
revealed high BMI and hair sutism. Her investigation were abnormal. LH, GTT and free
androgen index were high. Her Vit D and FSH were on lower side, more over her prolactin
level were very high. The patient was depressed and asked for endocrinologist opinion.
In view of the above, I suspect she has polycystic ovaries. A report of her pelvic U/S was
attached along. I would appreciate if you could offer your expert opinion and management of
her condition.
Please contact me for any questions.
Yours sincerely,
Doctor
Assessor feedback
Word length 206
Comments Mistakes pertain to spelling, word choice,
punctuation and sentence formation. However,
relevant case notes have been covered in a logical
order. Overall, the letter meets the expectations.
Grade B
Advice 1. Revise grammar and sentence formation.
2. Improve word choice.
3. Always proofread your letter after finishing it.
Margin comments
- Comment [bnchmrk1]: polycystic ovary syndrome
- Comment [bnchmrk2]: woman
- Comment [bnchmrk3]: as her intermenstrual interval stayed up to 90 days
- Comment [bnchmrk4]: acne was
- Comment [bnchmrk5]: . Moreover,
- Comment [bnchmrk6]: in
- Comment [bnchmrk7]: discontinued
- Comment [bnchmrk8]: after getting married
- Comment [bnchmrk9]: hirsutism
- Comment [bnchmrk10]: and
- Comment [bnchmrk11]: whereas her
- Comment [bnchmrk12]: was
Page 36 — Re: Mr James Seymour, 60-year-old
Letter
Dr Malcolm Still
Rheumatologist
5 Grant St
Fairmont
03/05/2014
Dear Dr Malcolm,
Re: Mr James Seymour, 60-year-old
Thank you for seeing Mr James, who has demonstrated features consistent with gout.
Regarding the patient social history; his alcohol consumption is exceeding the recommended
limit. Mr James’s father was diagnosed with RA.
The patient has had regular episodes of inflammation in his 1st
toe since 2010. He is on
colchicine 500 mcg 2 tablets to be reduced to 1 tablet each 2/24 until pain is relieved (total
dose less than 6 mg in 4 days) and indomethacin 25 mg 2 tablets twice daily. Mr James had
taken allopurinol after his last acute attack, however, he stopped it two months ago before
the current episode.
On 25/04/2014, he presented with 4 weeks into current attack of gout, there was poor
compliance to his medications and he was completely convinced that he has RA. By
examination, 1st
left toe was red and inflamed. I recommended him to continue on his
medications, taking regular paracetamol and oxycodone 5 mg if he is in pain with decrease
alcohol intake. Some investigations were ordered.
Today Mr James is in remission state, I informed him about synovial fluid sample stat next
episode, also he must commence allopurinol now and for long time.
Would you kindly review Mr James? I attached a copy of his pathology results.
Yours sincerely
Doctor
Assessor feedback
Word length 211
Comments Mistakes pertaining to grammar and word choice
are visible. Some case notes can be covered in a
better way. The letter does not meet the
expectations.
Grade C+
Advice 1. Revise grammar.
2. Improve choice of words.
3. Try to finish the letter in 200 words by writing
information in brief wherever possible.
4. Always proofread the letter after finishing
writing it.
Margin comments
- Comment [bnchmrk1]: 60 years old
- Comment [teacher2]: Seymour
- Comment [teacher3]: patient’s family and
- Comment [teacher4]: and his
- Comment [teacher5]: He
- Comment [teacher6]: had
- Comment [teacher7]: On
- Comment [teacher8]: found to be
- Comment [teacher9]: plus
- Comment [teacher10]: . he was also asked to
- Comment [teacher11]: , Mr. Seymour
- Comment [teacher12]: while the x-ray has revealed degenerative changes of the left first metatarsophalangeal joint. Therefore, he has been asked to take allopurinol.
- Comment [teacher13]: Seymour? I have
- Comment [teacher14]: faithfully
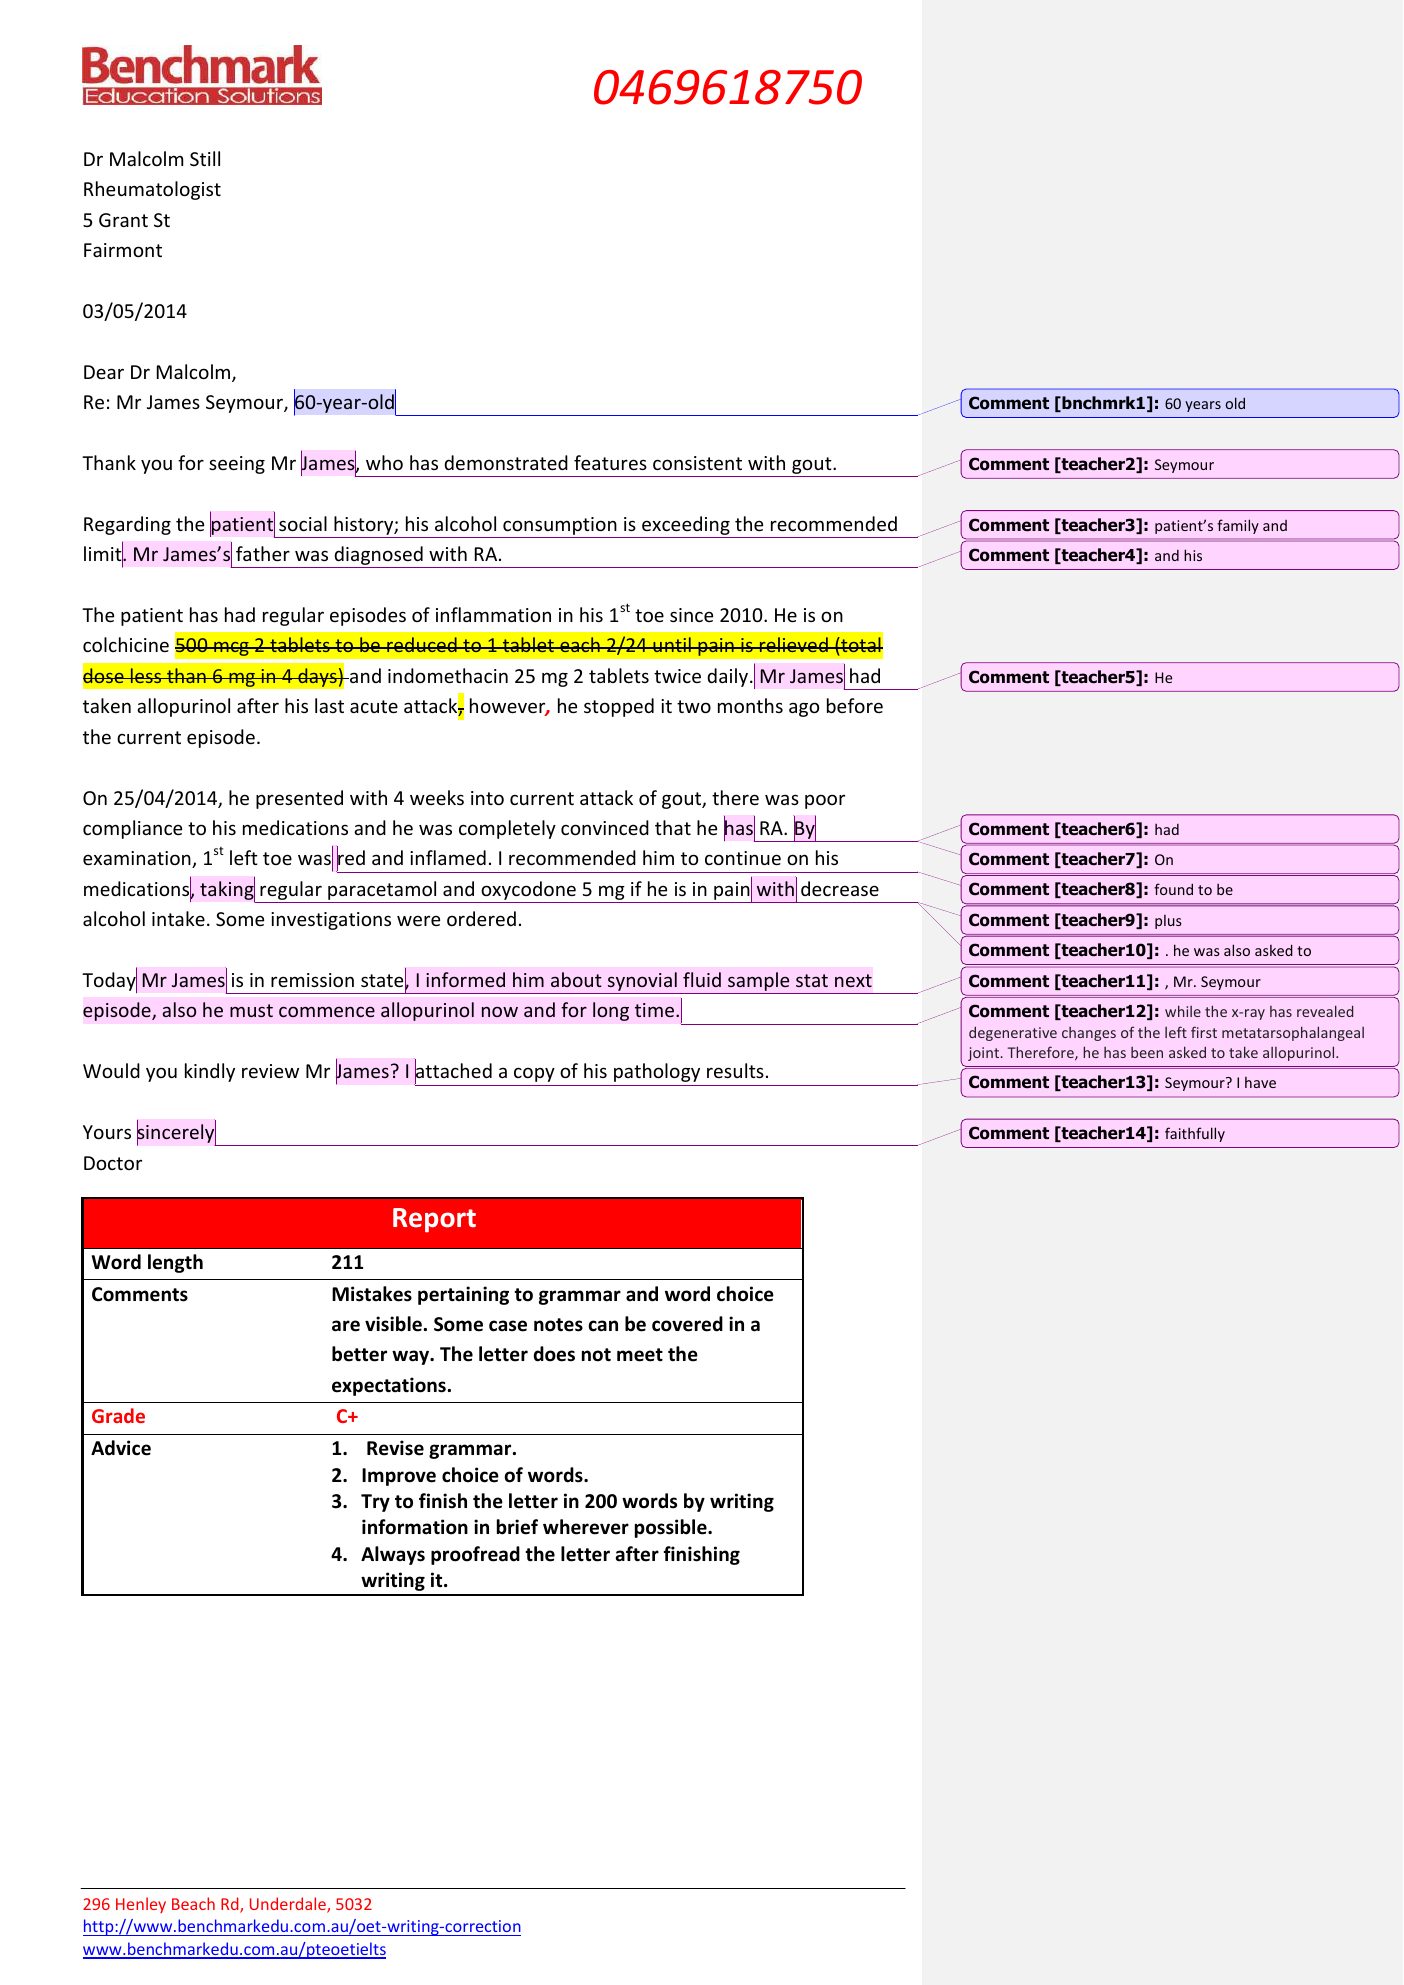
Page 37
Case notes / writing task (OCR)
OCCUPATIONAL ENGLISH TEST
WRITING SUB-TEST: MEDICINE
TIME ALLOWED:
READING TIME:
WRITING TIME:
5 MINUTES
40 MINUTES
Read the case notes below and complete the writing task which follows.
Patient details:
Mr James Seymour is
a 60-year-old man presenting in you
n left large toe.
Name:
Residence:
James Seymour
DOD:
4 Powlet Drive, Clayfield
19/09/53 (Age 60)
Social history:
Retired academic (computer science)
Divorced, no children, lives alone
Non-soker since 1334
Heavy drinker 5-6 beers and 3 wines/day
Observations:
BP 115/70mmHg, HR 68, RR 18, T 37.4°C
Allergies:
Nil known
Father - rheumatoid arthritis (RA) ~ 28 yrs old. Died 75yrs.
Grandparents’ history unknown, died when old.
Mother - smoker, died chest infection aged 71yrs.
PMHx:
Appendicectomy 1963
onlianood - recurrentoroncnius
Regular episodes of inflammation (?gout 1st toe) since 2010 - consulted
Annual influenza vaccine
several doctors
Medication:
Colchicine (Lengout) - 500mcg 2 tabs (stat on attack) then 1 tab each 2/24 until
Indomethacin (Indocid) - 25mg 2 tabs, twice/day.
relief. Total dose ≤ 6mg in 4 days.
On allopurinol arter last acute attack - arter several mins wo symptoms ceased
meds (a couple of mths before current episode).

Page 38
Case notes / writing task (OCR)
Treatment record:
25/04/14
~ 4 wks into current bout of gout.
Indocid taken erratically.
Colchicine started 2 wks into bout, only taken at sub-therapeutic levels.
3rd bout in 8 mths.
No allopurinol for a couple of mths.
Modifies diet to purines. Sometimes wakes at night.
Pt thinks gout meds not working (unlikely).
Given father’s Hx Pt wants referral to rheumatologist to exclude RA.
Moderately inflamed, red first L toe. V painful - Pt irritated. No evidence of
Pt V insistent on possibility of RA; poor compliance with gout management much
involvement of other joints.
Treatment:
more likely.
• Encouraged to comply with gout meds:
- resume full dose indomethacin. Cease either if gastrointestinal (GI) side
- resume full dose colchicine.
Regular paracetamol (4g/day for 3 days, then prn).
effects (diarrhoea from colchicine; upper Gl upset from indomethacin).
Improve dietary compliance and + alcohol intake.
Take oxycodone 5mg bedtime only if sore and can’t sleep; try to cease ASAP.
X-ray L foot, FBE, ESR, LFT, U&E, SUA, CRP.
03/05/14
• Rev. 1/52 to discuss results & referral.
X-ray - minor degenerative changes of L first metatarsophalangeal joint.
FBE: *MCH 32.3pg (Ref Range: 27.0 - 32.0). All other NAD.
*CRP 6.0mg/L (Ref Range: < 3.0)
*Urate 0.48mmol/L (Ref Range: 0.18 - 0.47mmol/L).
Gout episode subsiding.
No drug side effects apart from brief diarrhoea.
Provisional Diagnosis:
Only needed night time oxycodone 3 nights.
Gout.
Treatment:
• Discussed ?synovial fluid sampl
Start allopurinol now, long term; reinforce
Referral to Rheumatologist on patient’s ins
nce with copy of pathology results.
& alcohol.
Using the information given in the case notes, write a letter to Dr Malcolm Still, Rhe
St, Fairmont, for further treatment or investigations.
tologist at 5 Grant
In your answer:
Expand the relevant notes into complete sentences
Use letter format
Do not use note form
The body of the letter should be approximately 180-200 words.

Page 39 — Re: Ms. Lola Duval, D.O.B. :27/05/1990
Letter
Dr Charles White
Bayview Private Hospital
81 Canyon Road
Bayview
01/06/2014
Dear Dr White,
Re: Ms. Lola Duval, D.O.B. :27/05/1990
Thank you for seeing this pleasant 24 years old lady, she has demonstrated features
suggestive of hyperthyroidism most likely, Grave’s disease.
Ms. Duval is a student of engineering at Bayview University.
Regarding the patient’s medical and family history; she has insomnia and anxiety, therefore,
she is occasionally taking sleeping pills. Her mother has been diagnosed with depression.
She visited our clinic yesterday complaining of sudden weight loss of 10 Kg over the last 2
months in spite of eating well. There were symptoms of tremors, palpitations, sweating, heat
intolerance and fatigue. Examination revealed normal vital data and slightly enlarged non-
tender thyroid gland. Exophthalmose with lid lag had seen in her eyes. Routine blood tests,
ECG and thyroid function tests were requested.
Today the results came back showing sinus tachycardia in the ECG, low TSH; less than 0.05
mU/L and elevated T4 and T3. The results have been explained to the patient with the most
likely diagnosis. Furthermore, I have requested thyroid auto-antibody tests and thyroid scan.
Understandably she is anxious, I would very much appreciate your early attention to the
patient.
Please contact me if you have any queries.
Yours faithfully
Doctor
Assessor feedback
Word length 171
Comments An effort to accomplish the task is visible.
Information has been written in logical
paragraphing. However, the letter is shorter than
180 words and many mistakes pertaining to
punctuations, spelling, sentence structures, tenses
and word choice are visible. Some pieces of
information are missing as well. Overall, the letter
requires further improvements.
Grade C
Advice 1. Revise grammar.
2. Be careful with spelling.
3. Improve choice of words.
4. Try to write at least 180 words.
5. Always proofread the letter after finishing
writing it.
Margin comments
- Comment [teacher1]: I am writing to request an urgent review for this
- Comment [teacher2]: who
- Comment [teacher3]: suffers from
- Comment [teacher4]: Ms Duval
- Comment [teacher5]: but
- Comment [teacher6]: Exophthalmos
- Comment [teacher7]: in
- Comment [teacher8]: and would like to be seen by you at the earliest. 296 Henley Beach Rd, Underdale, 5032 http://www.benchmarkedu.com.au/oet-writing-correction www.benchmarkedu.com.au/pteoetielts
Page 40
Case notes / writing task (OCR)
Notes:
You are a doctor at Bayview Private Practice. You are examining a 24-year-old woman who has been
losing a lot of weight.
Name:
DOB:
Ms Lola Duval
Address:
27.05.9
1087 Feather St
Bayview
Medical history:
Laryngitis - 2012
Anxiety
Medications:
Occasional sleeping pill
Insomnia
Family history:
Mother - depression
Social history:
Student at Bayview University (engineering)
Presenting complaint: Pt complaining of unexplained weight loss - 10kg over the last 2/12
Pt eating well, has good appetite
Treatment Record
31.05.1ął
Subjective:
Upon questioning, Pt experienced tremors, episodic palpitations, sweating, heat
intolerance for last 2/12. Associated fatigue in last month.
being unwell
Pt does describe feeling anxious currently - concerned about weight loss,
Objective:
HR - 90
Weight - 55kg
BP - 130/70
Height - 160cm
Temp - afebrile
Slightly enlarged non-tender thyroid gland, tremor in both hands
Eye examination:
Eye movements testing - some exophthalmos with lid lag
Given history, probable hyperthyroidism with overlying anxiety
Routine blood tests, ECG, thyroid function tests
01.06.1ął
Test results:
ECG:
Blood test:
Sinus tachycardia, no other abnormalities
Thyroid Function: TSH < 0.05mU/L (0.4-5mU/L)
Normal FBE, UEC
Elevated T4 and T3:
Free T3 15pmol/L (3.5-6.5pmol/L)
Treatment:
Free T4 40pmol/L (9-26pmol/L)
Order thyroid auto-antibody tests & thyroid scan
Discuss results with Pt - likely hyperthyroidism due to Grave’s disease
Refer to Dr White, thyroid specialist - request early review as Pt anxious
Writing Task:
Using the information given in the case notes, write a letter of referral to the thyroid specialist, Dr White,
Road, Bayview.
at Bayview Private Hospital. Address the letter to Dr Charles White, Bayview Private Hospital, 81 Canyon

Page 41 — Re: Mr. Barry Jones, D.O.B.: 01/04/1972
Letter
Ms Jane Graham
Newtown Occupational Therapy
10 Johnston St
Newtown
20/06/2015
Dear Ms. Graham,
Re: Mr. Barry Jones, D.O.B.: 01/04/1972
I am writing to you regarding Mr. Jones who presented to the clinic asking for returning to his work after back
injury incident 3 months ago.
Regarding the patient’s family and social history; he is married and working as forklift driver in a huge
warehouse. Moreover, his job requires prolonged sitting and sometimes heavy lifting. Mr. Jones is on
naproxen and carisoprodol (muscle relaxant).
Back to 21/03/2015, Mr. Jones was diagnosed with severe lower back strain due to lifting heavy box off floor at work. His
X-ray showed no disc problems. As a result, the patient was advised to walking daily with gradual increase to
time/distance. He was prescribed naproxen and carisoprodol. He also referred to physiotherapist furthermore, I gave him
certificate with 30 days off work to be given to the employer.
After regular visits and follow up over the last 3 months, Mr. Jones was attending his physiotherapist
appointments regularly and was exercising. However On review today, he is still in pain and stiff on movement,
he is recovering well. He is walking 30 minutes per day but feel tired after that. Pain is increasing after nearly
30 minutes of sitting or lying down. But, he is bored and disheartened and wants to return to work.
I would very much appreciate your assessment of his workplace. Baring in mind he should take regular breaks
during work and does not lift any heavy objects.
Yours sincerely,
Doctor
Assessor feedback
Word length 217
Comments The letter has many inaccuracies pertaining to
articles, tenses, word choice and sentence
formation. Some important information is missing
while some has been repeated. Overall, the letter
does not meet the expectations.
Grade C
Advice 1. Revise grammar.
2. Improve choice of words.
3. Try to finish the letter in 200 words by writing
information in brief wherever possible.
4. Repetitions of information are visible.
5. Always proofread the letter after finishing
writing it.
Margin comments
- Comment [teacher1]: is
- Comment [teacher2]: a
- Comment [teacher3]: a
- Comment [teacher4]: On
- Comment [teacher5]: a
- Comment [teacher6]: walk
- Comment [teacher7]: in
- Comment [teacher8]: was
- Comment [teacher9]: for
- Comment [teacher10]: Over
- Comment [teacher11]: has been
- Comment [teacher12]: and followup
- Comment [teacher13]: , on
- Comment [teacher14]: bearing
- Comment [teacher15]: that

Page 42 — Re: Mrs. Mary Clarke, D.O.B.: 17/09/1960
Letter
Dr Penny Clifton
Thoracic Surgeon
Department Of Cardiothoracic Surgery
Central Hospital
Main Street
Stillwater
22/08/2015
Dear Dr. Clifton.
Re: Mrs. Mary Clarke, D.O.B.: 17/09/1960
I am writing to refer Mrs. Clarke who has demonstrated features suggestive of bronchogenic
carcinoma. Your help would be highly appreciated.
Mrs. Clarke is an office clerk and married. She is a heavy smoker for more than 30 years with
consumption of 30-35 cigarettes per day. Moreover, she has no allergies and her mother died
from laryngeal carcinoma. She presented once with sore throat upon which she was
prescribed Augmantin.
On review today, Mrs. Clarke has been suffering from dry non-productive cough with no
haemoptysis for the last 7 weeks. Associated with chest pain (heaviness) and shortness of
breath which is more noticeable during night, however she can exercise well, do her shopping
and walking. Respiratory examination revealed right mid-zone consolidation accompanied
with monophonic wheeze. Other systems’ examination were normal; no cyanosis, no cervical
lymphadenopathy and no hoarseness of voice. Chest X-ray and CT scan showed right middle
lobe atelectasis with enlarged right hilum.
In view of the above, my provisional diagnosis is bronchogenic carcinoma. I am referring her
for further investigations (bronchoscopy with biopsy) and assessment. If you have any query,
please contact me.
Yours sincerely,
Doctor
Assessor feedback
Word length 185
Comments Some issues pertaining to sentence formation and
word choice are visible. There are mistakes of
tenses and punctuation as well. Overall, the letter
requires further improvements.
Grade C+
Advice 1. Revise grammar and sentence formation.
2. Improve word choice.
3. Always proofread your letter after finishing it.
Margin comments
- Comment [bnchmrk1]: has been
- Comment [bnchmrk2]: associated
- Comment [bnchmrk3]: systemic and respiratory examinations
- Comment [bnchmrk4]: , and there was
- Comment [bnchmrk5]: or

Page 43
Case notes / writing task (OCR)
Mrs Mary Clarke (born on 17 September 1960) is a patient in your General Practice.
Patient details
Name:
Mrs Mary Clarke
Address:
Riverside
26 Marine Drive
Social background:
54-year-old office clerk
Smokes 30-35 cigarettes per day (>30 yrs)
Married, lives at home with husband and 20-year-old son
Family/medical history:
Mother died 66 y.o. - laryngeal carcinoma
Father (coal miner) died 54 y.o. - mining-related lung disease
Nil medication
No known allergies
04.07.15
Patient presented with sore throat, body aches, fever and cough.
Prescription: Augmentin (penicillin)
22.08.15
Presenting complaint:
7-week Hx of dry non-productive cough (no haemoptysis)
Cough commenced with flu-like symptoms → cleared with Augmentin
heaviness” in chest
Associated mild shortness of breath (esp. at night) and “strange sensation of
Nil fever, night sweats or rigors
Exercise tolerance OK - chores, shopping, could walk up 2 sets of stairs
Examination: T: 36.7°C, P: 80 regular, Ht: 165cm, Wt: 68kg
mid-zone
Respiratory exam - signs of consolidation associated with monophonic wheeze in R
No hoarse voice/Horner’s syndrome
No cyanosis/dyspnoea/ascites
No cervical lymphadenopathy
No hepatosplenomegaly/bone pain
Systems review - GIT & CV normal
Sputum cytology - normal
Chest X-ray and CT - R middle lobe atelectasis, enlarged R hilum
Assessment: ?Bronchogenic carcinoma
Plan:
Refer to thoracic surgeon for follow-up investigations (bronchoscopy, biopsy) and
Counselled on potential diagnosis and need for further investigations
assessment
Writing Task:
Using the information given in the case notes, write a letter of referral to the thoracic surgeon, Dr Penny
Clifton, seeking follow-up investigations and assessment. Address the letter to: Dr Penny Clifton,
Department of Cardiothoracic Surgery, Central Hospital, Main Street, Stillwater.
In your answer:
Expand the relevant notes into complete sentences
Use letter format
Do not use note form
The body of the letter should be approximately 180-200 words.

Page 44 — Re: Mrs. Lucy Clarke, D.O.B.: 11/03/1951
Letter
Dr David Smith
Cardiologist
Emergency Department
Main Hospital
Coast City
20/09/2015
Dear Dr. Smith,
Re: Mrs. Lucy Clarke, D.O.B.: 11/03/1951
I am referring Mrs. Clarke urgently as her features are highly suggestive of an unstable
angina.
Mrs. Clarke is a retired office clerk. She is non- smoker and drinks occasionally. She has been
suffering from DM for 14 years now, in addition to, hyperlipidemia and hypertension since
2005. Her mother was diagnosed with MI and died at age of 59 from ischemic stroke. Mrs.
Clarke is on sitagliptin 100mg (p.o) mane, insulin 25 units (s.c) b.d., atrovastatin 40mg (p.o)
mane and irbesartan 75mg (p.o) mane.
On review today, she has been complaining of a chest pain on exertion for the last week. The
pain was presented 3 times with less than 15 minutes duration each. Moreover, it was
radiated to the left arm and was relieved by rest. The patient developed dyspnea, however
there were no palpitation, no orthopnea and no paroxysmal nocturnal dyspnea. Mrs. Clarke is
worried and convinced that she had a heart attack. On examination, her vital data were
normal with normal resting ECG.
In view of the above, my provisional diagnosis is unstable angina. She needs a hospital
admission for your further management. Would you kindly advise the patient on the risks of
MI?
Yours sincerely,
Doctor
Assessor feedback
Word length 198
Comments There are only minor inaccuracies of grammar and
sentence formation. The letter meets the
expectations.
Grade B+
Advice 1. Revise grammar.
2. Keep up the good work!
Margin comments
- Comment [teacher1]: a
- Comment [teacher2]: complained of
- Comment [teacher3]: of
- Comment [teacher4]: in the past week.
Page 45
Case notes / writing task (OCR)
Name:
Mrs Lucy Clarke
DOB:
11 March 1951
Residence:
23 Mountain Drive
Coast City
Social background: 64-year-old retired office clerk
Independent, lives at home with husband
Non-smoker, social drinker
20.09.15
Presenting complaint:
1 week history central crushing chest pain on exertion (3x, <15 mins duration)
Associated dyspnoea, radiation of pain down L arm
Relieved by rest
No palpitations, no orthopnoea (difficulty breathing on lying down), no paroxysmal
nocturnal dyspnoea (difficulty breathing at night)
Pt anxious - believes had a heart attack
Past medical history:
2001 - diabetes mellitus (DM) Type II (currently stable)
2003 - hyperlipidaemia
2005 - hypertension (HT)
Medications:
Sitagliptin (Januvia) 100mg per oral (p.o.) mane
Insulin (NovoMix30) 25 units subcutaneously (s.c.) b.d.
Atorvastatin (Lipitor) 40mg p.o. mane
Irbesartan (Avapro) 75mg p.o. mane
Family history: Mother - acute myocardial infarction (MI) at 57 y.o.; died of ischaemic
stroke at 59 y.o.
Examination:
T - 36.7°C. P - 80 regular, Ht - 164cm, Wt - 65kg
No peripheral oedema
Systems review - normal
Resting ECG - normal
Provisional diagnosis:
Unstable angina
Plan:
Hospital admission for urgent assessment
Referral to Emergency Department cardiologist for update & further managi
Counsel patient - advised on serious risk of MI
Writing Task:
cardiologist, Dr Smith, Address the letter to: Dr David Smith, Cardiologist, Emergency Qepartment
Using the information in the case notes, write a letter of referral to the Emergency Department
Main Hospital, Coast City.
In your answer:
• Expand the relevant notes into complete sentences
• Use letter format
• Do not use note form
The body of the letter should be approximately 180-200 words.

Page 46 — Re: Ms Dolores Hoffmann, D.O.B:22/06/1986
Letter
Dr John McLennan
Psychiatrist
Royal Mental Health Clinic
177 Park Avenue
Newtown
29/11/2014
Dear Dr McLennan,
Re: Ms Dolores Hoffmann, D.O.B:22/06/1986
Thank you for seeing Ms Hoffman, a 28-year-old sales assistant , whose features are
consistent with reactive depression and anxiety .Your co-operation would be greatly
appreciated .
Ms Hoffmann is single and lives alone in Australia.
On25/04/2014, initially, Ms Hoffmann complained of wooziness and stress at work. additionally
,last night, she fainted at pub after taking several cocktails. Nine-months later, she presented
with features which are consistent with upper respiratory tract infection, upon which,
erythromycin was prescribed. she was anxious about having Epstein bar virus as her colleague.
one -month later, she presented with depressed mood, nightmares, insomnia, loss of appetite
and poor libido. moreover, she had poor memory, poor concentration, loss of pleasure ,loss of
confidence. Unfortunately ,she split up with her boy-friend. In addition, she had intent to
quitting her job. consequently, temazepam was prescribed .
Today,Ms Hoffmann reported poor compliance on temazepam regime. In addition she accepted
to be seen by psychiatrist. ·
In view of the above, I am referring her for further assessment and management. For any
queries, please feel free to contact me.
Yours sincerely,
Doctor
Assessor feedback
Word length 178
Comments An effort to accomplish the task is visible.
However, the letter has inaccuracies pertaining to
punctuation, capitalisation and word choice.
Overall, the letter does not meet the expectations.
Grade C
Advice 1. Revise grammar.
2. Be careful with capitalization.
3. Improve choice of words.
4. Unnecessary pieces of information are visible.
5. Always proofread the letter after finishing
writing it.
Margin comments
- Comment [teacher1]: also mentioned in conclusion
- Comment [teacher2]: A
- Comment [teacher3]: the earlier
- Comment [teacher4]: a
- Comment [teacher5]: were
- Comment [teacher6]: S
- Comment [teacher7]: suspected having contracted
- Comment [teacher8]: O
- Comment [teacher9]: M
- Comment [teacher10]: was considering
- Comment [teacher11]: C
- Comment [teacher12]: T
- Comment [teacher13]: with
- Comment [teacher14]: T
- Comment [teacher15]: However,
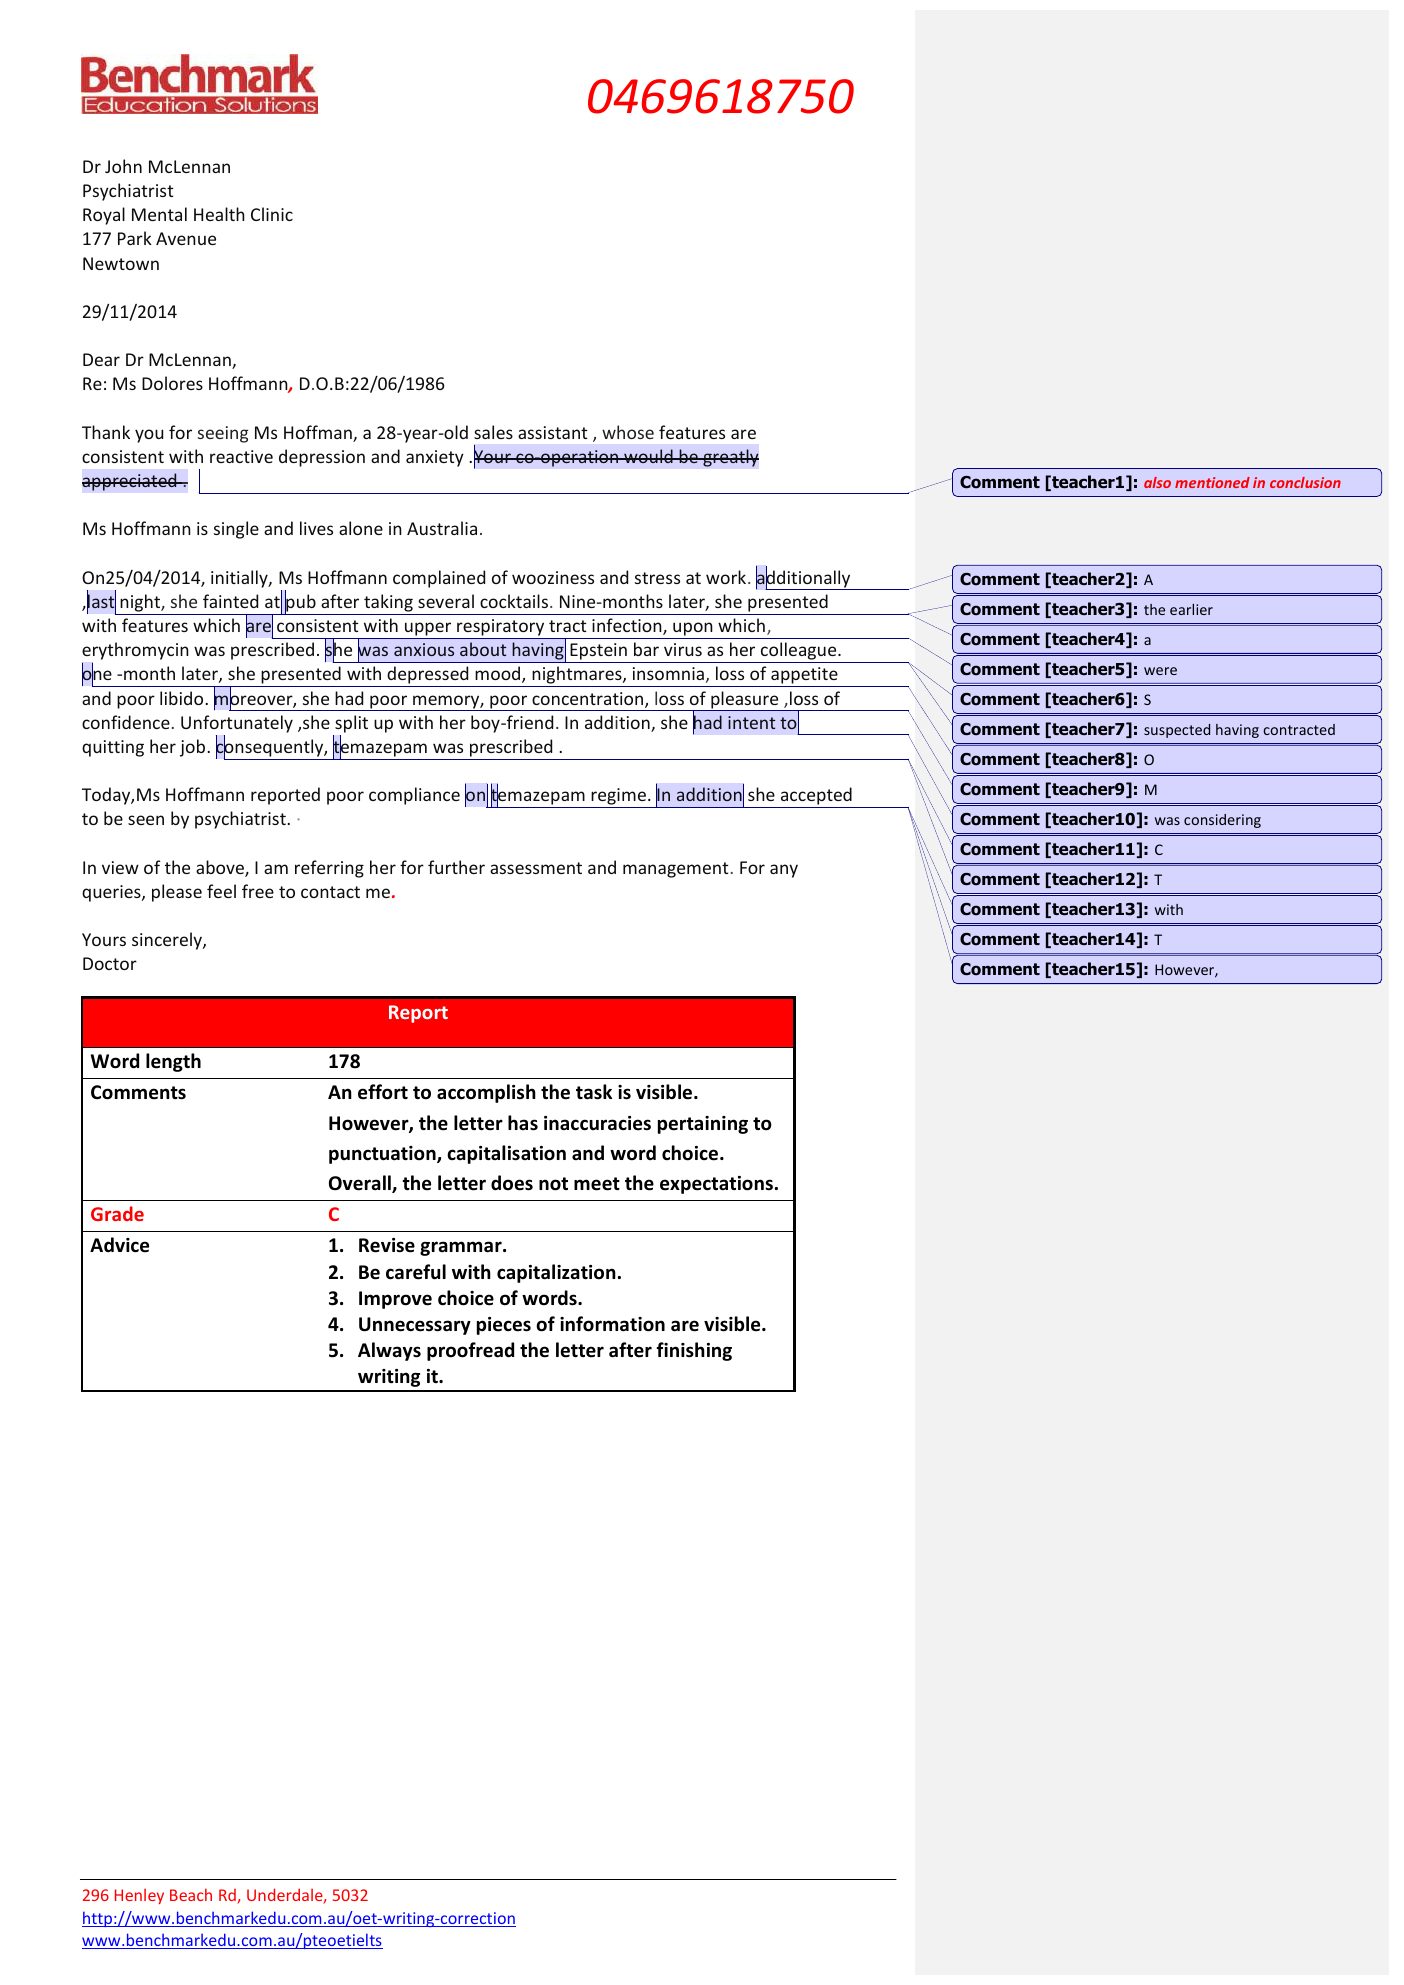
Page 47 — RE: Joshua Vance DOB: 17/11/2013
Letter
Admitting Officer
Emergency Department
Children’s Hospital
Newtown
18/01/2014
Dear Sir/Madam,
RE: Joshua Vance DOB: 17/11/2013
I am referring Joshua Vance, a 2-month-old infant , who has recently developed constipation with mild
dehydration. Further assessment would be highly appreciated.
Joshua is the first baby of his parents. He was delivered vagnially after a full-term pregnancy with normal
weight and there were neither perinatal nor neonatal compilations.
On 31/12/2013, Joshua’s mother attended, for a routine baby check, concerning about her baby’s bowel
actions. He had only one bowel action every three days with hard stools. Examination revealed normal findings
with a normal weight gain. Consequently, his mother was reassured and was advised to give him some water
along with breast feeding. Next visit, the mother was worried about her baby because he was waking up crying
every half hour throughout the night with no improvement of his symptoms. Examination revealed normal
hydration; therefore, Coloxyl drops was prescribed and increasing water intake for the baby was
recommended.
Today, Joshua’s mother reported that he has not passed stool for the last five days; besides, refusing feeds,
vomiting once and there were no wet nappies. Examination showed that the baby is irritable and mildly
dehydrated.
In view of the above, my provisional diagnosis is constipation with mild dehydration. I am therefore referring
this patient for further management. For any queries, please do not hesitate to contact me.
Yours faithfully,
Doctor
Assessor feedback
Word length 217
Comments There are mistakes pertaining to sentence
formation, punctuation, spelling and word
choice. Nevertheless, the letter meets the
expectations.
Grade B
Advice 1. Revise grammar.
2. Be careful with spelling.
3. Improve choice of words.
4. Always proofread the letter after finishing
writing it.
Margin comments
- Comment [teacher1]: vaginally
- Comment [teacher2]: complications
- Comment [teacher3]: and expressed concerns
- Comment [teacher4]: including
- Comment [teacher5]: On the
- Comment [teacher6]: still
- Comment [teacher7]: previous
- Comment [teacher8]: were
- Comment [teacher9]: the
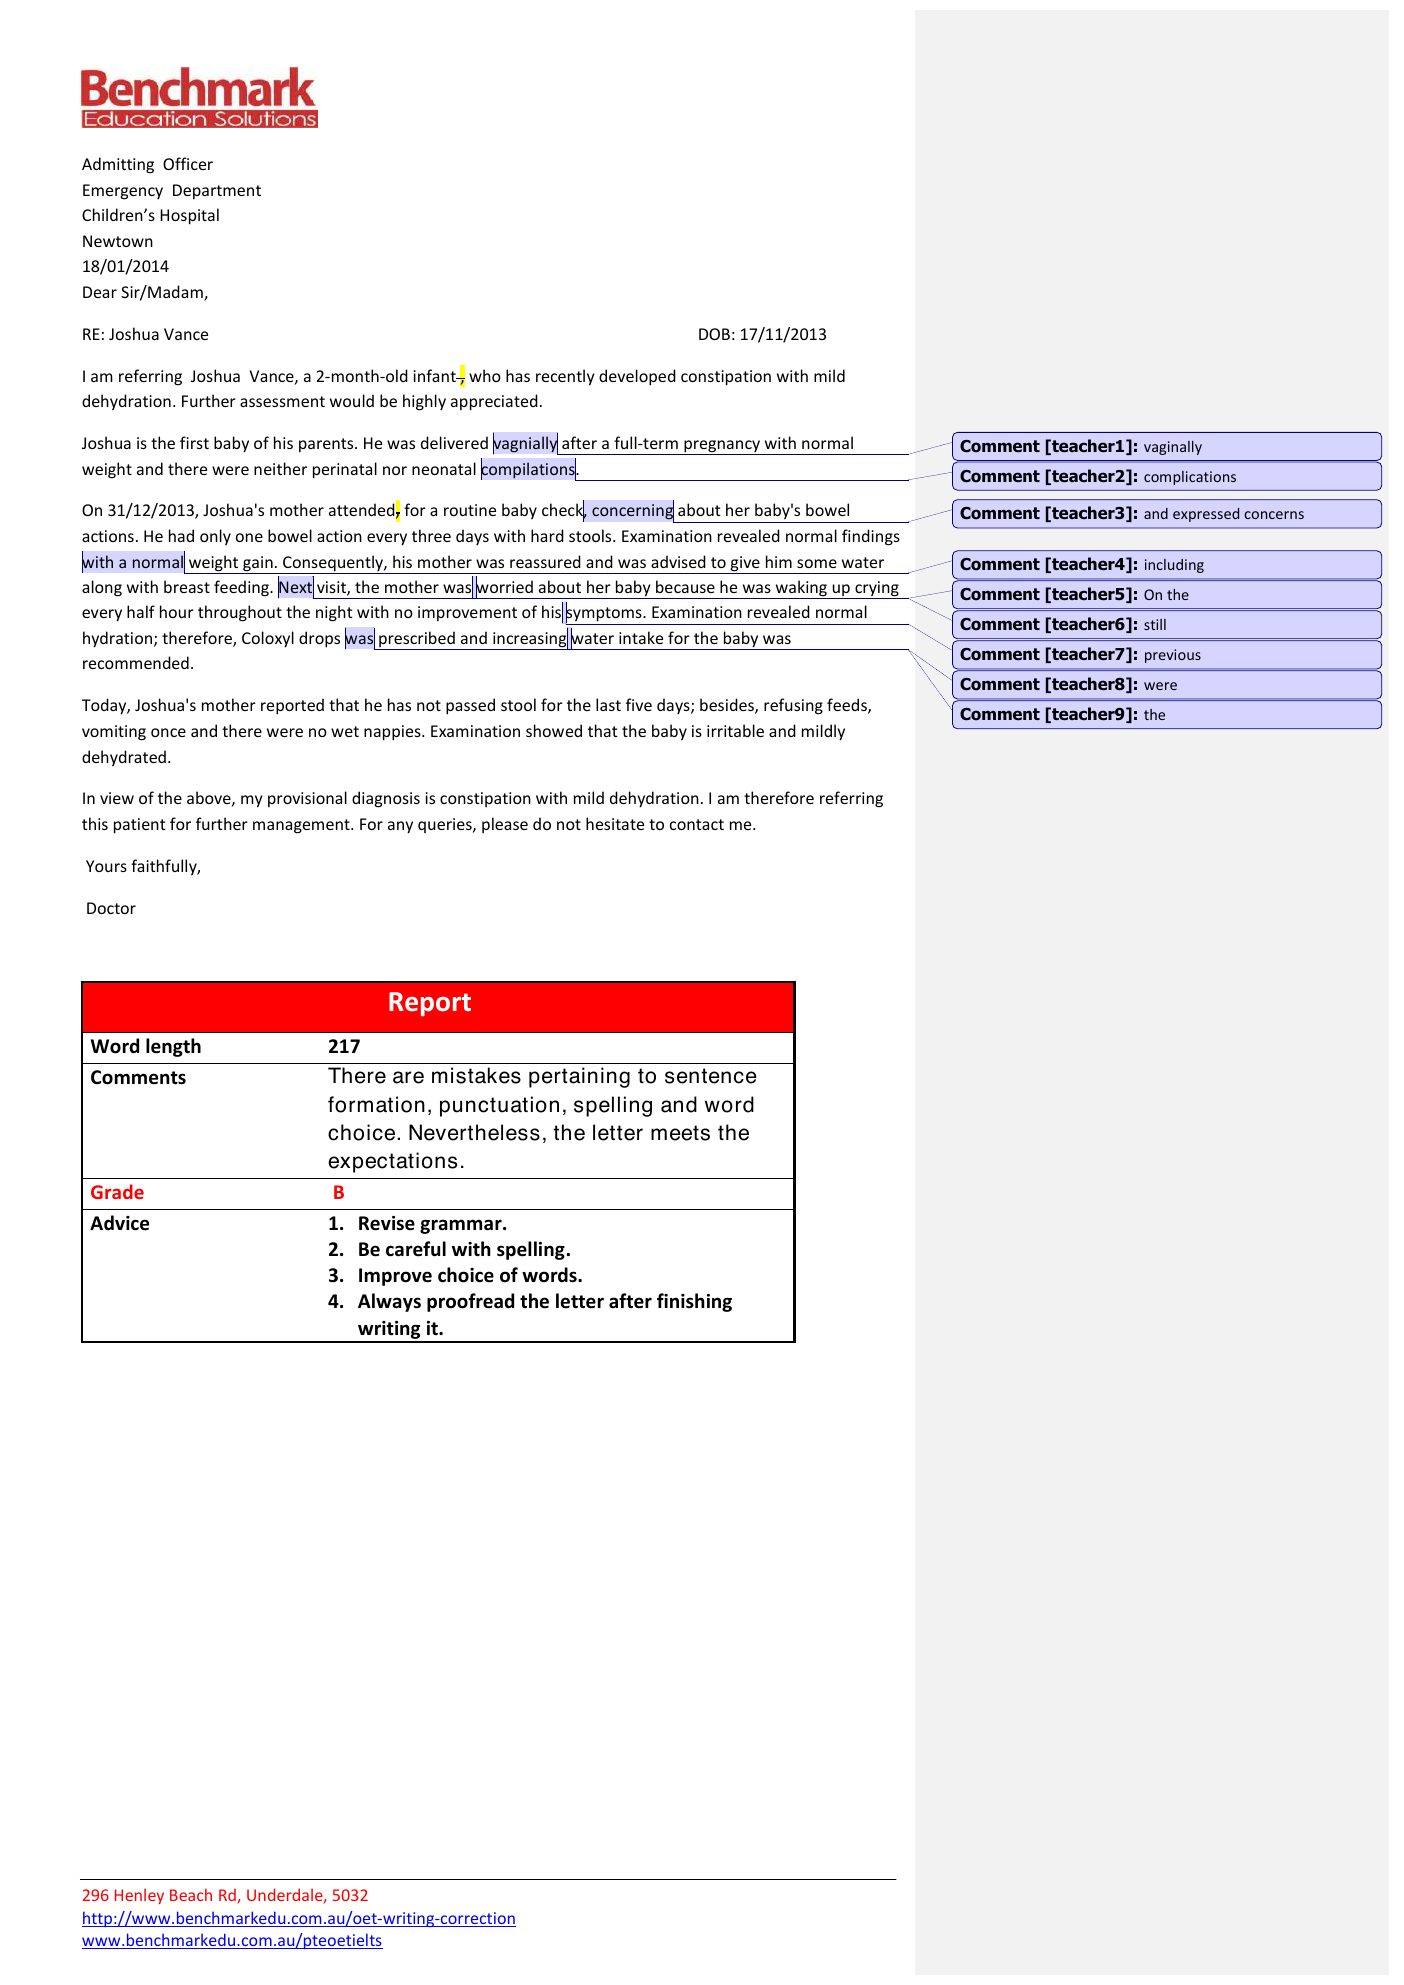
Page 48 — Re : Mr Michael Weir, 44 years of age
Letter
Dr M McLaren
Neurologist
Suite 3
67 The Crescent
Newtown
Dear Dr McLaren,
Re : Mr Michael Weir, 44 years of age
Thank you for seeing Mr Weir, whose symptoms and signs are indicative of multiple sclerosis.
Your further management would be highly appreciated.
Mr Weir is a married real estate agent and has three children. Regarding his medical history,
he has been taking Zoloft for depression since 2012. Please note, he is a smoker.
In 29/06/2014, Mr Weir complained of tiredness and stress. Her examination reveled nothing
abnormal except for high body mass index; therefore, laboratory tests were ordered. On the
next review visit, he reported that he was still tired in addition to a weakness in his left leg.
High level of cholesterol with low Hb was noticed in the tests’ results. Consequently, the
patient was advised on lifestyle changes such as increasing exercise, decreasing saturated fats
intake and smoking cessation. Besides, a review visit was scheduled in one month.
Today, Mr Weir reported two recent blackouts with dizziness. Moreover, he complained of
mood swinging, stress, loss of energy beside tingling in his both hands. The examination
revealed loss of sensation in his both hands with a diminished left patellar reflex.
Consequently, head and neck CT scan was ordered.
In view of the above, I am referring the patient for MRI and your full neurological assessment.
For any queries, please dont hesitate to contact me.
Yours sincerely,
Doctor
Assessor feedback
Word length 214
Comments An effort to finish the task is visible. Flow of information is
logical and relevant case notes have been covered well.
However, there are minor inaccuracies related to spelling,
word choice and sentence formation. Nevertheless, the letter
meets the expectations.
Grade B
Advice 1. Pay a little more attention to grammar and word choice.
2. Be careful of spelling and avoid contractions such as don’t.
Margin comments
- Comment [benchmark1]: a 44-year-old real estate agent
- Comment [benchmark2]: the patient’s
- Comment [benchmark3]: revealed
- Comment [benchmark4]: test
- Comment [benchmark5]: swing
- Comment [benchmark6]: besides
- Comment [benchmark7]: do not

Page 49 — Re: Mr. Barry Jones D.O.B 01/04/1972
Letter
Ms Jane Graham
Occupational Therapist
Newtown Occupational Therapy
10 Johnson Street
Newtown
20/06/2015
Dear Ms Graham,
Re: Mr. Barry Jones D.O.B 01/04/1972
Thank you for seeing Mr. Jones, a 44-year-old forklift who desires for returning to work. Your assessment
would be highly appreciated.
On 21/03/2015, Mr. Jones presented with a 4-day history of back pain, after he had lifted a heavy box off
floor at his work. The x-ray revealed no disc problems. Therefore, he was diagnosed with a severe low back
strain, for which he was prescribed naproxen and carisoprodol. In addition, he was referred to a
physiotherapist and was given a medical certificate of a 30-day duration off work. On the next visit, the
patient was still in pain and complained of movement stiffness. Although he was complaint to
physiotherapy, he was concerned about the painful exercises. His sick-leave was extended another month.
One month later, Mr. Jones attended complaining of severe movement stiffness and pain during walking.
Therefore, he was advised on increasing naproxen dose with an extension of his sick-leave duration.
Today, Mr. Jones reported that he was still in pain, however; the range of movement was improving. He
was very bored and wanted to return to his work. Therefore, he was advised to return to work with no
lifting and to take breaks regularly.
In view of the above, I am referring the patient for assessment of his workplace and your advice. Should
there be any queries, please do not hesitate to contact me.
Yours sincerely,
Doctor
Assessor feedback
Word length 228
Comments Wording needs improving to enhance coherence
and reduce the length of the letter. Order of
content is good. Revision on grammar and
capitalisation would be useful.
Estimated Grade B-
Advice 1. Revise grammar and vocabulary.
2. Try to finish the letter in 200 words by writing
information in brief wherever possible.
3. Always proofread the letter after finishing
writing it.
Commented [AH1]: driver,
Commented [AH2]: would like to return
Commented [AH3]: the
Commented [AH4]: for 30 days
Commented [AH5]: compliant with
Commented [AH6]: pain during his
Commented [AH7]: for
Commented [AH8]: to increase his
Commented [AH9]: , and was given

Page 50 — Re: Mr Michael Weir, D.O.B.: 20/09/1970
Letter
Dr M McLaren
Neurologist
Suit 3
67 The Cresent
Newtown
09/08/2014
Dear Dr MClarent
Re: Mr Michael Weir, D.O.B.: 20/09/1970
Thank you for seeing Mr Weir, whose features are suggestive of multiple sclerosis. Your
further assessment and management are highly appreciated.
Mr Weir, who is an overweight real estate agent, has been suffered from depression for 2
years for which takes Zolof.
Initially, the patient presented to me for his regular check-up on 29/06/2014. At that time, he
reported weakness in his general health and his blood pressure was low. On the review visit
one week later, he reported weakness in the left leg. His blood tests showed
hypercholesterolemia and anaemia. Therefore, he was advised to modify his lifestyle and to
stop smoking.
Today, Mr Weir presented with complaints of dizziness, two recent blackouts and a tingling
sensation in his both hands. Besides, the weakness in the left leg has been persistent. His
neurological examination revealed loss of both sharp and blunt sensations on both hands in
addition to a diminution in the left Pallar reflex. For those reasons, I have ordered a CT for the
head and Lumar spine to rule out either spinal pathological conditions or central causes.
In view of the above, my provisional diagnosis is possible multiple sclerosis. Thus, I am
referring this patient to you for further assessment and possible MRI imaging. Please contact
me, for further information.
Yours sincerely,
Doctor
Assessor feedback
Word length 213
Comments Apart from minor inaccuracies, the letter meets
the expectations.
Grade B+
Advice 1. Always try to write information in brief form
(comment 3).
2. Use synonyms.
3. Keep up the good work!
Margin comments
- Comment [bnchmrk1]: will/would be highly
- Comment [bnchmrk2]: suffering
- Comment [bnchmrk3]: During initial visit on 29/06/2014, the patient
- Comment [bnchmrk4]: came (use synonyms wherever possible)
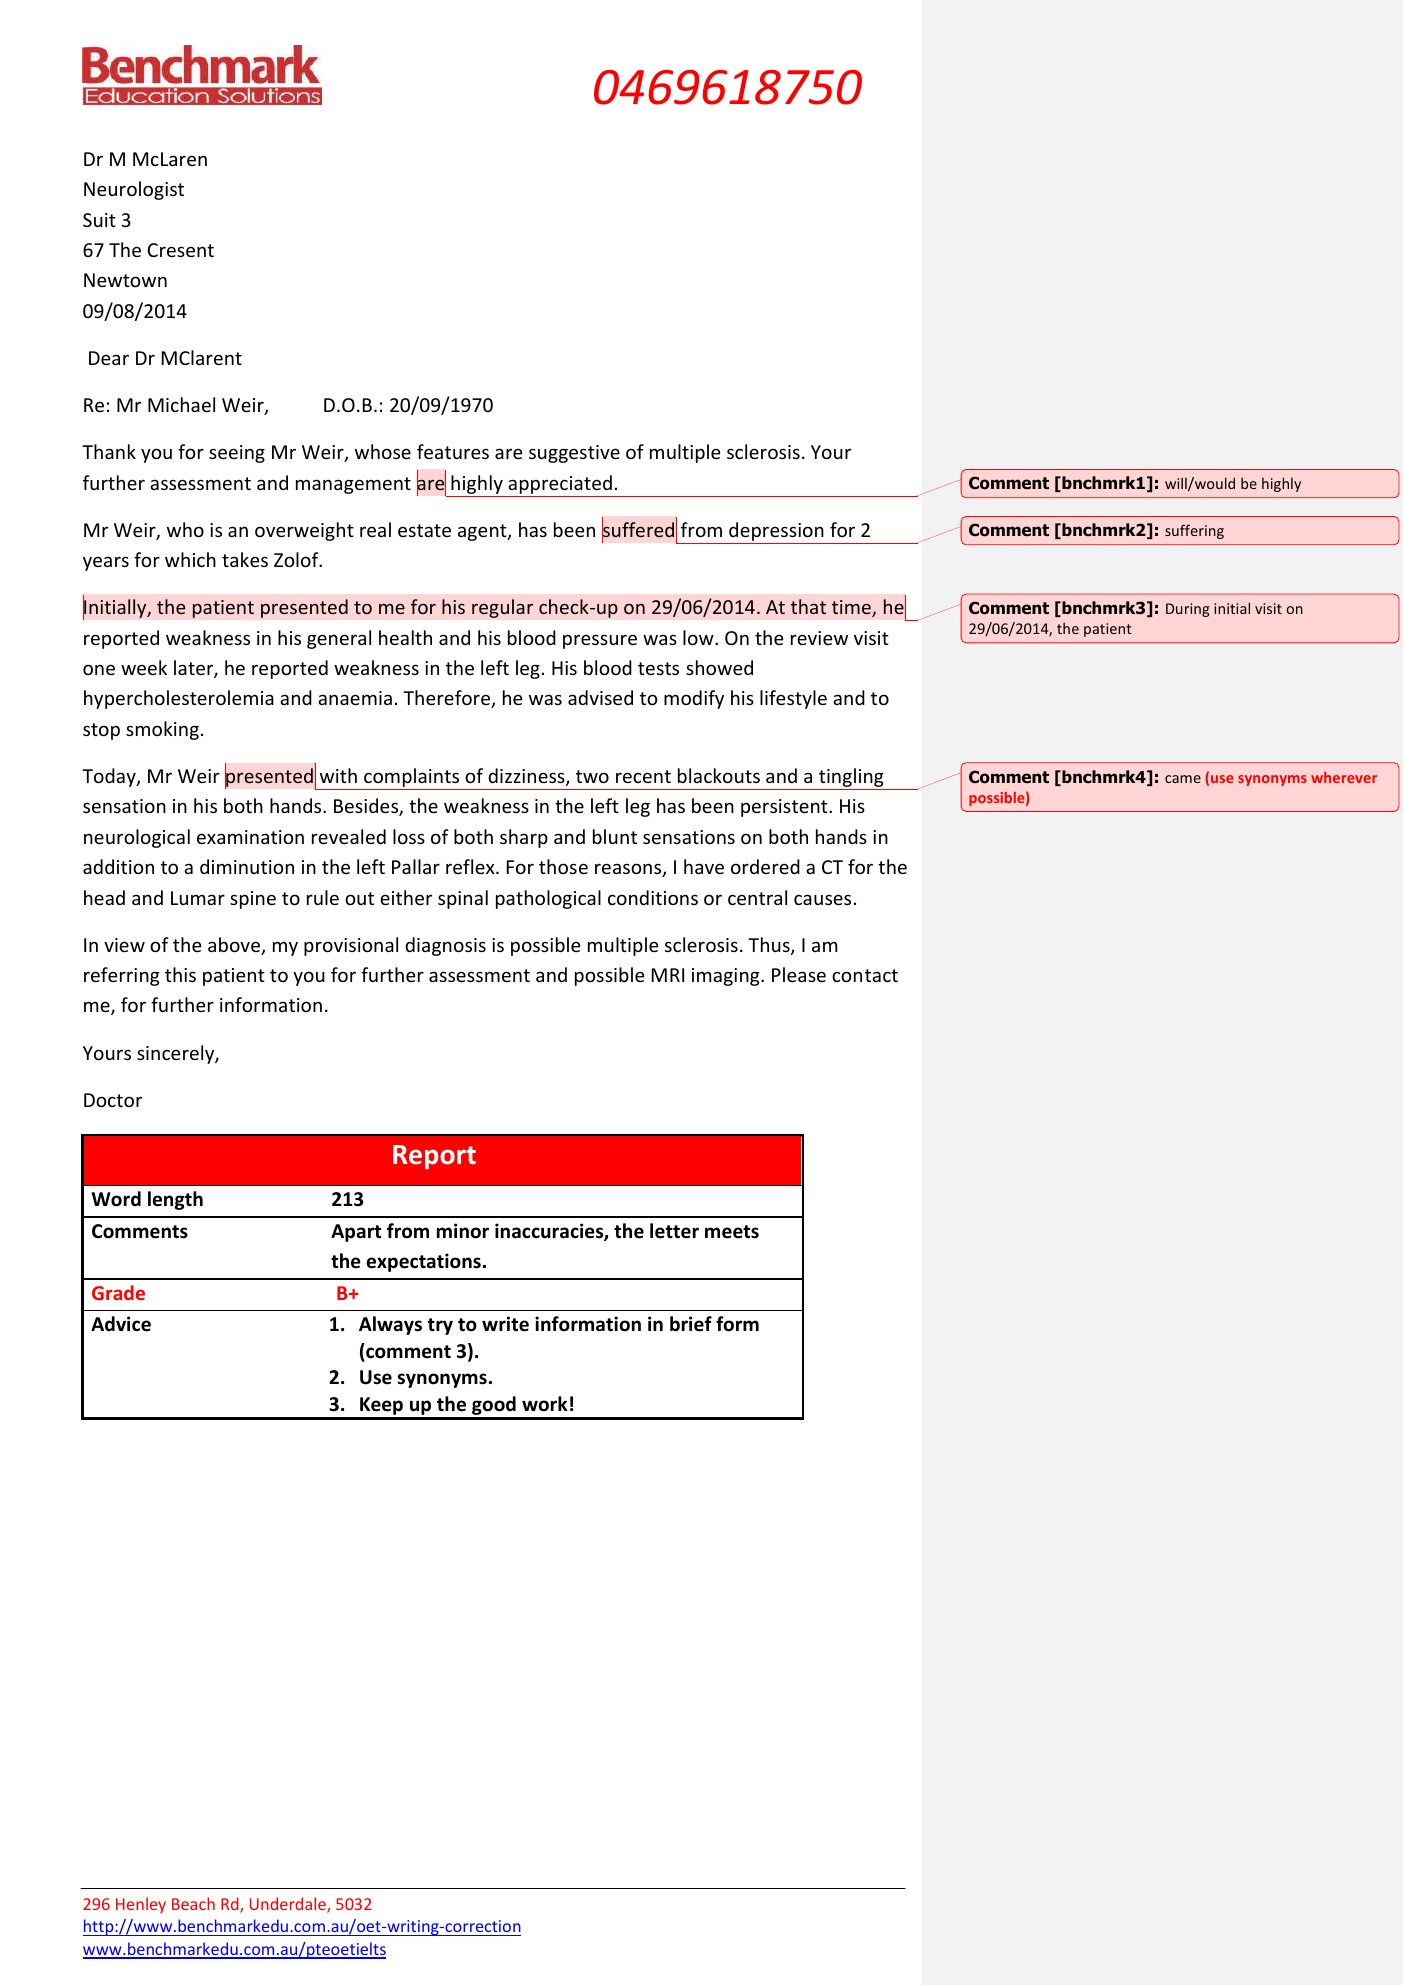
Page 51 — Re: Ms Hannah Modi D.O.B.: 22/ 06 /1987
Letter
Dr Hazem Gouda
Psychiatrist
Royal mental health clinic
177 Park Avenue
Newtown
29 11 2017
Dear Dr Gouda,
Re: Ms Hannah Modi D.O.B.: 22/ 06 /1987
I am writing to refer Ms Modi, a 30-year-old sales assistant lady, who presented with
symptoms and signs suggestive of depression. Your further management is appreciated.
Ms Modi is a single lady who lives with a boyfriend only. Unfortunately, she is a smoker and
alcohol drinker. Moreover, she experiences a lot of stress during her busy work.
On 11/10/2016, Ms Modi came with history of loss of consciousness (5-10 minutes) and one
attack of vomiting following heavy drinking on the previous night. Her examination was
unremarkable together with normal routine blood tests after that she was reassured.
On 07/06/2017, Ms Modi presented with several moles on both sides of her neck to which
only observation was advised. 4 weeks later, she presented again with a picture of chest
infection. In addition, she was concerned about being avoided by her colleague and about
having EBV infection. Reassurance was offered and Erythromycin was prescribed for
nonspecific mild elevation of neutrophils.
After about 2 months, she presented with clear symptoms of depression and anxiety due to
the increasing work load. Moreover, she has splitted up with her boyfriend and considering
leaving the job aiming to have rest. Unfortunately, she doesn’t accept to be seen by
psychiatric; moreover, she was uncompliant to the prescribed temazepam.
Today, Ms Modi has accepted my recommendation; therefore, I am referring her with
provisional diagnosis of depression and anxiety. I will be glad if you manage her condition.
Yours sincerely,
Doctor
Assessor feedback
Word length 239
Comments The letter ably addresses the case notes. Flow of
information is logical and paragraphing is relevant.
Sentence formation is broadly fine. However,
mistakes pertaining to spelling, articles, word
choice and tenses are visible. Also, the letter is
longer than recommended 200 words.
Grade C+
Advice 1. Since this is a letter to a psychiatrist,
unimportant medical issues can be written in
summary form to reduce the length.
2. Be careful of spelling and punctuation marks.
3. Learn more vocabulary and word choice.
4. Revise grammar.
Margin comments
- Comment [bnchmrk1]: her boyfriend
- Comment [bnchmrk2]: S (there is nothing unfortunate about it)
- Comment [bnchmrk3]: work-related stress
- Comment [bnchmrk4]: the
- Comment [bnchmrk5]: instance
- Comment [bnchmrk6]: During subsequent visits, she complained of moles on both sides of the neck and
- Comment [bnchmrk7]: split
- Comment [bnchmrk8]: is
- Comment [bnchmrk9]: does not
- Comment [bnchmrk10]: a
- Comment [bnchmrk11]: she is not complaint with her temazepam and refused to be seen by a psychiatrist
- Comment [bnchmrk12]: Your assessment and management of this patient’s condition will be highly appreciated.

Page 52
Case notes / writing task (OCR)
Patient Name:
Patient History:
DOB 22.06. *
(Ms)
Allergic to penicillin.
Social History:
Sales assistant - ladieswear in a department store.
Single woman - no family in Australia; lives with long-term boyfriend.
At pub last night with friend. 2 glasses wine + several cocktails. Then fainted
No symptoms gastroenteritis or URTI. Work very busy/stressful. Feelsiwoozy”
5-10mins unconscious → vomited once. No Hx fits/seizures/incontinence.
today. No appetite. Requested check-up.
OE: slightly pale; T 36°, P 72 reg, BP 120/70, medical certificate (Med. Cert.)
- 1 day, rest, watch for new symptoms.
Blood tests (FBE, LFT, U&E): normal
Skin check. Several moles L and R neck - ok. Advised to monitor for changes.
URTI since 2/52, yellow-green sputum; SOB, tight chest, wheezy; lethargic.
Smoker
Anxious re. EBV (Epstein-Bar virus) - work colleague is off with it.
Reassurance.
Rec. rest. Med. Cert. given for 2 days.
HAEMATOLOGY:
Ordered bloods.
Haemoglobin
124g/L
(115-165)
PCV
4.8 x 10/L
MCV
0.37
(3.80-5.50 × 101/L)
(0.35-0.4/)
MCH
88 fL
(78-99)
White Cell Count
30 pg
7.0 x 10/L
(27-32)
2.8 x 10/L
8.0 X 1071
(4.0-11.0 x 10/L)
(1.0-4.0 x 10/L)
(2.0-8.0 × 10/L)
0.3 x 10/L
0.4 x 10/L
(< 1.0 x 10/L)
0.0 x 10/L
(¿$0.6 x 10/L)
Platelets
250 x 10/L
1150-450 X 10/L)
(< 0.2 x 10/L)
Rx: erythromycin 250mg qid
Paul Bunnell/latex screening test for IM (infectious mononucleosis): negative
Orofacial HSV-1 for 3 days. Rx: acic
1CICOVIT S70 - 010
vir 200mg - 4hrly for five days + topical
ot appetite. low libido
Job stress+++ causing depression, nichtm
nnia, difficulty getting up, loss
Poor memory and concentration; loss of ple
Low tolerance for alcohol.
sure; loss of confidence.
Split up with boyfriend. Now living alone. Considering quitting job. Wants a break
from working.
Recommended referral to psychiatrist - Pt resistant.
Rx: temazepam 20mg - 30mins before bed
R/V: 1 week
Diagnosis: reactive depression and anxiety
Pt has not filled temazepam script - not keen on drug Rx
Pt has agreed to a referral to psychiatrist.
Using the information in the case notes, write a letter of referral to Dr
Mental Meal Olnic, 1// rark Avenue. Newtown
psychiatrist, Royal
In your answer:
Expand the relevant notes into complete sentences
Use letter format
Do not use note form

Page 53 — Re: Mr. Tamer Sultan D.O.B.: 20/ 09 /1974
Letter
Dr. Hazem Gouda
Suit 3
67 The Crescent
Newtown
09/ 11/ 2016
Dear Dr. Gouda,
Re: Mr. Tamer Sultan D.O.B.: 20/ 09 /1974
I am writing to refer Mr. Sultan, a 42-year-old real estate agent, who presented by symptoms
and signs suggestive of multiple sclerosis. Your further assessment is highly appreciated.
Mr. Sultan is married with three children. He is a smoker and has no time for exercise which
resulted in being overweight. Besides, he takes zoloft for depression since 2012.
During subsequent visits, he presented by his regular complaint of tiredness, feeling
depressed and stressed. However, on 7 /10/ 2016, he reported left leg weakness. At that
time, his examination was unremarkable along with being anaemic with high cholesterol
level. Consequently, he was advised to change his lifestyle and to continue same medication.
Today, Mr. Sultan came with a history of 2 recent blackouts that were associated with
dizziness and mood changes. Moreover, he reported the same weakness of the left leg
together with tingling in his hands. Although he has started exercise, he is still overweight. His
examination showed loss of sensation on both hands and diminished left patellar reflex. Our
next step is to do CT on his head and lumbar spine.
Based on the above information, I am suspecting multiple sclerosis. Therefore, I am referring
this patient for your further assessments including an MRI study.
Yours sincerely,
Doctor
Assessor feedback
Word length 206
Comments The letter ably covers the case notes and there is a
logical flow of information. Some mistakes
pertaining to grammar are visible, but these do not
reduce communication.
Grade B
Advice 1. Revise grammar.
2. Improve word choice.
3. Always proofread your letter after finishing it.
4. Keep up the good work!
Margin comments
- Comment [bnchmrk1]: with signs and symptoms
- Comment [bnchmrk2]: him
- Comment [bnchmrk3]: has been taking
- Comment [bnchmrk4]: with
- Comment [bnchmrk5]: complaints
- Comment [bnchmrk6]: apart from
- Comment [bnchmrk7]: the
- Comment [bnchmrk8]: the recent history of 2

Page 54
Case notes / writing task (OCR)
is a patient in your general practice.
Name:
Height:
183cm
Background:
Smoker
Depression - sertraline hydrochloride (Zoloft) since Sep 2012
Overweight - long term
Married - 3 children (13, 10 & 8vrs)
Active member of local church congregation
Real estate agent - reports no time for exercise/relaxation
Patient History:
Subjective:
Examination:
Here for general check-up. Reports feeling ‘run down: tired, stressed, ‘sluggish’.
BMI: 27.8 (Wt: 93.1kg)
BP: 96/83, Heart rate (HR): 70bpm
Chest clear
Tests:
Skin check - no suspicious lesions found
CBC, cholesterol/lipids
Plan:
R/v in 1wk (discuss test results)
Subjective:
Here to receive results of blood tests (cholesterol, CBC)
Still tired, feeling ‘down’.
Examination:
Reports weakness in L leg.
BP: 90/80, HR: 79 bpm
Chest clear
Sertraline hydrochloride - ongoing
Test results:
BMI: 28.5 (Wt: 95.5kg)
Cholesterol: 6.37mmol/L
Assessment:
Repeat assessment of hypercholesterolaemia in 3mths.
CBC - low WBC; low RBC, low Hb & Hct; other results in normal range
Monitor general health - tiredness, depressed feelings.
Plan:
Pt should make lifestyle changes (smoking, diet, exercise, recreation).
Pt to dietary saturated fat, incorporate regular exercise to +weight & cholesterol
R/v in approx 1mth to assess general health, feelings of tiredness & being ‘down.
levels; stop smoking.
Complains of dizziness and reports two recent ‘blackouts’ (a few minutes each).
Feels stressed - busy at work. Mood up and down since last visit. Reports tingling
in hands. L leg still feels weak. Breathless, occasional constipation, short of energy.
Still smoking.
Has been trying to eat better & exercise more - walks (30mins) x2-3/week
BP: 88/70, HR: 76bpm
BMI: 28 (Wt: 93.7kg)
Loss of sensation on L & R hands (sharp/blunt)
Herexes - diminisned L patellar renex
Tests:
Order head & lumbar spinal CT to try to determine cause(s) of leg weakness and
associated objective hyporeflexia (?central or spinal - check for spinal cysts/
Assessment:
tumours, etc.).
?multiple sclerosis
Order CT
Refer to neurologist: a full neurological as
nent: order MRI
Using the information given in the case notes, write a letter of referral to Dr
Suite 3, 67 The Crescent, Newtown.
In your answer:
• Expand the relevant notes into complete sentences
• Use letter format
The body of the letter should be approximately 180-200 words.

Page 55 — Re: Mr Anees Ford, 45 Years of age
Letter
Dr. O Shawki
Neurosurgeon
City Hospital
Newton
25/01/2018
Dear Dr. Shawki
Re: Mr Anees Ford, 45 Years of age
Thank you for seeing Mr Ford, a 45-year-old stock brocker, who has presented with a
discogenic low back pain. For your kind care.
Mr. Ford is married with three children. He is a smoker and he drinks alcohol daily. He is
mildly overweight. Of note to mention that he is allergic to Pethidime, penicillin and a
radiographic contrast. Otherwise, he is medically free.
On 11/01/2018, the patient has visited the clinic complaining of severe low back pain which
was not radiating to thighs then after lifting a heavy object. On examination, he was vitally
stable. He had loss of lumbar lordosis as well as painful limitation of spinal flexion &
extension. However, he maintained full range of lateral flexion. At that time, his SLR test was
90° bilaterally. Mr Ford was advised to have a sick leave and to continue oral analgesics. He
was given a follow-up appointment one week later. Unfortunately, he showed no
improvement. In addition, the pain has radiated to his right thigh and leg.
Today, and after another week of rest and pain killers, Mr Ford has been almost immobile
because of the agonizing low back pain and right sciatica. His examination shows more
restricted spinal movements in all direction. While SLR test is only 50° on the right side.
I am referring Mr Ford to you as my provisional diagnosis is discogenic radiculopathy for
performing MRI and your opinion regarding possibility of surgery accordingly.
Yours sincerely,
Doctor
Assessor feedback
Word length 239
Comments The letter is quite long. Also, mistakes pertaining
to grammar and word choice are visible. Effort to
write information in brief is missing as well.
Overall, the letter requires further improvements.
Grade C+
Advice 1. Avoid writing more than 200 words.
2. Pay attention to tenses.
3. Improve word choice.
Margin comments
- Comment [bnchmrk1]: a 45-year-old stock broker
- Comment [bnchmrk2]: Please note that
- Comment [bnchmrk3]: and
- Comment [bnchmrk4]: , and
- Comment [bnchmrk5]: rest
- Comment [bnchmrk6]: Upon his following visit,
- Comment [bnchmrk7]: and his
- Comment [bnchmrk8]: with
- Comment [bnchmrk9]: of
- Comment [bnchmrk10]: He requires
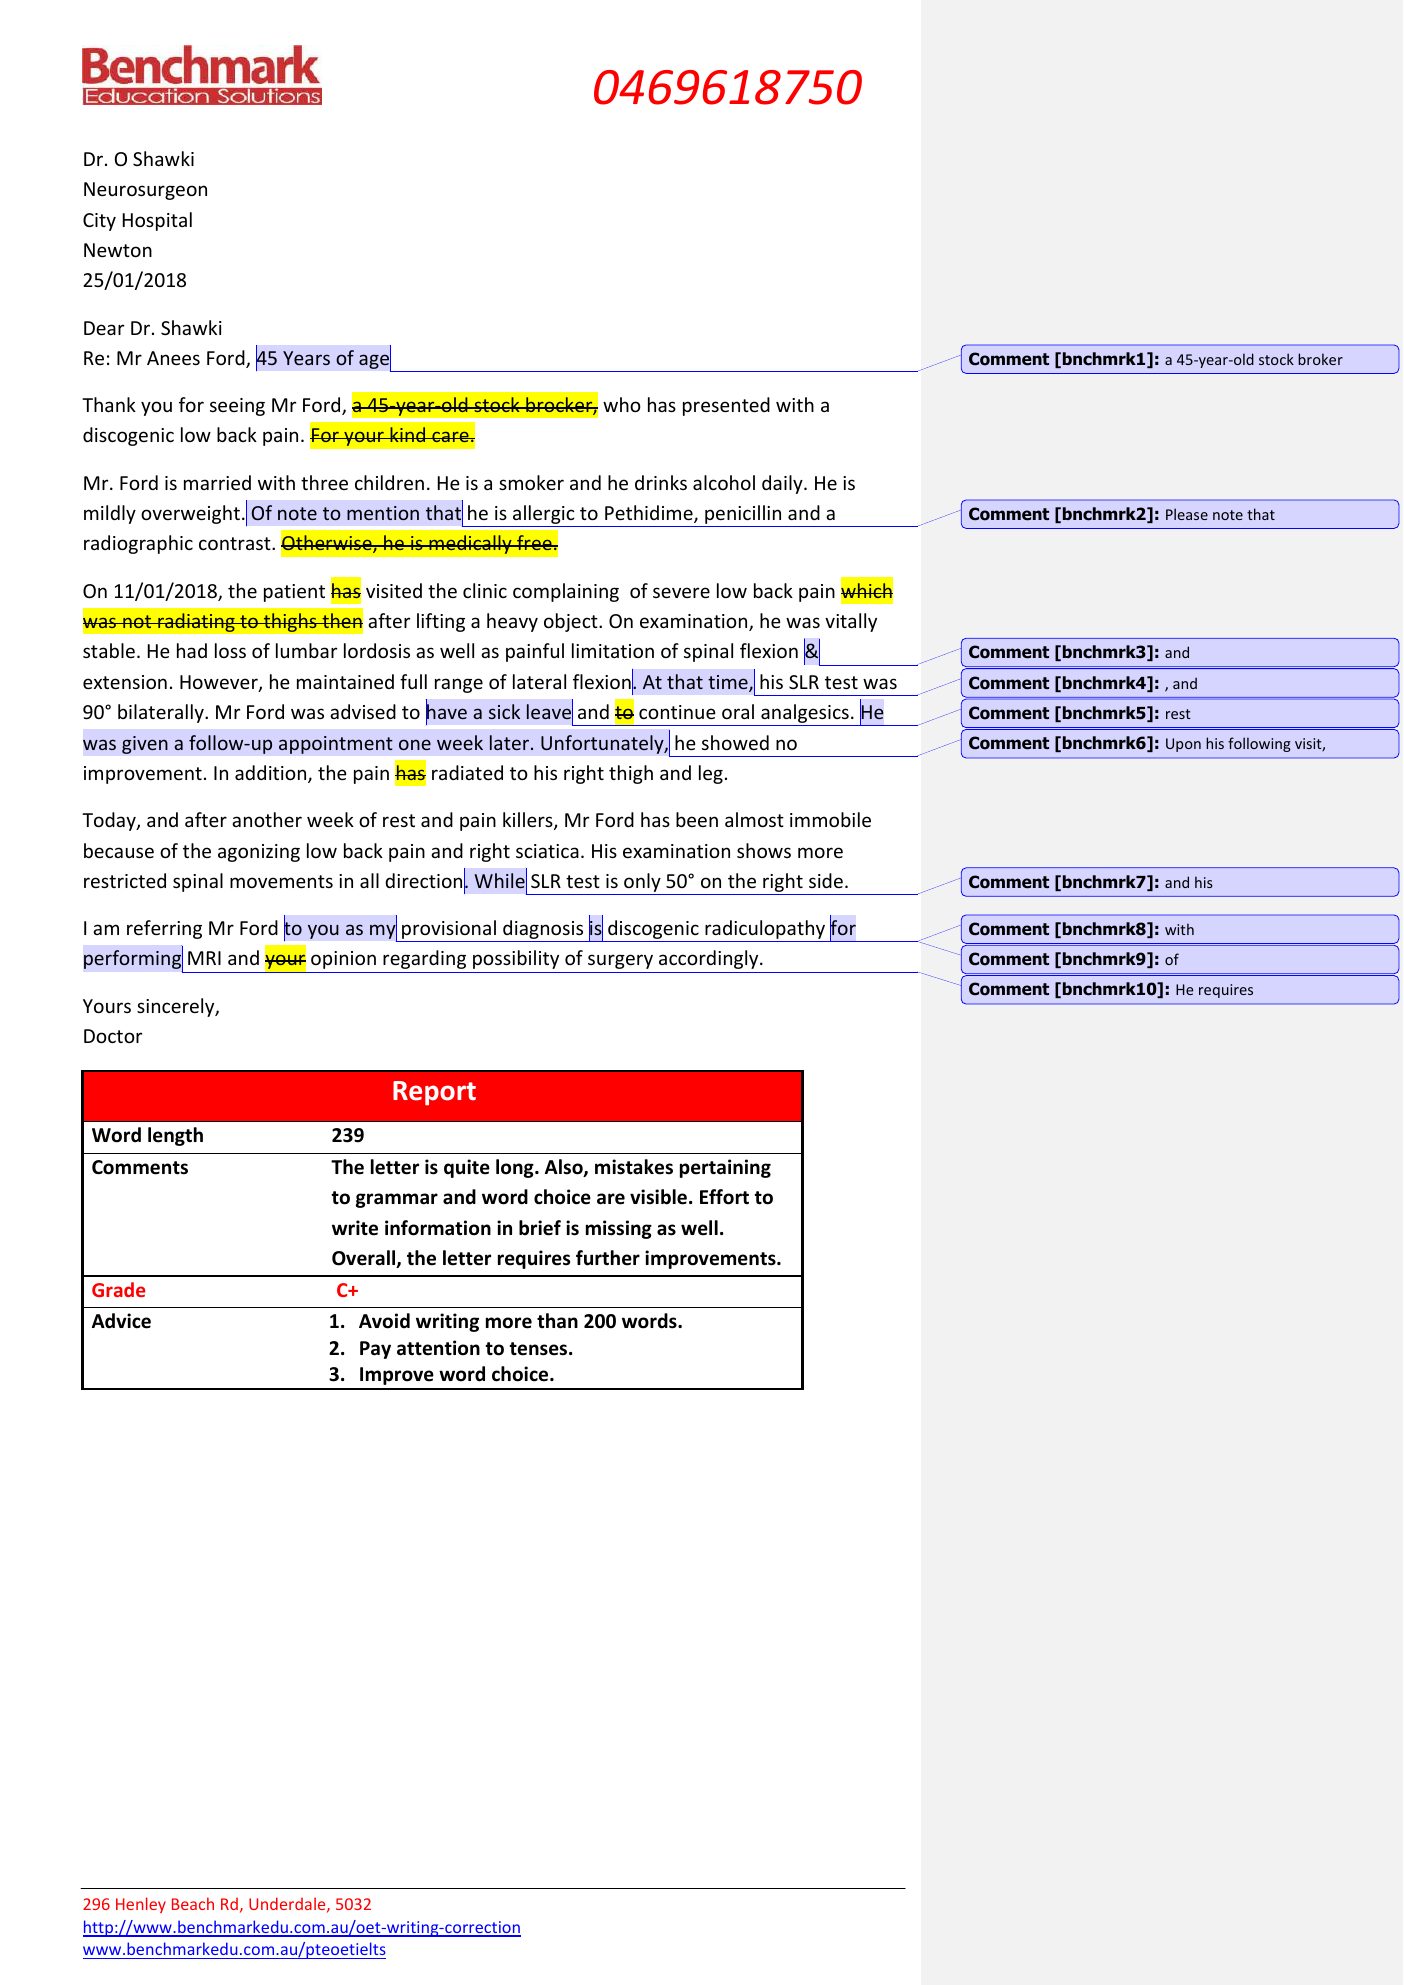
Page 56 — Re: Mr Anees Ford
Handwritten page: OCR is a rough search aid, not a dependable transcription. Check the original image.
Letter (OCR)
Please record your answer on this page.
(Only answers on Page 3 and Page 4 will be marked.)
Ur. O Shawki
Neurosurgeon
ity Haspital
Vemtar
25/01/2018
Dear Dr. Shank
Re: Mr Anees Ford
, 45 years of age
Kind. care
He is as Ford is married with thee didi.
is medically
On 11/01/2018, the patent hai vi back pain
civic comp at sadhating to thighe then tafter
eftng a heavy object. On examination,
itally stable. He had loss of lumbar
Lordosis
lateral plexion
his SLK
test was
advised to havera sick leave and to continue
90” bilaterally. Mr Ford’ was
OET Writing sub-test - Answer booklet

Page 57
Handwritten page: OCR is a rough search aid, not a dependable transcription. Check the original image.
Case notes / writing task (OCR)
Please record your answer on this page.
(Only answers on Page 3 and Page 4 will be marked.)
a fallow-up
oral analgesis. He was give
later. Unfortinately,
ня рат
ind
leg.
rest and
right
sciatica
I am refferring Mr Ford to you
ours sincerely,
Doctor
OET Writing sub-test - Answer booklet

Page 58 — Re: Ms Sara Adams
Letter
Admitting Officer
Emergency Department
Newtown Hospital
13/09/2014
Dear Sir/Madam,
Re: Ms Sara Adams
Thank you for seeing Ms Adams, who is having an acute exacerbation of asthma and
pneumonia. Your urgent management is highly appreciated.
Ms Adams is a 38-year-old administrator who is known to be asthmatic and hypertensive. For
both conditions she is receiving ramipril, fluticasone and ventolin.
On 10/09/2014, the patient presented with runny nose, productive cough as well as wheezy
chest. At that time, she had no shortness of breath. On examination, she showed nasal
congestion, red throat, in addition to scattered chest wheezes. Ventolin dose was augmented
and she was advised of rest. Unfortunately, Ms Adams came back 2 days later as her chest
condition became worse. She complained of shortness of breath and fever. Therefore,
Amoxicillin and oral prednisone were prescribed.
Today, Ms Adams, in spite of receiving the antibiotic and the prednisone, appeared very
unwell. Her fever has not settled; her shortness of breath has become more significant. When
examining her chest, a generalized wheeze as well as bibasal crepitations were found.
Showing no improvement on Ventolin Nebules, Ms Adams is most propably having an
exacerbating attack of asthma on top of pneumonia. Thus, I am referring her to you for your
urgent management. Should u have any queries, please do not hesitate to contact me.
Yours sincerely,
Doctor
Assessor feedback
Word length 209
Comments Mistakes pertain to articles, conjunctions and
punctuation. On the bright, paragraphing is logical
and relevant case notes have been covered
adequately. Overall, the letter meets the
expectations.
Grade B
Advice 1. Try to write information in brief wherever
possible.
2. Revise grammar.
3. Keep up the good work!
Margin comments
- Comment [teacher1]: , Peroxitine
- Comment [teacher2]: V
- Comment [teacher3]: two days later, her
- Comment [bnchmrk4]: Her condition has still not improved and she appeared unwell today.
- Comment [teacher5]: and
- Comment [teacher6]: was (simply write and in place of as well as to avoid confusion)
- Comment [teacher7]: The dosage were increased accordingly.
- Comment [teacher8]: With her condition worsening, I suspect
- Comment [teacher9]: you
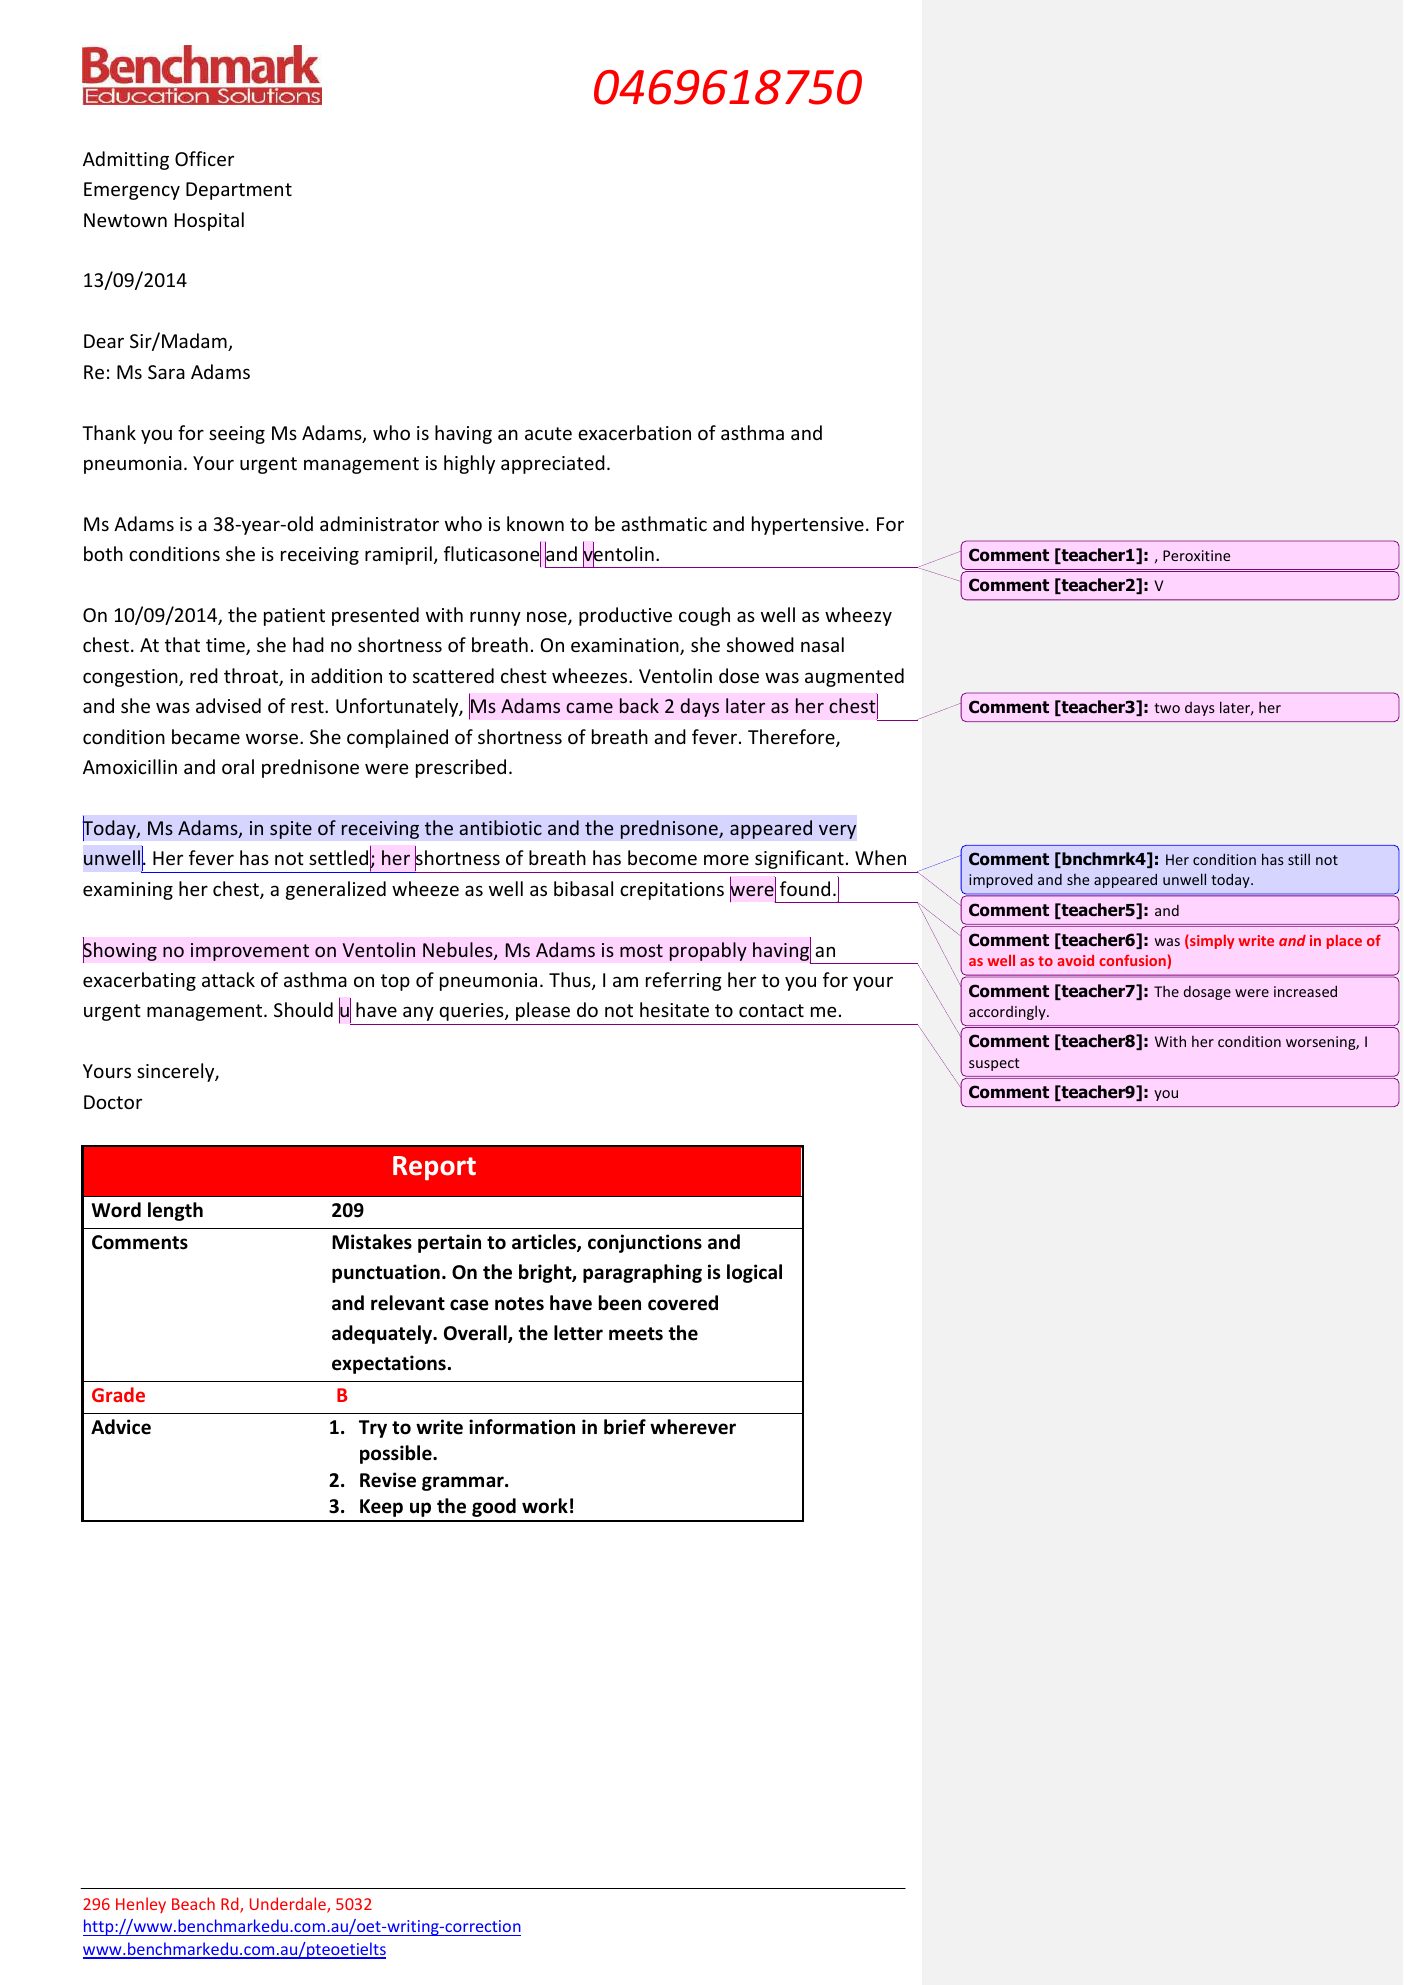
Page 59 — Re: Mr James Seymour D.O.B.: 19/09/1953
Letter
Dr Malcolm Still
Rheumatologist
5 Grant st
Fairmont
03/05/2014
Dear Dr Still,
Re: Mr James Seymour D.O.B.: 19/09/1953
Thank you for seeing Mr Seymour, a 60-year-old retired academic, whose his features are
suggestive of gout. Your further management is greatly appreciated.
Mr Seymour, who lives alone as he is divorced with no children, has been an ex-smoker for
the post 20years. However, he is a heavy drinker. His father had suffered from rheumatoid
arthritis for about 50 years till his death. The patient’s past history shows recurrent attacks of
possible gout affecting his large toe over the last 4 years. Regarding medications, he takes
lengout, indocind and allopurinal on occasions.
One week ago, the patient presented with a complaint of a swollen left large tow. He
reported that it had been the third bout of gout over the last 8 months for which he had been
taking a low dose of colchicin and irregular doses of Indocid. At that time he was not taking
allopuranal; nevertheless, he modified his diet. His examination showed an inflamed left big
toe with no other joint affection. Therefore, I ordered an x-ray and some blood tests and
advised him on taking proper doses of gout medications along with regular analgesics.
Moreover, oxycodone 5mg was prescribed only when required.
Today, the gout attack has been improving with good compliance to his medication. The x-ray
indicated some degeneration at the left metatarsophalangeal joint as well as an elevation of
CRP level was noted. Unfortunately, the patient is very concerned about the possibility of
rheumatoid arthritis and requested a referral to a rheumatologist. Please note, synovial fluid
sampling was discussed with the patient as well as the importance of diet control and alcohol
reduction.
In view of the above, I am referring this patient to you upon his insistence for your further
management. Please contact me if you require further information.
Yours sincerely
Doctor
Assessor feedback
Word length 297
Comments This is an excessively long letter with no effort to
write information in brief. Also, mistakes
pertaining to word choice and grammar are visible.
Overall, the letter requires further improvements.
Grade C+
Advice 1. Try to finish your letters in 200 to 220 words.
2. Improve word choice.
3. Revise grammar.
Margin comments
- Comment [bnchmrk1]: will/would be
- Comment [bnchmrk2]: and
- Comment [bnchmrk3]: He has a family history of arthritis
- Comment [bnchmrk4]: a
- Comment [bnchmrk5]: N
- Comment [bnchmrk6]: The patient’s
- Comment [bnchmrk7]: Therefore, the patient has requested
- Comment [bnchmrk8]: along with
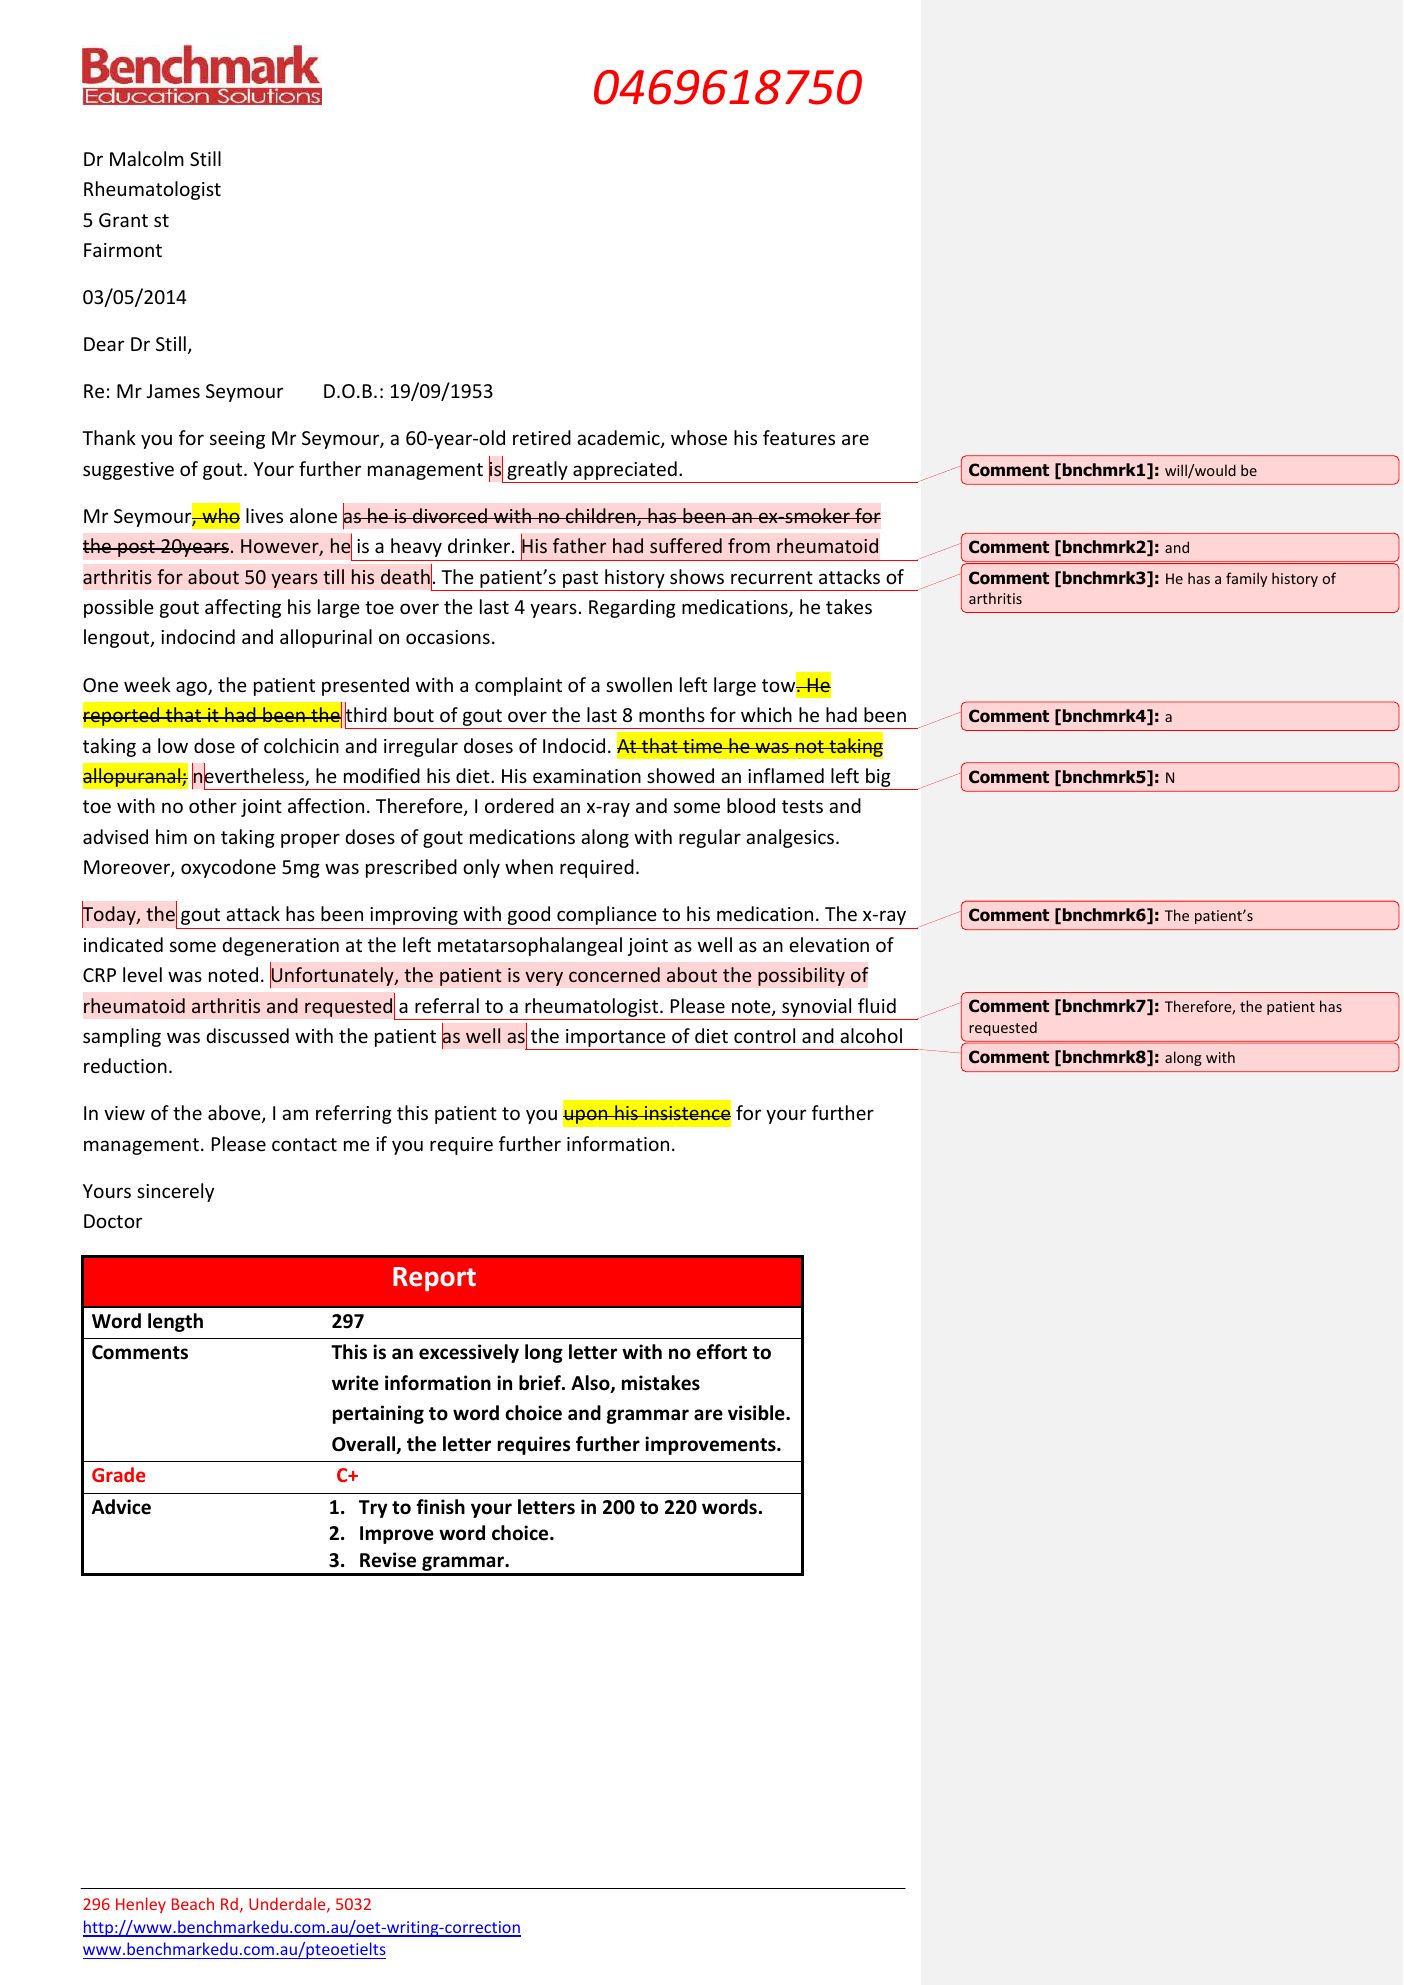
Page 60 — Re: Ms Sally McConville
Letter
Admitting Officer
Emergency Department
Newtown Hospital
13/9/2014
Dear Sir/Madam,
Re: Ms Sally McConville
Thank you for urgently seeing this 38-year-old lady, whose features are suggestive of
pneumonia. Your urgent management would be highly appreciated.
Ms McConville, who is a non-smoker administrator, has a history of asthma, hypertension
and depression for which she takes regular medications. She has no known allergies.
She presented on 10th
of this month with acute asthmatic symptoms, and on 12th
of this
month, was diagnosed with infective exacerbation of asthma. She was commenced on
amoxicillin 500mg three times a day in addition to Ventolin.
This patient presented today, after being seen twice in the previous 3 days, with obvious
respiratory distress, fever and the feel of unwellness. She has a diffue wheeze and basal
cripitations over both lung fields. Moreover, her temperature is 37.7, Pulse 112 and Blood
Pressure is 100/65. Although she was given salbutamol 5mg, she is still suffering of
respiratory distress.
It is worth mentionoing that this patient was diagnosed with an infective exacerbation of
asthma yesterday; for this reason, she was commenced on Amoxicillin 500ng three times a
day. Those were added to her regular does of Ventolin which had been prescribed since
10/9/2014.
In view of the above, my provisional diagnosis is acute asthmatic attack with possible
pneumonia. Therefore, it would be highly appreciated if you could urgently manage her
condition as you feel appropriate.
Yours sincerely,
Doctor
Assessor feedback
Word length 183
Comments Inaccuracies pertaining to word choice, grammar,
capitalization and spelling have been made. The
order of information needs to be improved.
Nevertheless, the letter meets the expectations.
Grade B
Advice 1. Revise grammar.
2. Be careful with spelling and capitalization.
3. Improve choice of words.
4. Always proofread the letter after finishing
writing it.
Margin comments
- Comment [teacher1]: this information is not really important for emergency doctor I suppose!
- Comment [teacher2]: worsening
- Comment [teacher3]: feeling unwell
- Comment [teacher4]: diffused wheezing
- Comment [teacher5]: crepitations
- Comment [teacher6]: p
- Comment [teacher7]: b
- Comment [teacher8]: p
- Comment [teacher9]: mentioning
- Comment [teacher10]: a
- Comment [teacher11]: mg
- Comment [teacher12]: dose 296 Henley Beach Rd, Underdale, 5032 http://www.benchmarkedu.com.au/oet-writing-correction www.benchmarkedu.com.au/pteoetielts

Page 61
Handwritten page: OCR is a rough search aid, not a dependable transcription. Check the original image.
Case notes / writing task (OCR)
Admitting Offican
de velantu Hospitr
13/9/2014
Per me sally de enville
88. r-old lady, ve ass are
calvine
Ms Me Conville biko is a non smoker petitie
This Petint Penta sends das,
bering seen twice In the Pou
bacal cripitations over both
Tam pratin
lung flute 12 and Blood Passure i
109/65. Although sha was finan) salbadamol
still sufy ering of respirate
yestarday; per
- You
