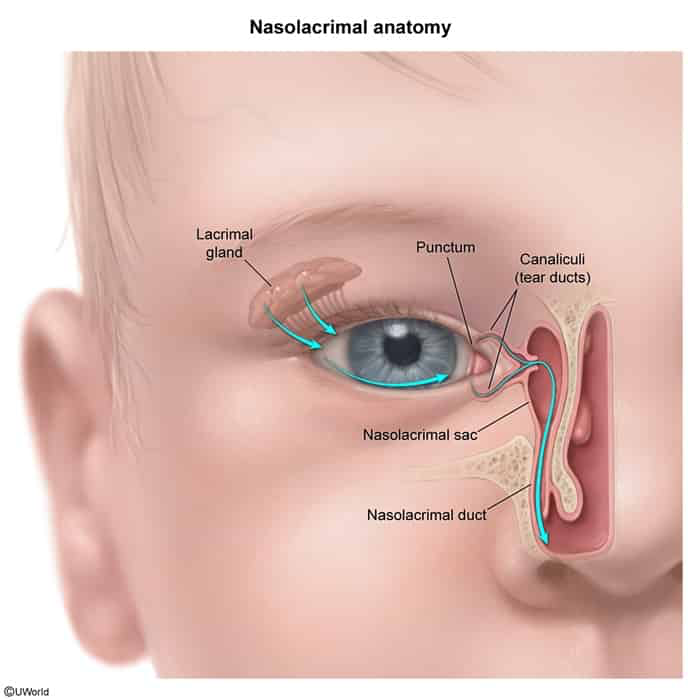
Dacryostenosis
- Etiology: Failed canalization of distal nasolacrimal duct at the Valve of Hasner; most common cause of infant tearing.
- Clinical Presentation:
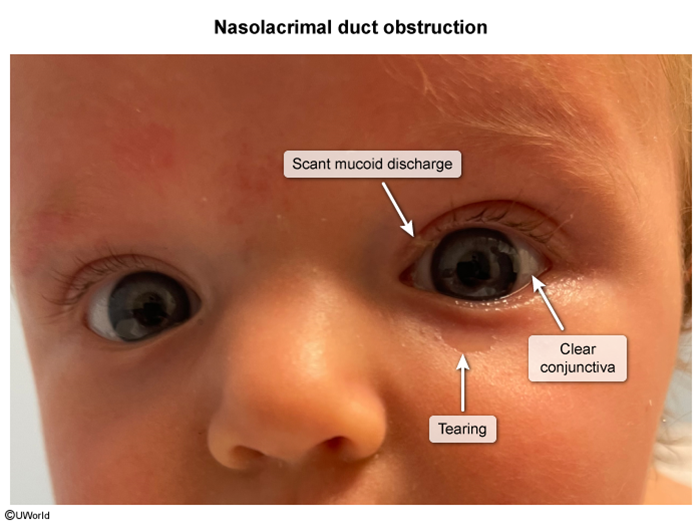
- Onset at ~2 weeks of life with chronic epiphora (tearing) and eyelash matting/crusting.
- Clear/mucoid discharge expressible via medial canthus pressure.
- Key Exam Finding: Clear conjunctiva (NO injection/erythema) and normal red reflex/cornea. c
- High-Yield Differentials:
- Dacryocystitis: Painful, tender, erythematous swelling over the medial canthus ± fever.
- Congenital Glaucoma: Epiphora + photophobia + blepharospasm + enlarged/cloudy cornea (buphthalmos).
- Conjunctivitis: Prominent conjunctival erythema/injection and chemosis.
- Diagnosis: Clinical; confirmed if needed by fluorescein dye disappearance test (dye remains >5 min).
- Management Algorithm:
- First-line (<9–12 months old): Conservative; Crigler massage (firm downward massage over lacrimal sac) + warm compresses (>90% resolve spontaneously by age 1).
- Acute Purulence: Add topical ophthalmic Abx (e.g., erythromycin or polymyxin/trimethoprim).
- Refractory (≥9–12 months old): Surgical nasolacrimal duct probing.
Dacryocystitis
- Etiology & Bugs:
- Clinical Presentation:
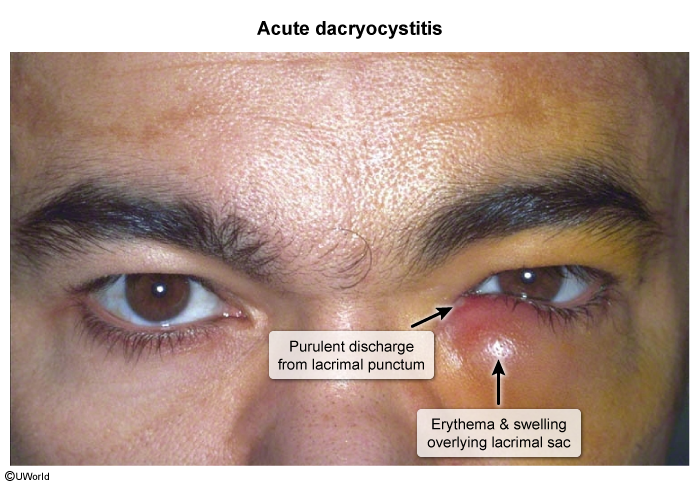
- Rapid-onset pain, erythema, warmth, and swelling at the medial canthus (inferomedial orbit).
- Epiphora (tearing) and purulent discharge expressed from the lacrimal punctum on palpation.
- Preserved visual acuity, normal EOM, and absence of proptosis.
- Diagnosis:
- Primarily clinical; culture purulent expressate to guide Abx.
- CT orbit w/ IV contrast indicated only if suspected orbital extension or abscess.
- High-Yield Differential:
- Dacryoadenitis: Infection/inflammation of lacrimal gland at supratemporal/superolateral orbit (“S-shaped” ptosis).
- Canaliculitis: “Pouting punctum” with expression of sulfur granules (Actinomyces).
- Orbital cellulitis: Differentiated by proptosis, ophthalmoplegia, and pain with EOM.
- Management:
- Initial/Acute: Systemic Abx (oral Amoxicillin-clavulanate or Clindamycin for mild; IV Vancomycin + Ceftriaxone for severe/systemic) + warm compresses.
- Definitive: Dacryocystorhinostomy (DCR) to bypass NLDO; performed electively after acute infection resolves.
- Contraindication: Do not irrigate, probe, or dilate the duct during acute infection (risk of bacteremia and fistula).
- Complications:
- Preseptal/orbital cellulitis, cutaneous fistula, cavernous sinus thrombosis.